Related Experiment Video
Updated: Jan 2, 2026

Cardiac Response to β-Adrenergic Stimulation Determined by Pressure-Volume Loop Analysis
Published on: May 19, 2021
Differential effect of selective beta 1 and nonselective beta-adrenoceptor blockade on epinephrine and atropine
L Gullestad1, K Forfang, S Simonsen
1Medical Department B, National Hospital of Norway, University of Oslo.

Abstract:
Sympathetic stimulation with epinephrine (EPI) combined with parasympathetic blockade with atropine was studied in 10 healthy volunteers premedicated with placebo or three different beta-adrenoceptor blockers: atenolol (62.5 micrograms/kg, beta 1-selective), propranolol (62.5 micrograms/kg, nonselective), and pindolol (7.5 micrograms/kg, nonselective with intrinsic sympathomimetic activity, ISA). EPI infusion (0.06 microgram/kg/min) after placebo increased heart rate (HR) and systolic blood pressure (SBP) and decreased diastolic BP (DBP). Pretreatment with atenolol reduced the HR increase, and caused similar changes in BP. In contrast, pretreatment with propranolol and pindolol decreased HR and increased BP. Combined EPI and atropine (15 micrograms/kg) after placebo increased HR by 40% without causing BP changes. Similar HR changes were observed after administration of all beta-adrenoceptor blockers, but whereas a marked pressor response was observed after propranolol and pindolol a blunted response was observed after atenolol. Propranolol and pindolol reduced myocardial oxygen demand estimated by the HR x BP product after EPI, but this response was abolished by atropine. Serum potassium decreased from 3.9 +/- 0.2 to 3.2 +/- 0.3 mM after EPi and atropine. This effect was less after atenolol, and potassium increased after premedication with propranolol and pindolol. Our results show that nonselective beta-adrenoceptor blockade has a favorable effect on potassium homeostasis and oxygen demand parameters during EPI infusion but causes a marked pressor response, contrary to a beta 1-selective agent, during combined sympathetic stimulation and parasympathetic blockade. They also highlight the importance of the vasodilator cholinergic system as a defense mechanism in such situations.
More Related Videos
 05:58
Testing Acetylcholine Followed by Adenosine for Invasive Diagnosis of Coronary Vasomotor Disorders
Published on: February 3, 2021
 08:41
Assessment of Vascular Tone Responsiveness using Isolated Mesenteric Arteries with a Focus on Modulation by Perivascular Adipose Tissues
Published on: June 3, 2019
Related Concept Videos
 01:26
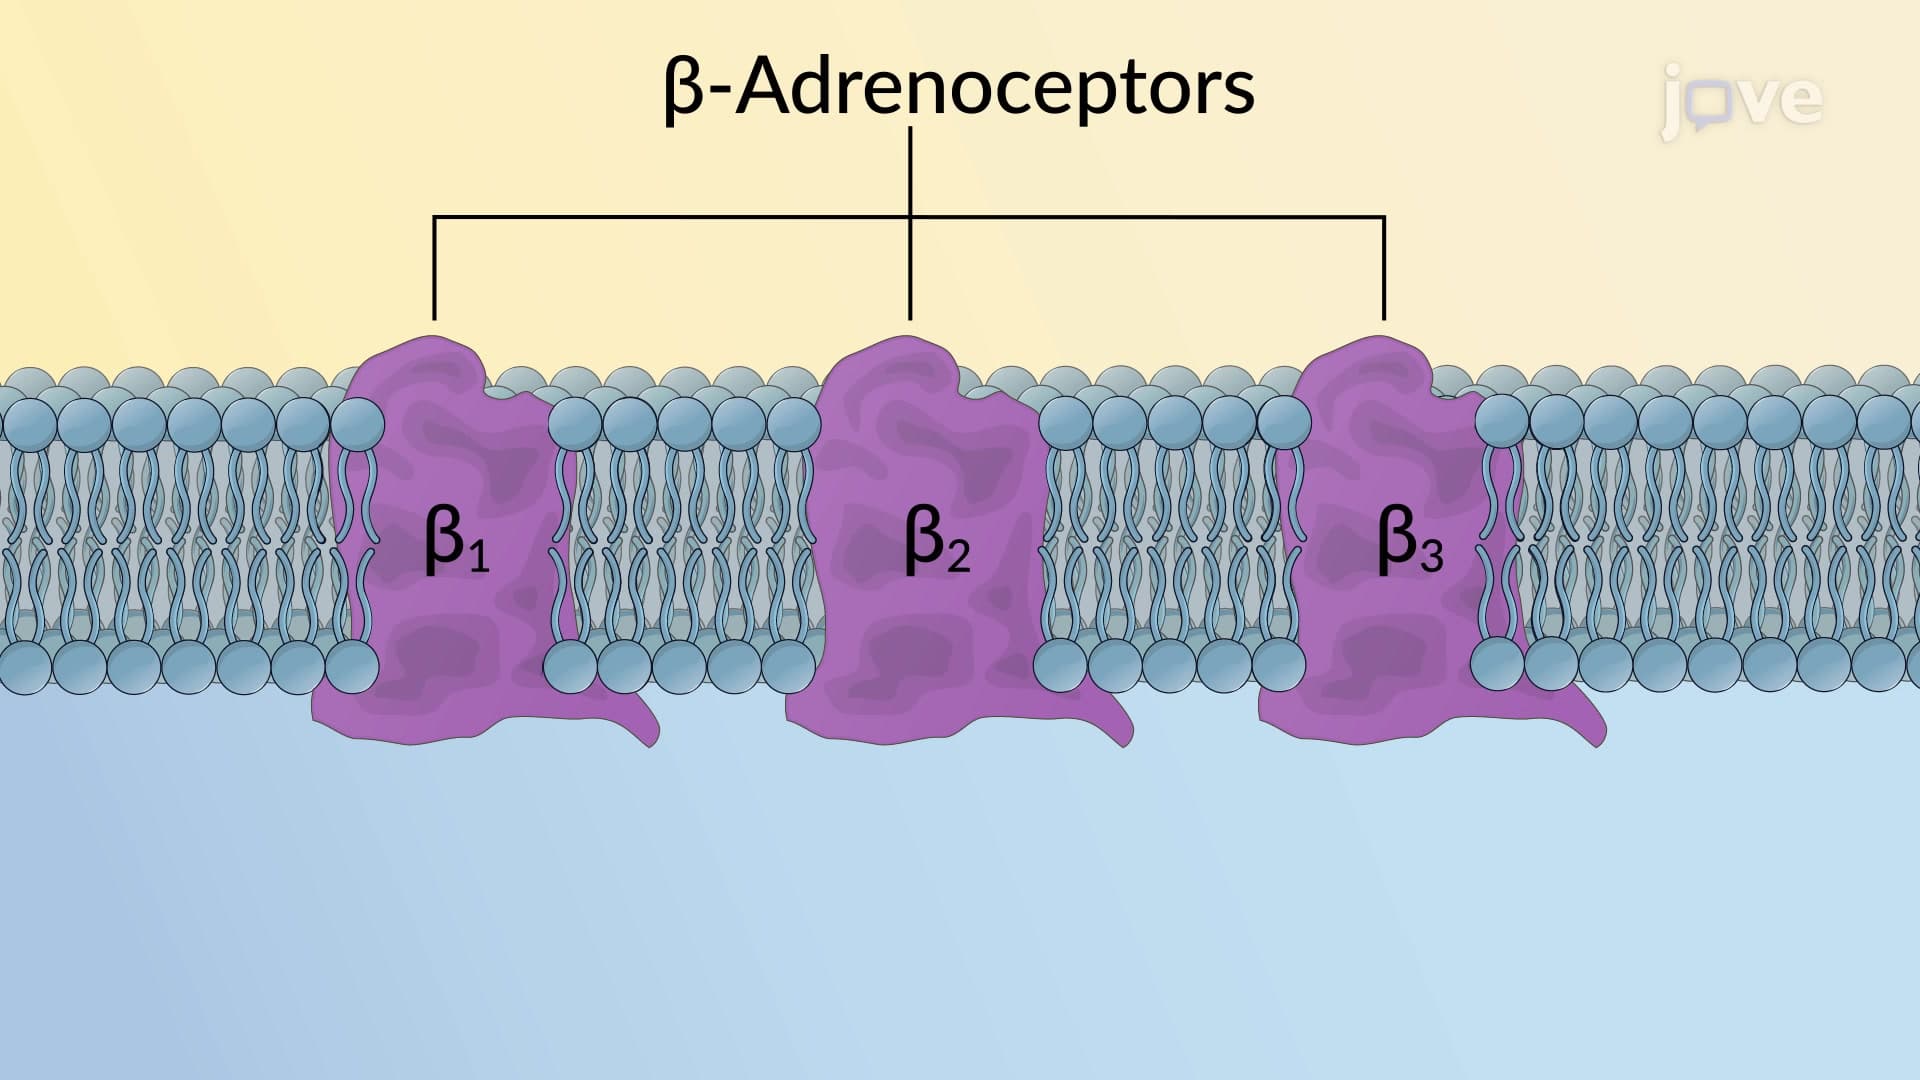
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors...
 01:28
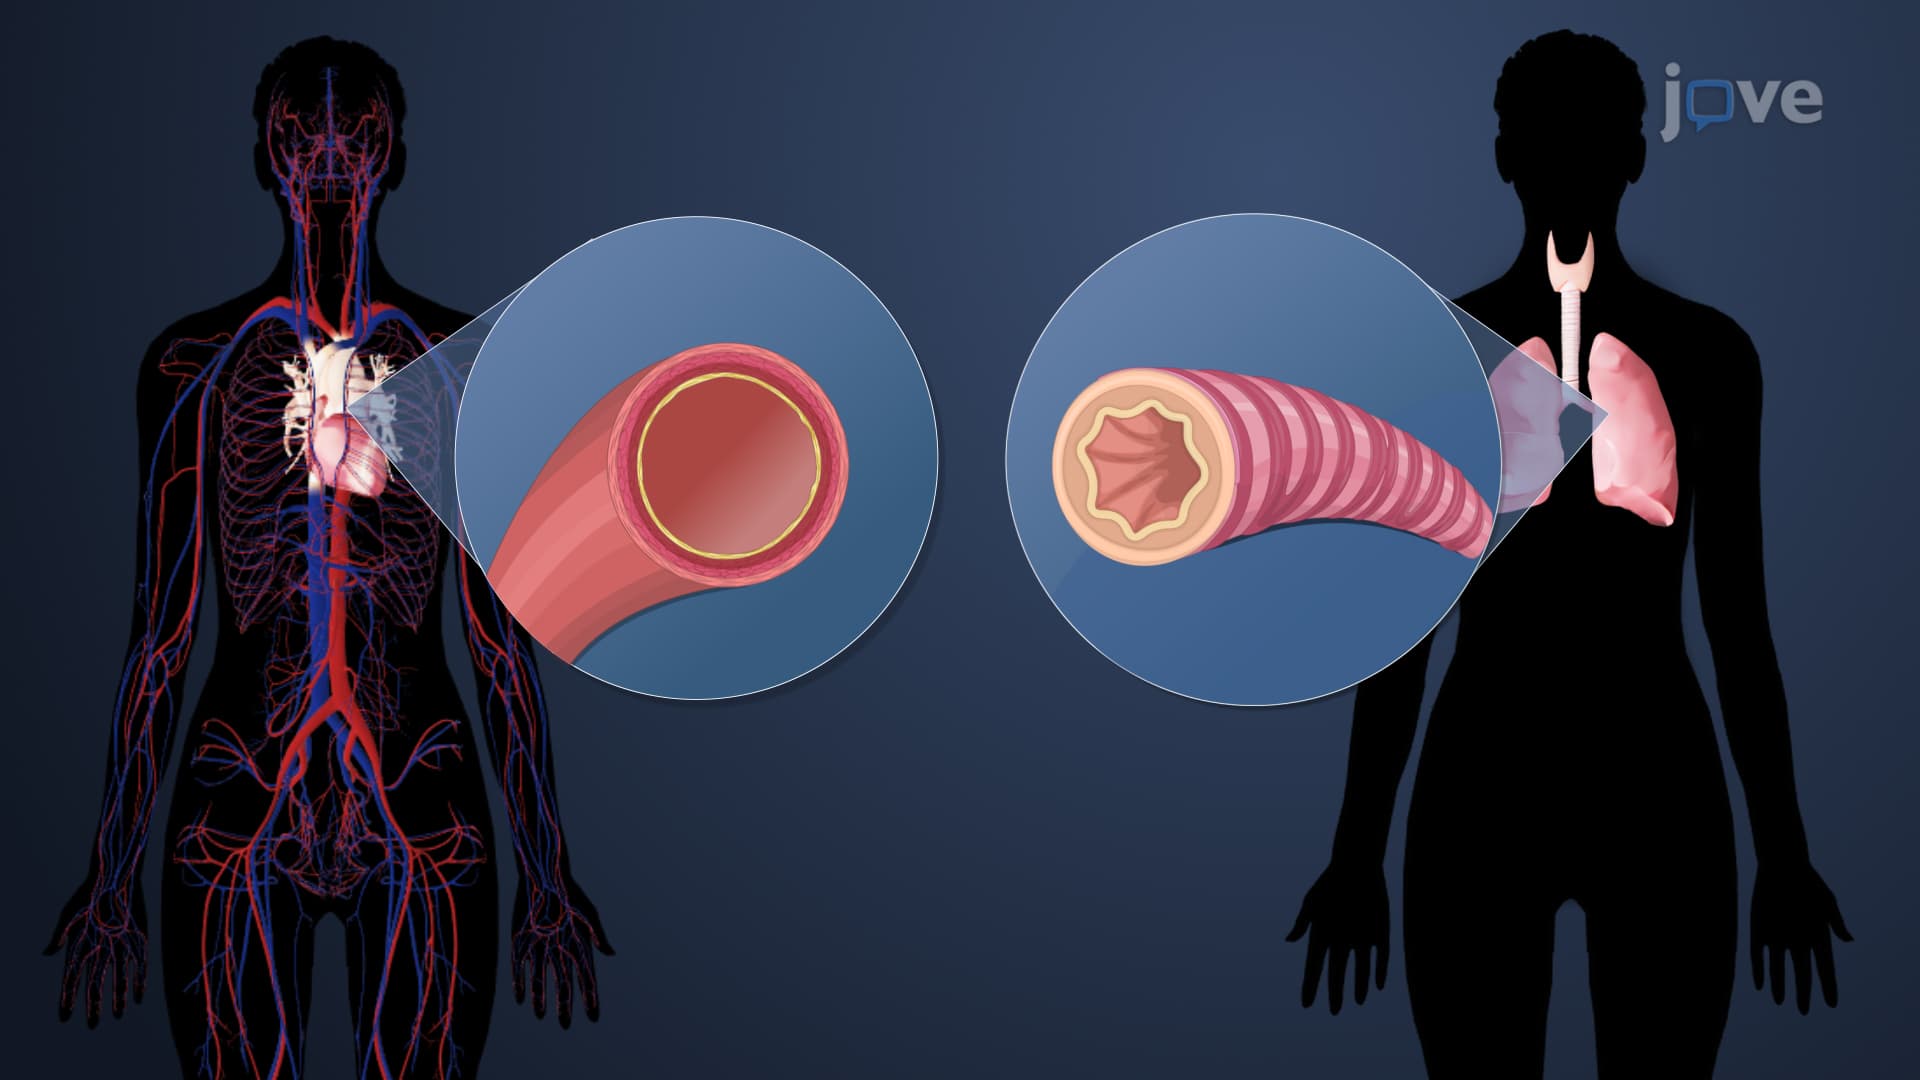
Antihypertensive Drugs: Types of β-Blockers
 01:27
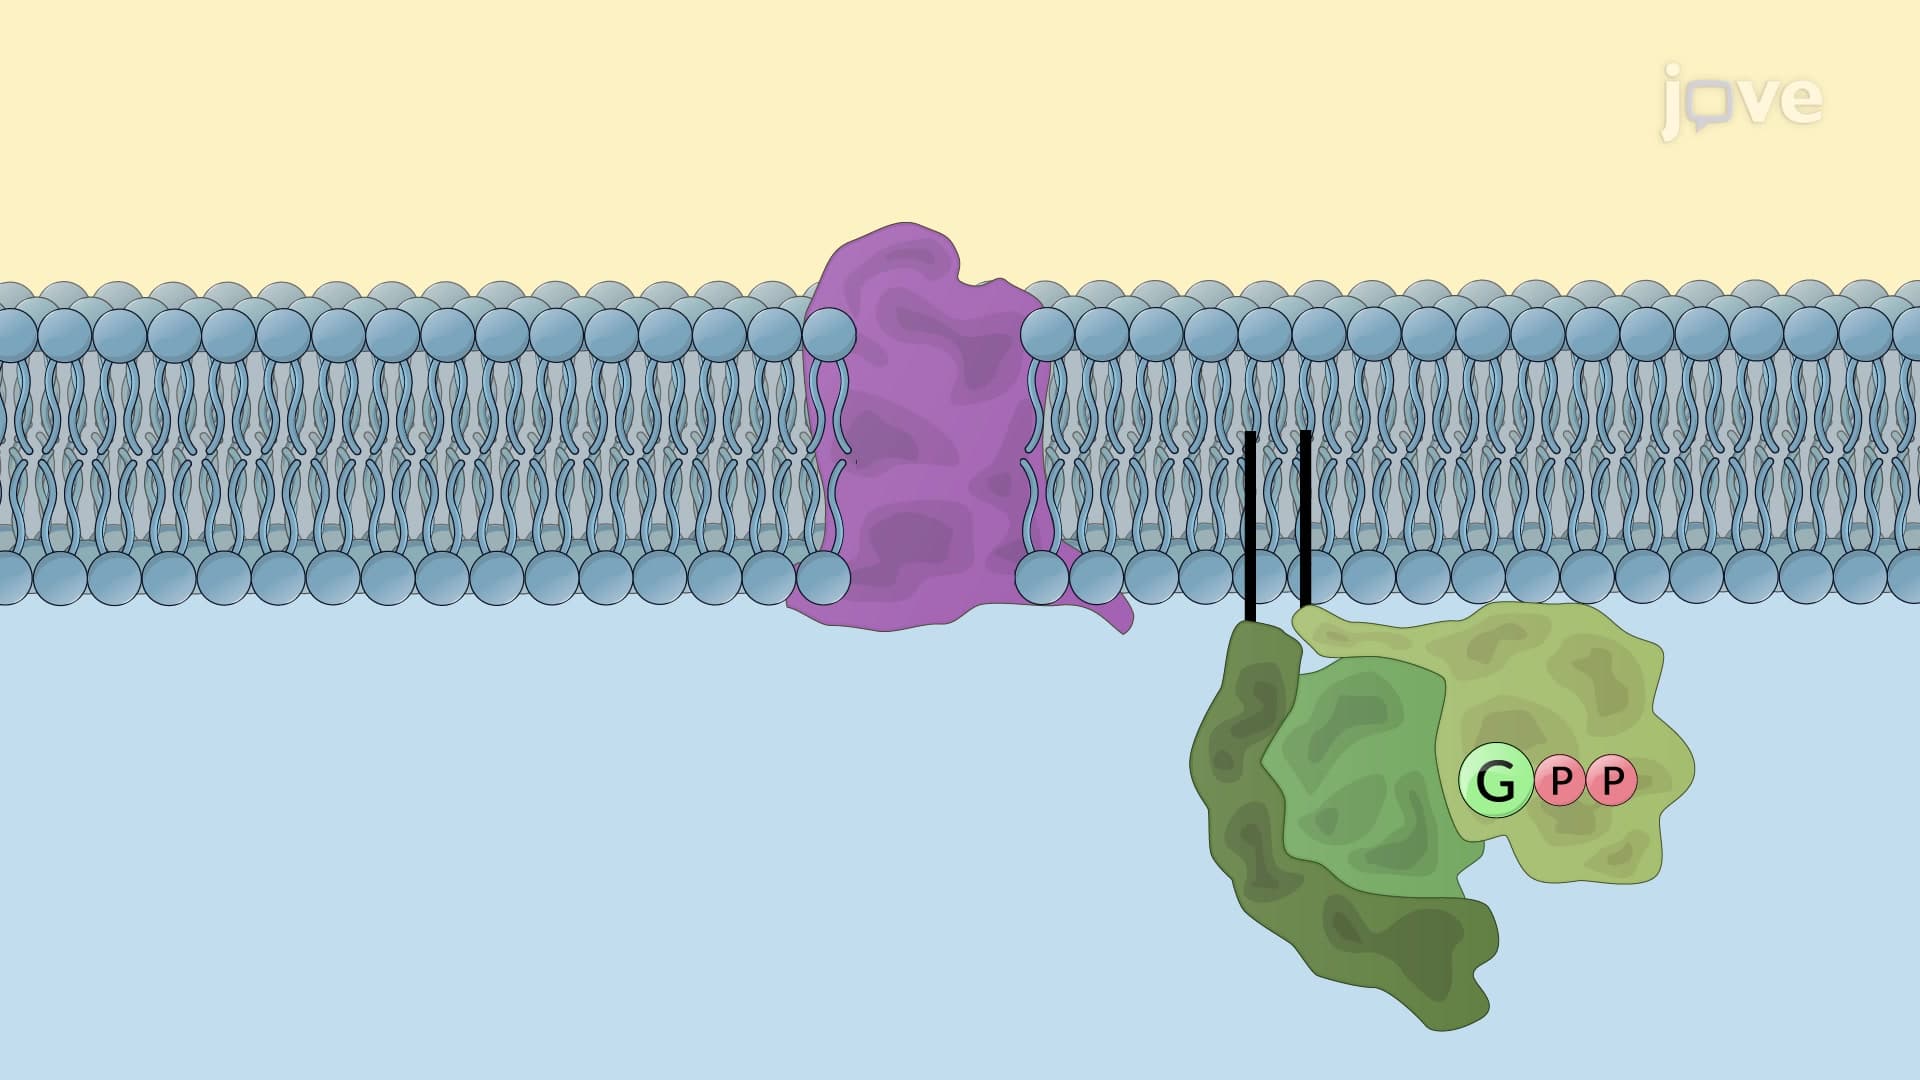
Adrenergic Receptors (Adrenoceptors): Classification
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors,...
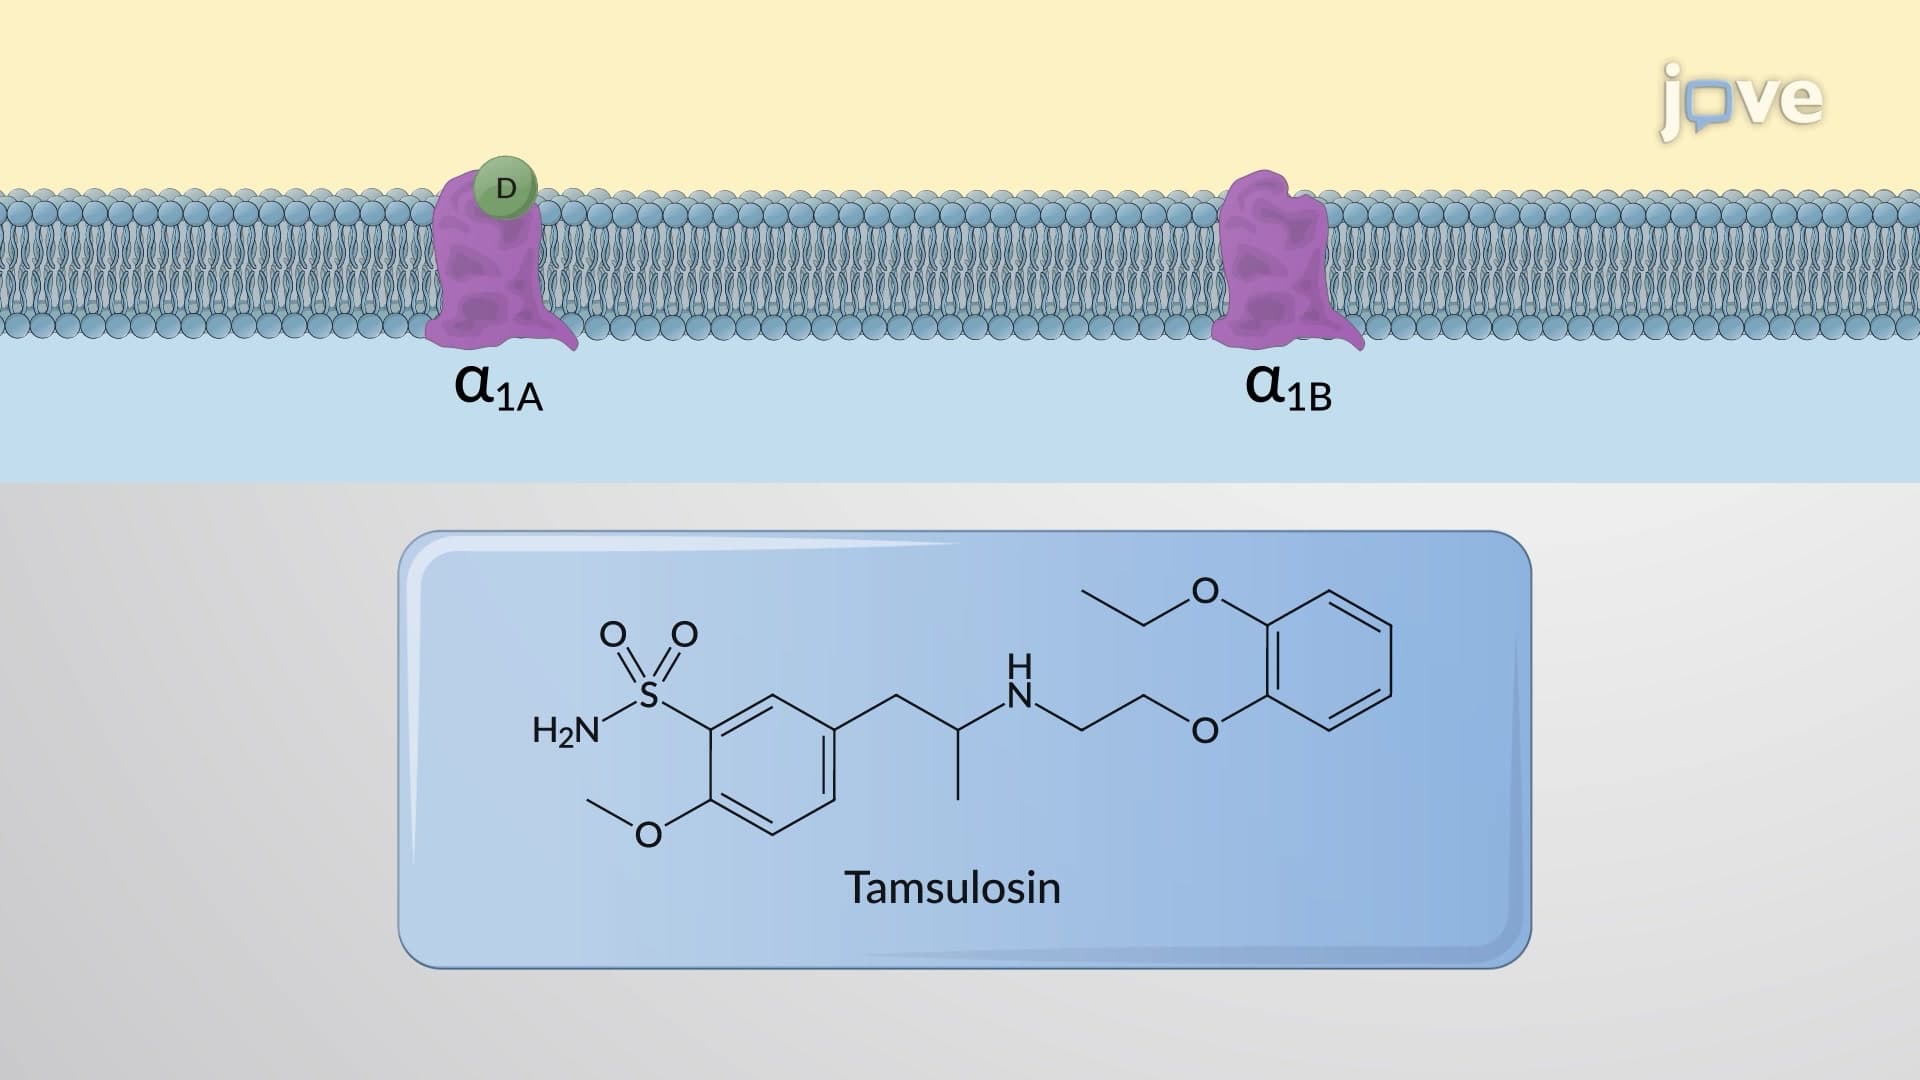 01:31
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase...
 01:30
Adrenergic Agonists: Direct-Acting Agents
These agents can be classified...
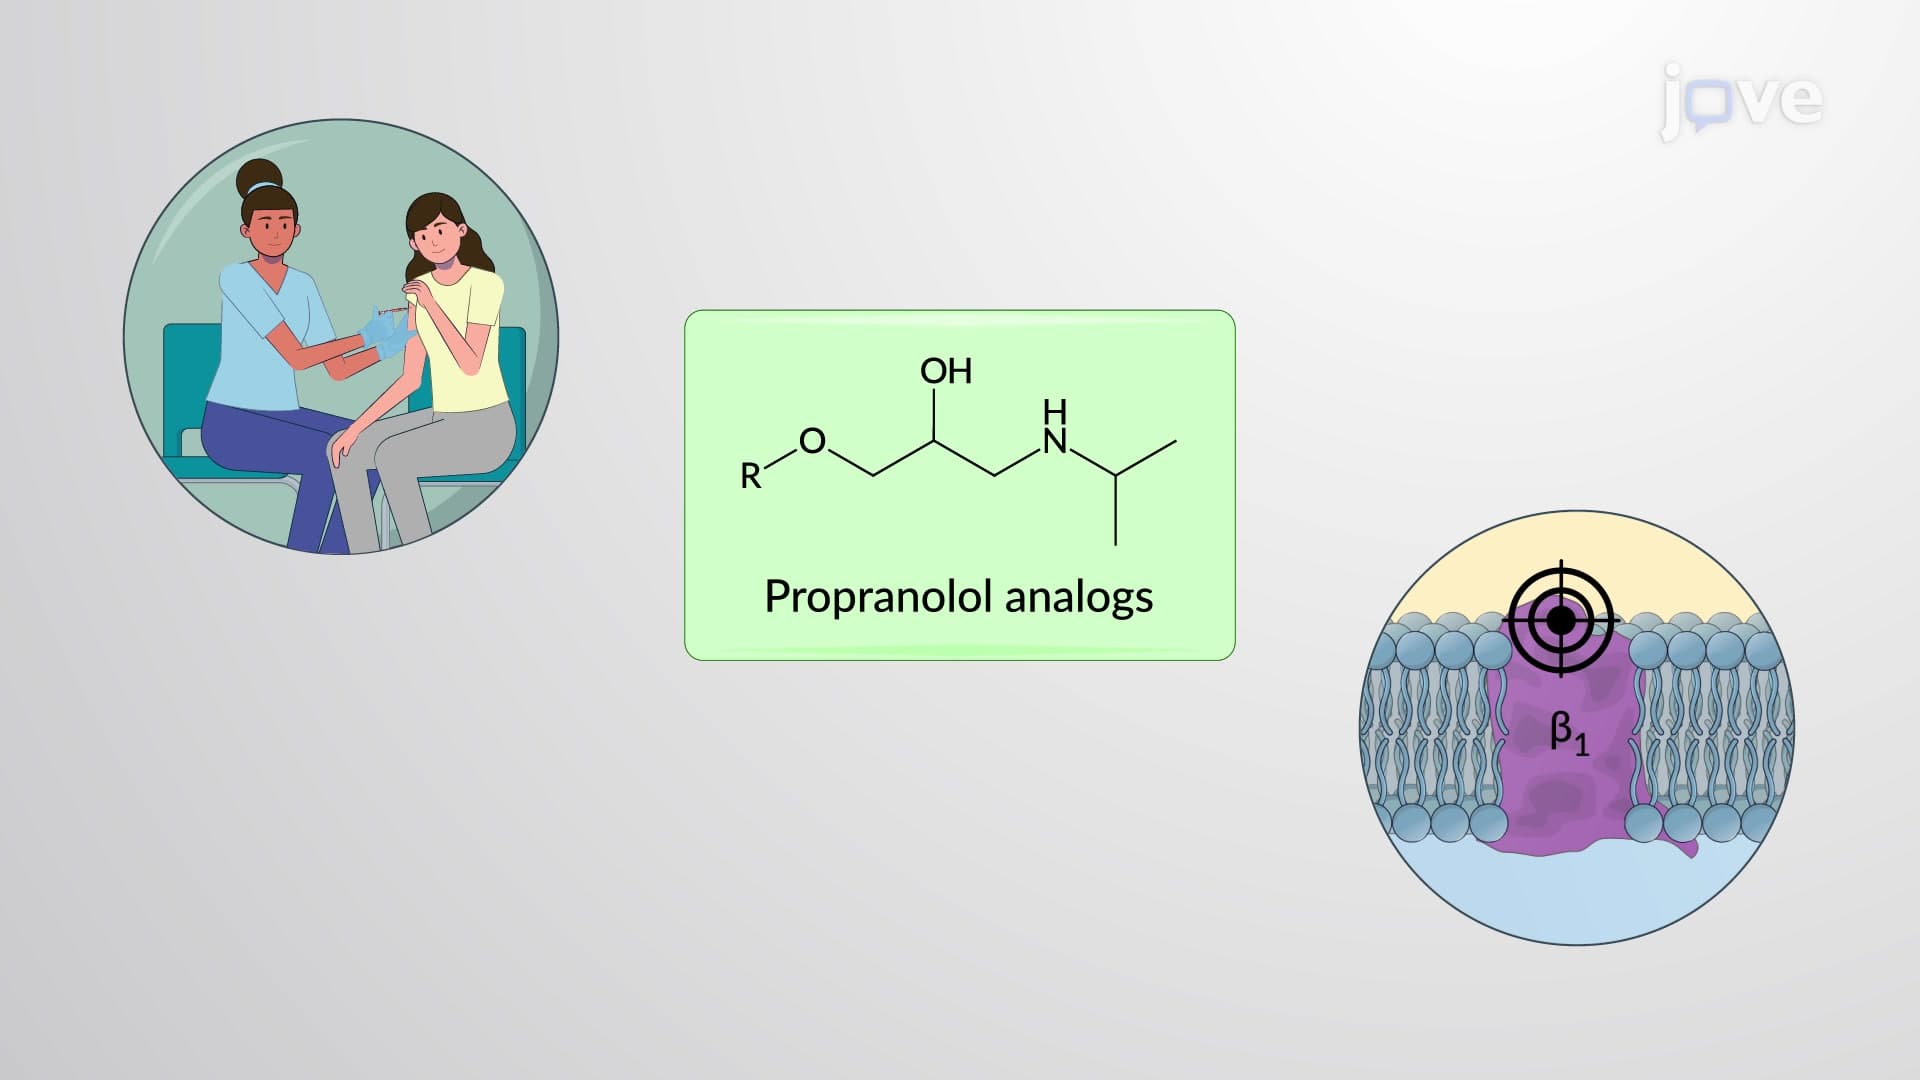 01:25
Adrenergic Antagonists: Chemistry and Classification of β-Receptor Blockers