Related Experiment Video
Updated: Sep 23, 2026
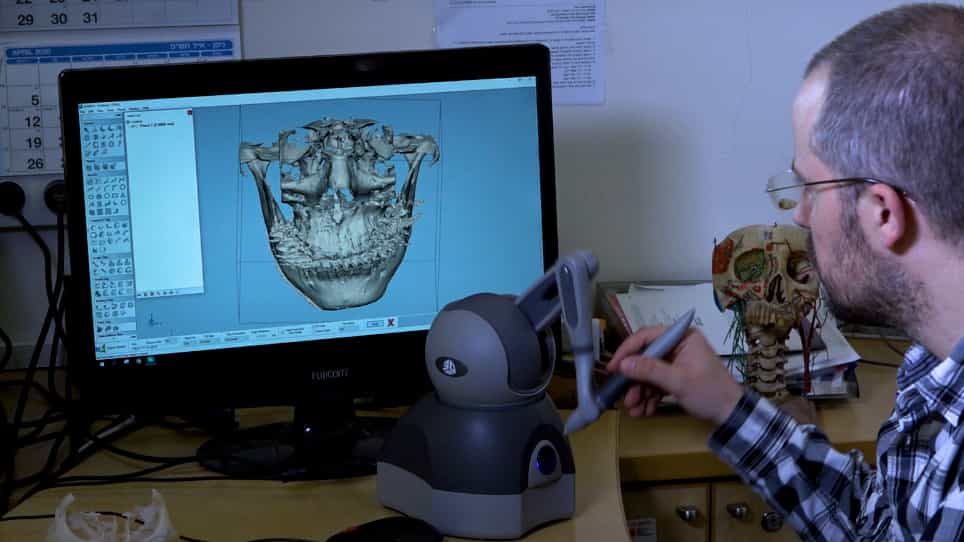

Treatment of Facial Deformities using 3D Planning and Printing of Patient-Specific Implants
Published on: May 23, 2020
Reduction malarplasty using osteotomy and repositioning of the malar complex: clinical review and comparison of two
1Department of Plastic and Recomnstructive Surgery, Kyungpook National University Hospital, Samduk 2 ga, 50, Daegu 700-721, Korea. bccho@knu.ac.kr

Abstract:
Twenty-five patients with a prominent zygoma underwent reduction malarplasty from January 1995 through January 2001. In mild cases, the osteotomized zygoma was repositioned superoposteriorly. In severe cases, after the removal of a 2- to 5-mm-thick bony segment, the osteotomized zygoma was repositioned medially and superoposteriorly. Ten patients underwent reduction malarplasty based on a bicoronal incision, whereas intraoral and preauricular incisions were used in the other 15 cases. Ten patients were male and 15 patients were female, with an age range from 18 to 52 years. The average follow-up was 13 months. All patients were satisfied with their results, and a symmetrical appearance was achieved in all cases. Reduction malarplasty using a bicoronal incision has various advantages because it provides a wide operative field, makes it easy to maintain symmetry, and facilitates combination with a forehead lift. Conversely, reduction malarplasty using an intraoral and preauricular incision has the advantages of a short operative time, simple procedure, and no scalp scar. Because the whole face should be regarded as one unit, the following adjutant procedures were also performed simultaneously: reduction of the mandibular angle in 17 patients, augmentation rhinoplasty in 4 patients, face lift in 2 patients, and fat graft in 2 patients. In conclusion, the procedure of osteotomy and repositioning the malar complex was found to be effective for correcting a prominent malar complex.
