Possible risks in combining endoscopic and surgical therapy of bleeding peptic ulcers
Related Experiment Video
Updated: Sep 23, 2026
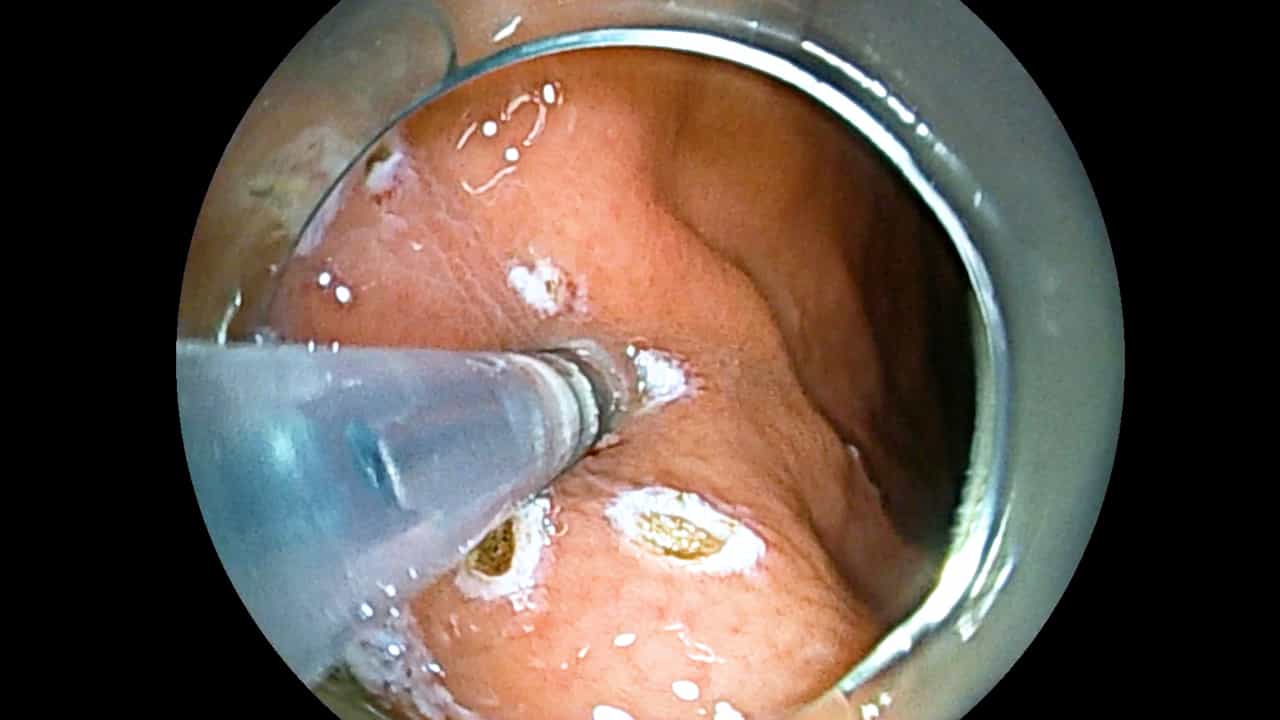
Evaluation of the Effectiveness of Longitudinal Incision for Endoscopic Submucosal Excavation of Gastric Subepithelial Lesions
Published on: April 28, 2026
J Olejnik1, P Labas, V Zahradnik
1Department of General Surgery, Derer's University Hospital, Slovak Postgraduate Academy of Medicine, Bratislava, Slovak Republic. olejnik@pobox.sk

Background/Aims:
Today's therapy of bleeding peptic ulcers consists of pharmacological hemostasis, endoscopic therapy and surgery in chronological order. The aim of this study was to objectively assess the contribution of the contemporary algorithm of therapy with the use of endoscopic and surgical hemostasis techniques for the therapy of bleeding peptic ulcers.
Methodology:
This study is a retrospective analysis and comparison of two randomized groups A/B with 427/388 patients with endoscopically verified bleeding from peptic ulcer lesions Forrest I-IIb. Patients in group A (1990-1993) were treated without endoscopic intervention, compared with group B patients (1998-2001) who were treated with endoscopic intervention. In both groups we have statistically scored and compared: quantitative operative therapy share, time interval from the beginning of therapy until surgery, APACHE II score of patients at the beginning of therapy and on the day of surgery, complications requiring re-operation and mortality.
Results:
In groups A/B surgical hemostasis was required in 15.0/10.6% cases, from which 90.6/61.0% operations were resections and bionomic operations. Data evaluation of APACHE II scores from both groups at the beginning of treatment showed no significant difference, but at the time of operative therapy the APACHE II scores were significantly higher in group B (11.83 +/- 6.49/15.00 +/- 4.36). The length of unstable intervals of bleeding in group B compared to group A was quantitatively lengthened (A = 55.6 +/- 19.8/B = 68.6 +/- 37.0 h). Significant differences were also noted in the number of re-operations 7.8/9.8% and mortality 15.6/24.3% between groups A/B.
Conclusions:
The contemporary accepted sequence of hemostatic therapy is accompanied by the risks of limited selection of optimal methods of endoscopic therapy, protracting the interval of bleeding with unfavorable rise in APACHE II score, and hesitancy in indication for surgery in intractable bleeding after non-surgical therapy.
Related Concept Videos
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:27
Peptic Ulcer
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to: