Related Experiment Video
Updated: Sep 23, 2026
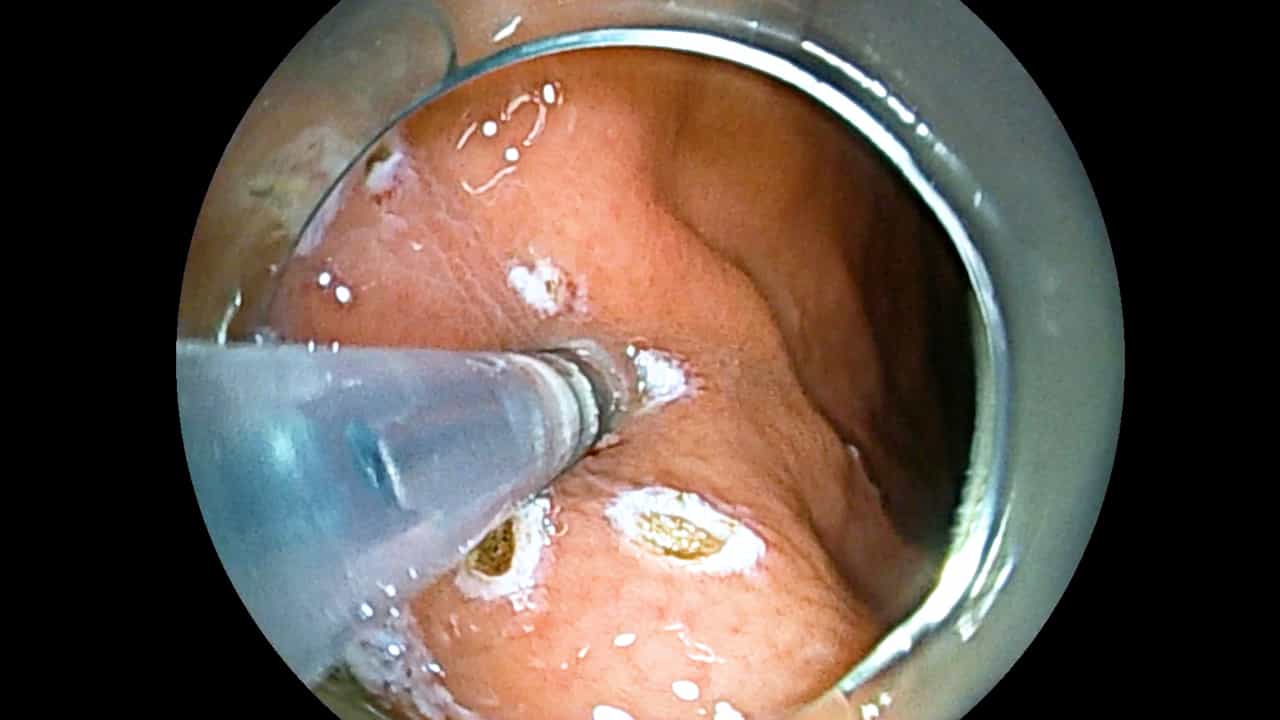

Evaluation of the Effectiveness of Longitudinal Incision for Endoscopic Submucosal Excavation of Gastric Subepithelial Lesions
Published on: April 28, 2026
A prospective randomized trial of two different endoscopic resection techniques for early stage cancer of the
Andrea May1, Liebwin Gossner, Angelika Behrens
1HSK Wiesbaden, Nuremberg, Germany.

Background:
A variety of different endoscopic resection techniques for early stage cancer of the upper GI tract have been described that are more effective than strip biopsy. However, there is no report of a prospective randomized comparison of different techniques.
Methods:
In a prospective randomized study, 100 consecutive endoscopic resections were performed in 72 patients with early stage esophageal cancer. Fifty endoscopic resections were performed with a "suck-and-ligate" device without prior submucosa injection and 50 with the cap technique with prior submucosa injection of a dilute saline solution of epinephrine. The main assessment criteria were maximum diameter of the resection specimen and of the resection area, and the complication rate.
Results:
No significant differences were observed between the two groups with regard to the maximum diameters and calculated area of the resected specimens (ligation group: 16.4 [4.0] x 11 [3.1] mm/185 [84] mm(2) vs. cap group: 15.5 [4.1] x 10.7 [2.7] mm/168 [83] mm(2)), or the maximum diameters and calculated area of the endoscopic resection ulcers after 24 hours (ligation group: 20.6 [4.8] x 14.3 [4.5] mm/314 [160] mm(2) vs. cap group: 18.9 [5.1] x 12.9 [3.8] mm/260 [145] mm(2)). There was only a slight advantage (greater diameter of resection specimens) for the ligation group in patients who had prior endoscopic treatment. There was one minor episode of bleeding in each group; there was no severe complication. In 41 of 72 patients (57%), further endoscopic therapy after endoscopic resection was necessary because of residual neoplasia at the first follow-up endoscopy after resection (61 of 100 resection specimens [61%] had lateral margins that could not be evaluated because of coagulation artifact or contained malignancy but with the base of the lesion free of tumor).
Conclusions:
The cap technique with submucosa injection and the ligation technique without submucosa injection are similar with respect to efficacy and safety for endoscopic resection of early stage esophageal cancers.
Related Concept Videos
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to:
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due to...