Related Experiment Video
Updated: Sep 6, 2026


LDL Cholesterol Uptake Assay Using Live Cell Imaging Analysis with Cell Health Monitoring
Published on: November 17, 2018
[Clinico-pharmacologic explanation models of cerivastatin associated rhabdomyolysis]
Markus Zeitlinger1, Markus Müller
1Universitätsklinik für Klinische Pharmakologie, Währinger Gürtel 18-20, A-1090 Wien.

Insights
Cerivastatin, a statin drug, was withdrawn due to fatal rhabdomyolysis. Its unique pharmacokinetic and pharmacodynamic properties, not shared by other statins, caused these severe side effects.
Area of Science:
- Pharmacology
- Drug Safety
- Clinical Medicine
Background:
- The HMG-CoA-reductase inhibitor cerivastatin was withdrawn globally in 2001 due to fatal rhabdomyolysis.
- This event raised safety concerns for the entire statin class, despite cerivastatin's higher incidence of severe side effects compared to other statins.
Purpose of the Study:
- To investigate the specific pharmacokinetic and pharmacodynamic characteristics of cerivastatin that led to its high frequency of fatal rhabdomyolysis.
- To differentiate the safety profile of cerivastatin from other statins.
Main Methods:
- Comparative analysis of pharmacokinetic properties (e.g., oral bioavailability, drug interactions) among statins.
- Evaluation of pharmacodynamic properties, specifically the IC50 for HMG-CoA-reductase inhibition.
- Assessment of potential mechanisms leading to skeletal muscle cell apoptosis and energy depletion.
Main Results:
- Cerivastatin exhibits the highest oral bioavailability and lowest IC50 for HMG-CoA-reductase inhibition within its class.
- Drug interactions, such as with gemfibrocil, can further elevate cerivastatin plasma levels.
- These factors contribute to apoptosis and energy depletion in skeletal muscle cells.
Conclusions:
- Fatal rhabdomyolysis associated with cerivastatin is attributed to its specific pharmacokinetic and pharmacodynamic profile, not a class-wide issue.
- The findings underscore the importance of ongoing clinical studies and precise adverse event reporting for all medications, including established ones.
Abstract:
Because of fatal cases of rhabdomyolysis the HMG-CoA-reductase inhibitor cerivastatin had to be withdrawn from the global market in 2001. The high frequency and severity of cerivastatin-associated rhabdomyolysis caused concerns about the safety of the entire class of HMG-CoA-reductase inhibitors (statins). Still, the frequency of deadly incidents of rhabdomyolysis with cerivastatin was 16 to 80 times higher than with other statins. This seems to be due to a combination of several pharmacokinetic and pharmacodynamic characteristics of cerivastatin. Cerivastatin shows the highest oral bioavailability within its class. Interactions with other drugs like gemfibrocil may cause further elevation of cerivastatin plasma levels, thereby leading to higher frequencies of side effects in peripheral organs. With approximately 1 pM cerivastatin shows the lowest IC50 for inhibition of HMG-CoA-reductase of all statins. The combination of high systemic drug levels and high intrinsic activity potentially leads to apoptosis and energy-depletion of skeletal-muscle cells. Therefore cerivastatin-associated fatal rhabdomyolysis seems to be based on specific pharmacokinetic and pharmacodynamic properties of cerivastatin, and is not a general characteristic of all members of this drug-class. The experiences with cerivastatin support the importance of clinical studies even about well established drugs, and underline the relevance of precise reporting of adverse events by each physician.


Related Concept Videos
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:20
Lipid-Lowering Drugs: Statins and Miscellaneous Agents
 01:15
Renal Drug Excretion: Overview
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules out...
 01:06
Renal Drug Clearance: Overview
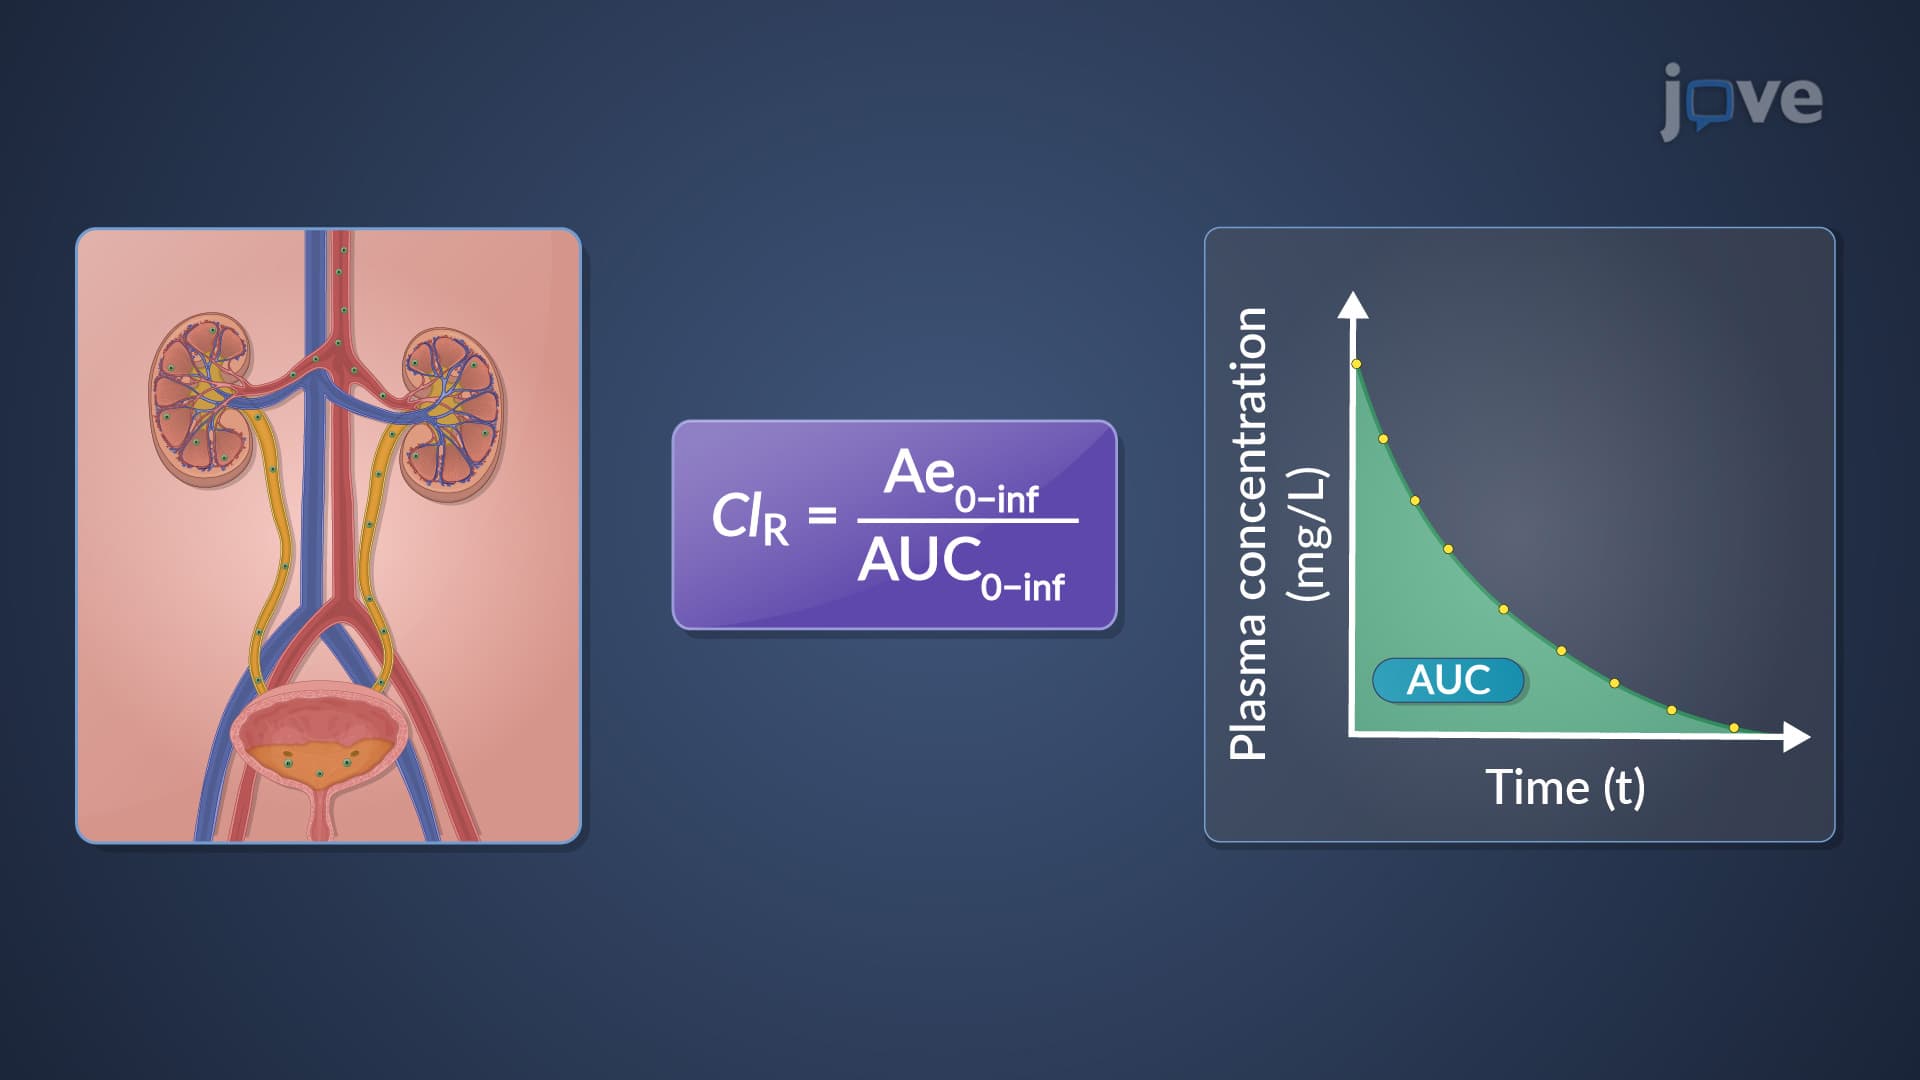
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:07
Physiological Pharmacokinetic Models: Incorporating Hepatic Transporter-Mediated Clearance
A recent model describes pravastatin's hepatobiliary excretion, mediated...
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions