Related Experiment Video
Updated: Sep 20, 2026
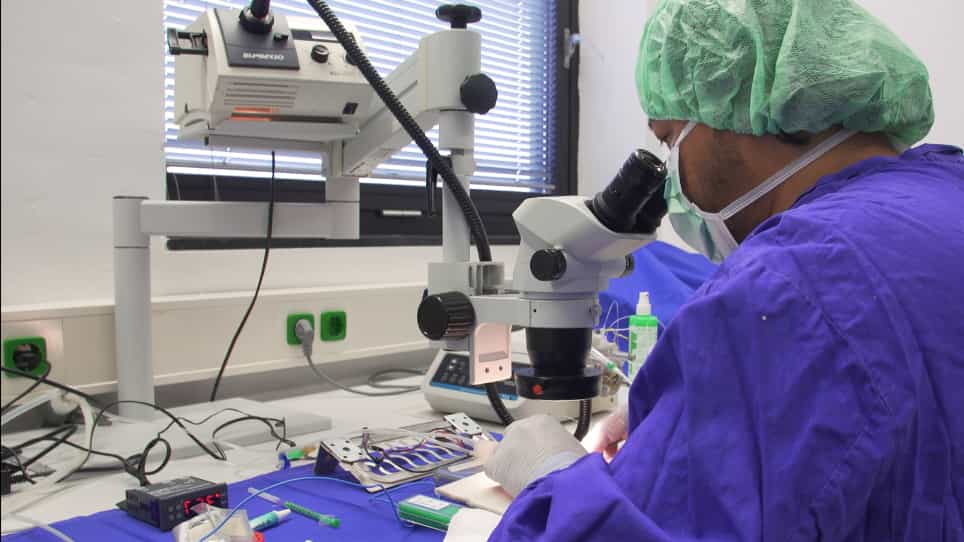

Veno-Venous Extracorporeal Membrane Oxygenation in a Mouse
Published on: October 24, 2018
Venovenous versus venoarterial extracorporeal membrane oxygenation in congenital diaphragmatic hernia
Amir Kugelman1, Ernesto Gangitano, Juan Pincros
1Department of Neonatology, Bnai-Zion Medical Center, Technion-Faculty of Medicine, Haifa, Israel.

Background:
Extracorporeal membrane oxygenation (ECMO) has a significant role as a final rescue modality in severe respiratory failure of the newborn with congenital diaphragmatic hernia (CDH). The objective of this study was to compare the efficiency of venovenous (VV) versus venoarterial (VA) ECMO in newborns with CDH.
Methods:
A retrospective report of 11 years experience (1990 through 2001) of a single center, comparing VV and VA ECMO is given. VV ECMO was the preferred rescue modality for respiratory failure unresponsive to maximal medical therapy. Only when the placement of a VV ECMO 14F catheter was not possible, VA ECMO was used. Forty-six patients met ECMO criteria; 26 were treated with VV ECMO and 19 with VA ECMO. One patient underwent conversion from VV to VA ECMO.
Results:
Before ECMO, there was no difference between VV and VA ECMO patients in mean oxygenation index (83 v 83), mean airway pressure (18.4 v 18.9 cm H(2)O), ECMO cannulation age (28 v 20 hours), or in the percentage of patients who needed dopamine and dobutamine (100% v 100%). From November 1994, nitric oxide (NO) was available; before ECMO, 11 of 14 (79%) VV ECMO patients received NO versus 9 of 10 (90%) patients in the VA group. VV ECMO patients were larger (3.34 v 2.77 kg; P <.05) and of advanced gestational age (39.0 v 36.9 wk; P <.05) compared with VA ECMO patients. There was no significant difference between VV and VA ECMO patients in survival rate (18 of 26, 69% v 13 of 19, 68%), ECMO duration (152 v 150 hours), time of extubation (32.0 v 33.5 days), age at discharge (73 v 81 days), or incidence of short-term intracranial complications (3.8% v 10.5%) or myocardial stun (3.8% v 15.8%).
Conclusions:
The authors conclude that VV ECMO is as reliable as VA ECMO in newborns with CDH in severe respiratory failure who need ECMO support and who can accommodate the VV double-lumen catheter. Because of its potential advantages, VV ECMO may be the preferred ECMO method in these infants.

Related Concept Videos
 01:14
Fetal Circulation
Two umbilical arteries transport blood from the fetus to the placenta. At the placenta, the blood absorbs oxygen and nutrients while simultaneously eliminating waste products. This oxygen-enriched and nutrient-rich blood then returns to the fetus through one...
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:25
Hemodialysis I: Introduction