Related Experiment Videos
Vancomycin use in hospitalized pediatric patients
Harry L Keyserling1, Ronda L Sinkowitz-Cochran, James M Harris
1Department of Pediatrics, Emory University School of Medicine, Atlanta, Georgia 30322, USA. hkeyser@emory.edu

Insights
Vancomycin is frequently used in children
Area of Science:
- Pediatric Infectious Diseases
- Antimicrobial Stewardship
- Hospital Epidemiology
Background:
- Vancomycin is a critical antibiotic for treating serious infections, but its use requires careful management to prevent resistance.
- Optimizing vancomycin prescribing practices in pediatric settings is essential for effective treatment and antimicrobial stewardship.
Purpose of the Study:
- To evaluate vancomycin utilization patterns in children's hospitals.
- To identify risk factors associated with vancomycin use and duration of therapy.
- To inform recommendations for optimizing vancomycin prescribing in pediatric patients.
Main Methods:
- Two surveys were administered to hospitals within the Pediatric Prevention Network.
- Survey I assessed hospital vancomycin control programs and policies.
- Survey II prospectively reviewed 416 vancomycin courses in 22 hospitals.
Main Results:
- Most hospitals (85%) had policies restricting vancomycin use.
- Vancomycin was primarily prescribed for neonatal sepsis, fever/neutropenia, and positive blood cultures (82%).
- Vascular catheters (77%) were the predominant risk factor for initiation, with limited laboratory confirmation of resistant organisms (7%).
Conclusions:
- Vancomycin initiation in children's hospitals often involves patients with vascular catheters and compromised immunity.
- Targeted interventions should focus on intensivists, neonatologists, and hematologists to modify empiric use.
- Reducing prophylaxis duration and optimizing therapy based on lab results can decrease vancomycin exposure.
Objectives:
To assess vancomycin utilization at children's hospitals, to determine risk factors for vancomycin use and length of therapy, and to facilitate adapting recommendations to optimize vancomycin prescribing practices in pediatric patients.
Methods:
Two surveys were conducted at Pediatric Prevention Network hospitals. The first (Survey I) evaluated vancomycin control programs. The second (Survey II) prospectively reviewed individual patient records. Each hospital was asked to complete questionnaires on 25 consecutive patients or all patients for whom vancomycin was prescribed during a 1-month period.
Results:
In Survey I, 55 of 65 (85%) hospitals reported their vancomycin control policies. Three quarters had specific policies in place to restrict vancomycin use. One half had at least 3 vancomycin restriction measures. In Survey II, personnel at 22 hospitals reviewed 416 vancomycin courses, with 2 to 25 (median = 12) patients tracked per hospital. Eighty-two percent of the vancomycin prescribed was for treatment of neonatal sepsis, fever/neutropenia, fever of unknown origin, positive blood culture, pneumonia, or meningitis. In an additional 6% (26/416), vancomycin was prescribed for patients with beta-lactam allergies and in 13% (56/416) for prophylaxis. Median duration of prophylaxis was 2 days (range: 1-15 days). Almost half (196, 47%) of the patients who received vancomycin were in intensive care units; 27% of the vancomycin courses were initiated by neonatologists and 19% by hematologists/oncologists. The predominant risk factor at the time of vancomycin initiation was the presence of vascular catheters (322, 77%); other host factors included cancer chemotherapy (55, 13%), transplant (30, 7%), shock (24, 6%), other immunosuppressant therapy (17, 4%), or hyposplenic state (2, <1%). Other clinical considerations were severity of illness (96, 23%), uncertainty about diagnosis (51, 12%), patient not responding to current antibiotic therapy (40, 10%), or implant infection (13, 3%). When vancomycin was initiated, blood cultures were positive in 85 patients (20%); cultures from other sites were positive in 45 (11%), and Gram stains of body fluids were positive in 37 (9%). In 29 (7%) patients, organisms sensitive only to vancomycin were isolated before vancomycin initiation. Reasons for discontinuing vancomycin included: therapeutic course completed (125, 30%), negative cultures (106, 25%), alternative antibiotics initiated (75, 18%), illness resolved (14, 3%), or patient expired (13, 3%). Final results of blood culture isolates resistant to beta-lactam antibiotics included 48 coagulase-negative staphylococcus, 5 Staphylococcus aureus, and 10 other species.
Conclusions:
At children's hospitals, vancomycin is initiated for therapy in patients who have vascular catheters and compromised host factors. Only 7% had laboratory-confirmed beta-lactam-resistant organisms isolated at the time vancomycin was prescribed. Efforts to modify empiric vancomycin use in children's hospitals should be targeted at intensivists, neonatologists, and hematologists. Initiatives to decrease length of therapy by decreasing the number of surgical prophylaxis doses and days of therapy before laboratory results may decrease vancomycin exposure.
Related Concept Videos
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:29
Drug Dosing: Infants and Children
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:20
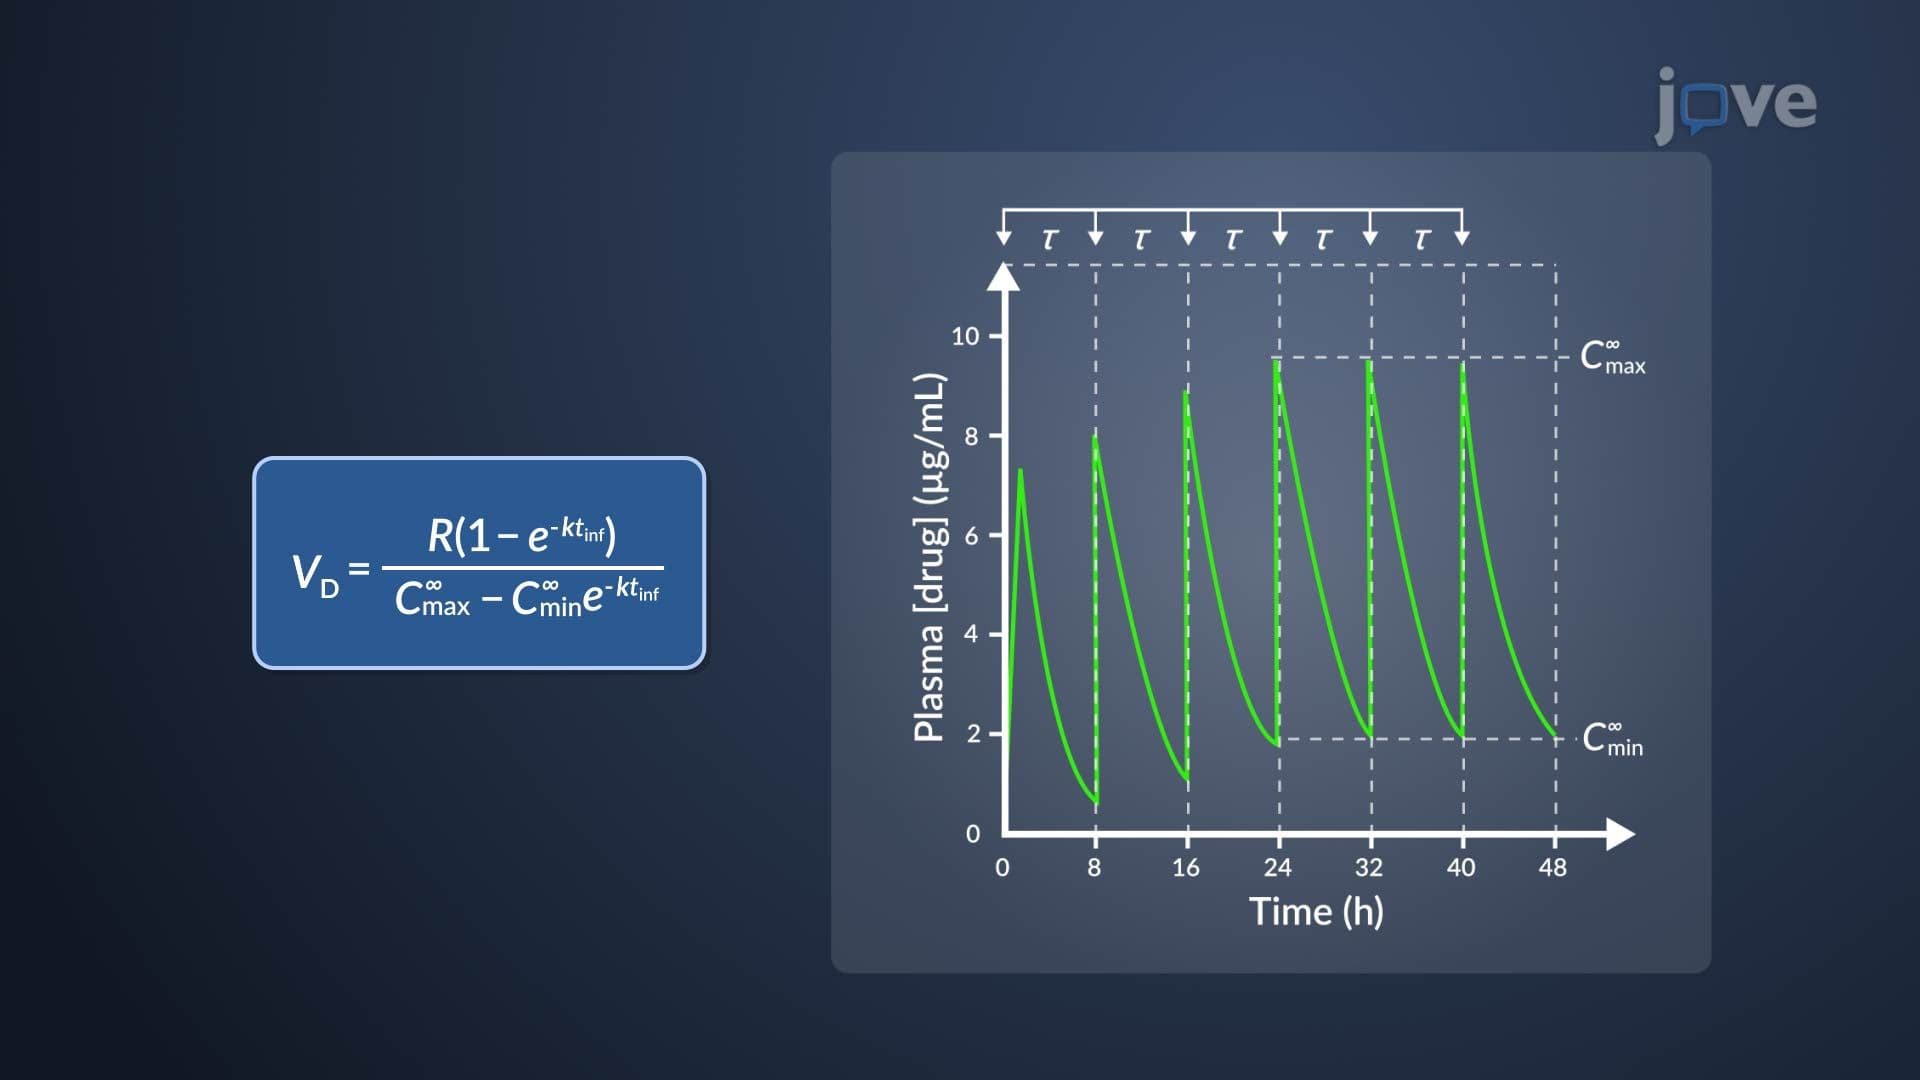
Estimation of k and VD of Aminoglycosides