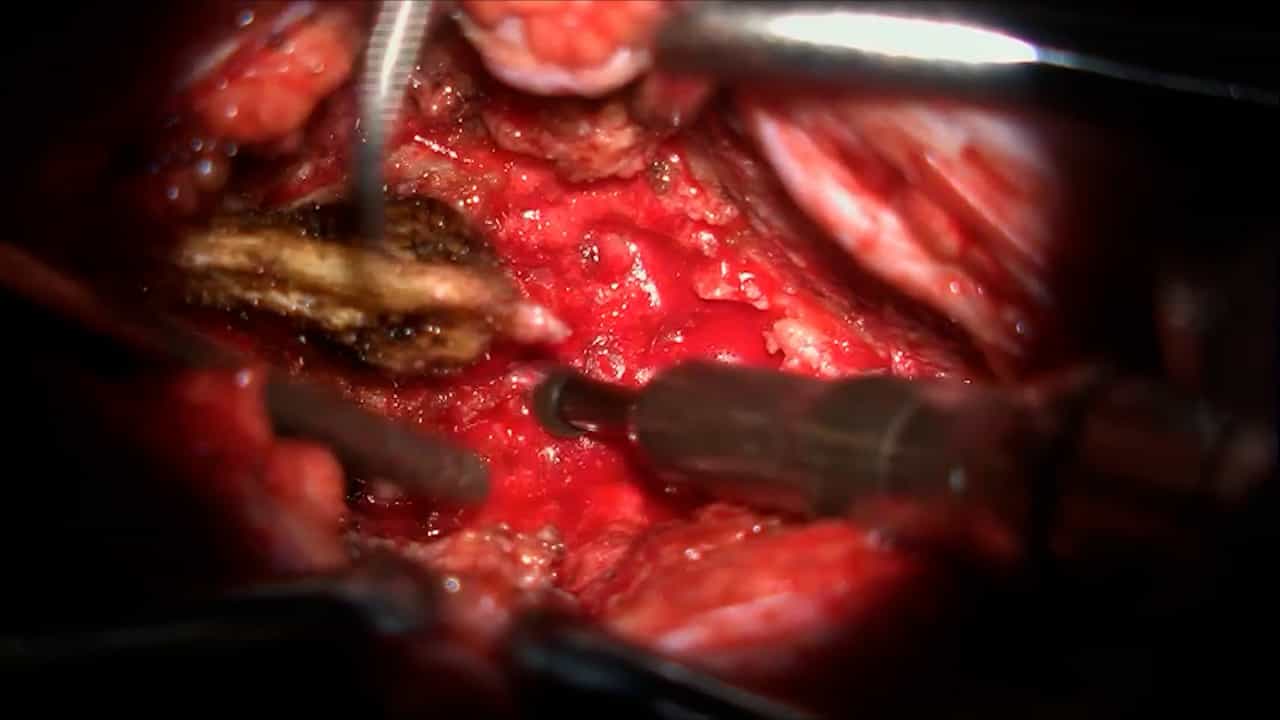
Hemorrhagic rectal ulcer caused by a deformity of the coccyx complicated by normal delivery
Toshimichi Kaneki1, Shigeru Koyama, Shuichi Wada
1Department of Internal Medicine, Nagano Red Cross Hospital, 5-22-1 Wakasato, Nagano 380-8582, Japan.

A 25-year-old woman delivered her first-born child weighing 3400 g by full-term normal delivery. Bloody stool developed 3 days after delivery. Colonoscopic examination revealed two linear ulcers parallel to the anal column on the posterior side of the rectal ampulla about 5 cm from the anal ring. Coagulated blood was detected at the ulcer bottom, suggesting the site of hemorrhage. Bowel rest in the absence of oral intake resulted in the disappearance of bloody stool. Three days later colonoscopic examination revealed improvement in the ulcer. There was no sign of constipation. A lateral pelvic radiograph showed that the apex of the coccyx was flexed anteriorly. The parturient canal may have physically pressed the rectum against the apex of the coccyx during delivery, causing mucosal injury. Only a few studies have reported the complication of a rectal ulcer due to injury during delivery. Furthermore, none of the previous studies has reported a rectal ulcer caused by deformity of the coccyx.
A 25-year-old woman delivered her first-born child weighing 3400 g by full-term normal delivery. Bloody stool developed 3 days after delivery. Colonoscopic examination revealed two linear ulcers parallel to the anal column on the posterior side of the rectal ampulla about 5 cm from the anal ring. Coagulated blood was detected at the ulcer bottom, suggesting the site of hemorrhage. Bowel rest in the absence of oral intake resulted in the disappearance of bloody stool. Three days later colonoscopic examination revealed improvement in the ulcer. There was no sign of constipation. A lateral pelvic radiograph showed that the apex of the coccyx was flexed anteriorly. The parturient canal may have physically pressed the rectum against the apex of the coccyx during delivery, causing mucosal injury. Only a few studies have reported the complication of a rectal ulcer due to injury during delivery. Furthermore, none of the previous studies has reported a rectal ulcer caused by deformity of the coccyx.
Related Concept Videos
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:27
Diverticular Disease of the Colon
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...
 01:24
Esophageal Varices-I: Introduction
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:07
Intestinal Obstruction II: Pathophysiology