Related Experiment Video
Updated: Sep 20, 2026


Endoscopic Bilateral Nipple-sparing Mastectomy via a Single Axillary Incision with Immediate Pre-pectoral Implant-based Breast Reconstruction
Published on: May 17, 2024
Infectious complications following breast reconstruction with expanders and implants
Maurice Y Nahabedian1, Theodore Tsangaris, Bahram Momen
1Department of Surgery, Johns Hopkins Medical Institutions, Baltimore, Maryland 21287, USA. mnahabed@jhmi.edu

The incidence of infection following breast reconstruction with expanders and implants ranges from 1 to 24 percent. Numerous factors associated with infection have been described; however, a one-variable at time setting and multifactorial analysis have not been performed. The purpose of this study was to analyze a set of factors that may predispose women to infection of the expander or implant. Between 1997 and 2000, a total of 168 implant reconstructions were performed in 130 women at a single institution. The mean age for all women was 48.2 years (range, 25 to 77 years). The factors that were analyzed included axillary lymph node dissection, chemotherapy, radiation therapy, tumor stage, timing of implant insertion, number of sides (unilateral versus bilateral), tobacco use, and presence or absence of diabetes mellitus. Statistical analysis was performed with stepwise logistic regression. Mean time to follow-up for all patients was 29 months (range, 12 to 47 months). Infectious complications occurred in 10 women (7.7 percent) and in 10 expanders or implants (5.9 percent). Infected implants were removed an average of 116 days following insertion (range, 14 to 333 days). Cultured bacteria included Staphylococcus aureus and Serratia marcescens. A significant association (p < 0.04) was detected between implant infection and radiation therapy. The chance for implant infection was 4.88 times greater for implants that were exposed to radiation therapy compared with those that were not. In addition, there was suggestive (p < 0.09) evidence that the chance of implant infection following lymph node dissection was 6.29 times higher than when no lymph nodes were removed. No significant association between implant infection and age, diabetes, tobacco use, tumor stage, timing of implant insertion, or chemotherapy was found.
The incidence of infection following breast reconstruction with expanders and implants ranges from 1 to 24 percent. Numerous factors associated with infection have been described; however, a one-variable at time setting and multifactorial analysis have not been performed. The purpose of this study was to analyze a set of factors that may predispose women to infection of the expander or implant. Between 1997 and 2000, a total of 168 implant reconstructions were performed in 130 women at a single institution. The mean age for all women was 48.2 years (range, 25 to 77 years). The factors that were analyzed included axillary lymph node dissection, chemotherapy, radiation therapy, tumor stage, timing of implant insertion, number of sides (unilateral versus bilateral), tobacco use, and presence or absence of diabetes mellitus. Statistical analysis was performed with stepwise logistic regression. Mean time to follow-up for all patients was 29 months (range, 12 to 47 months). Infectious complications occurred in 10 women (7.7 percent) and in 10 expanders or implants (5.9 percent). Infected implants were removed an average of 116 days following insertion (range, 14 to 333 days). Cultured bacteria included Staphylococcus aureus and Serratia marcescens. A significant association (p < 0.04) was detected between implant infection and radiation therapy. The chance for implant infection was 4.88 times greater for implants that were exposed to radiation therapy compared with those that were not. In addition, there was suggestive (p < 0.09) evidence that the chance of implant infection following lymph node dissection was 6.29 times higher than when no lymph nodes were removed. No significant association between implant infection and age, diabetes, tobacco use, tumor stage, timing of implant insertion, or chemotherapy was found.
Related Concept Videos
 01:24
Healing II: Complications
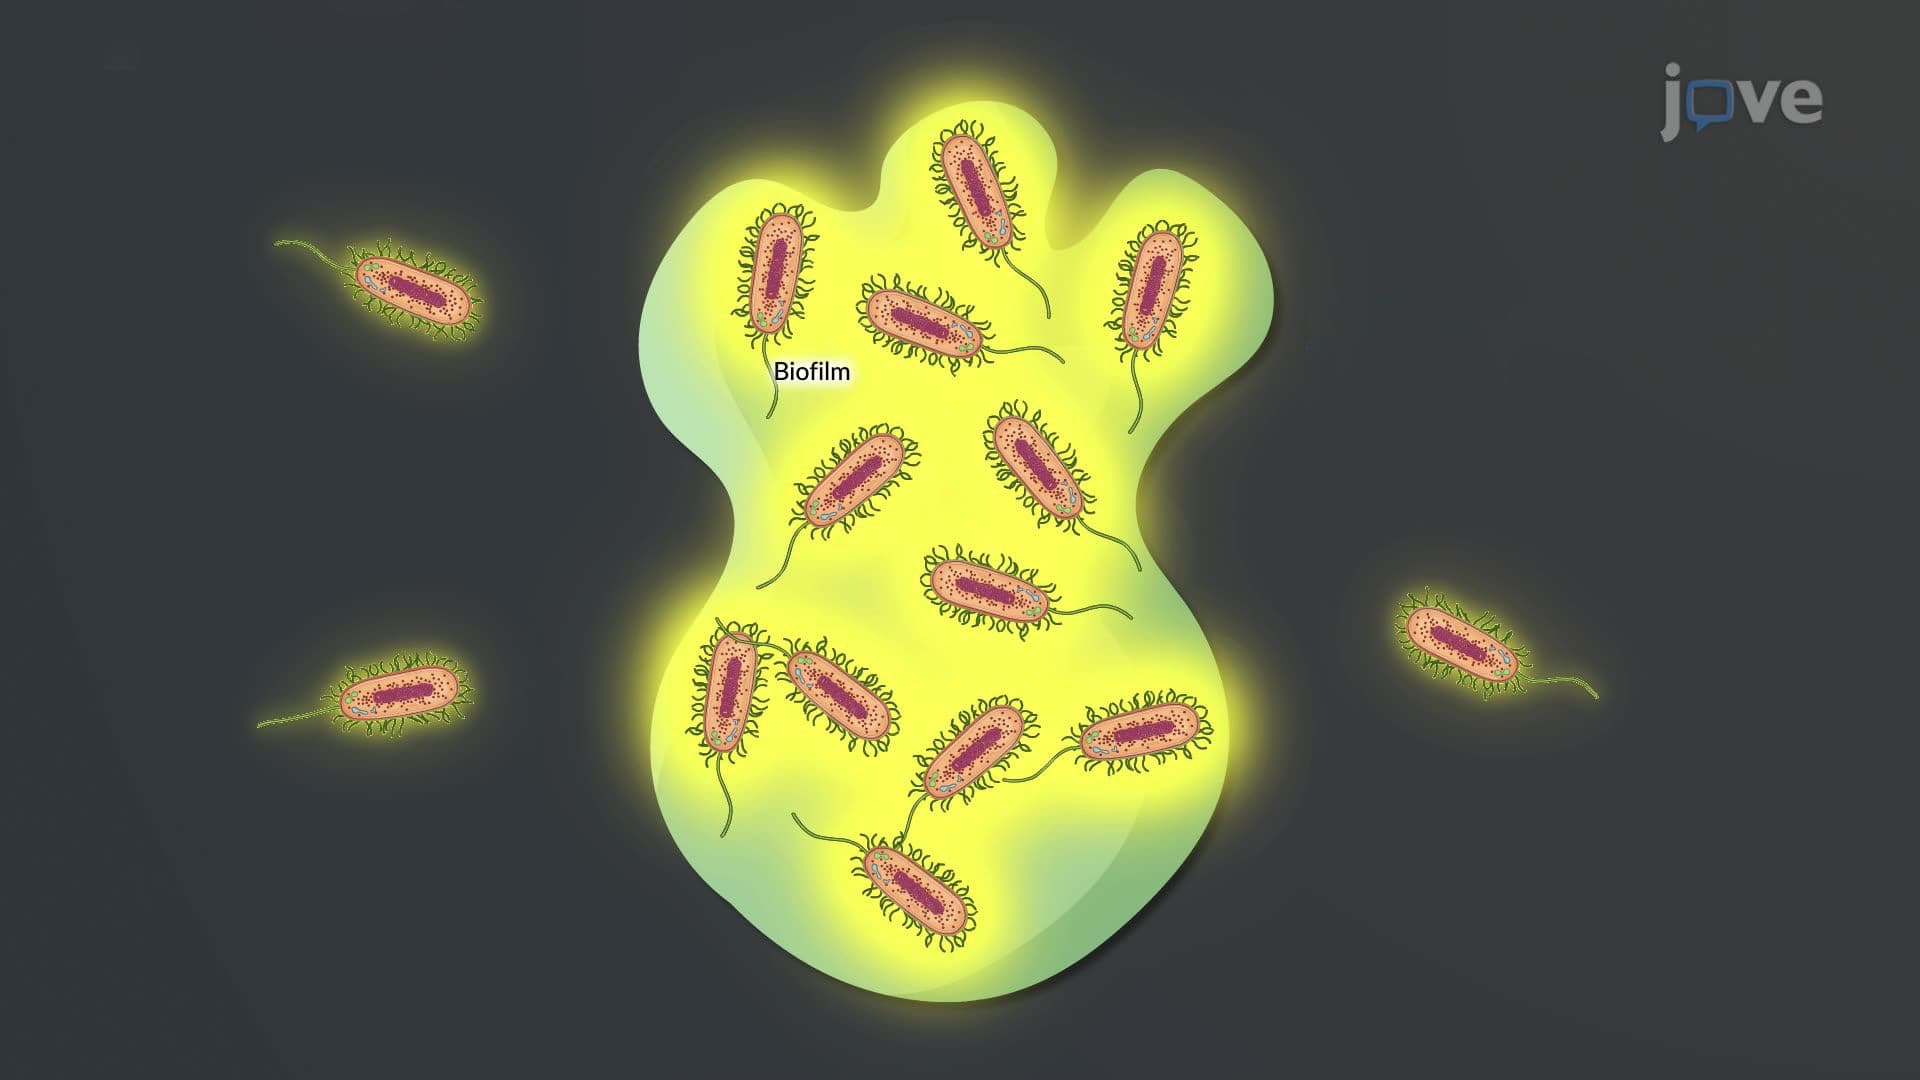 01:50
Bacterial Signaling
 01:29
Endocarditis IV: Nursing Management
 01:26
Aneurysm III: Interprofessional Care
 01:26
Healthcare Associated Infections I: Iatrogenic, Exogenic and Endogenic
HAIs significantly increase the cost of health care. Extended stays in healthcare institutions, increased disability, increased costs of medications, including specialized antibiotics, and prolonged recovery times add to the patient's expenses and the healthcare institution and funding bodies. Common...