Related Experiment Video
Updated: May 5, 2026
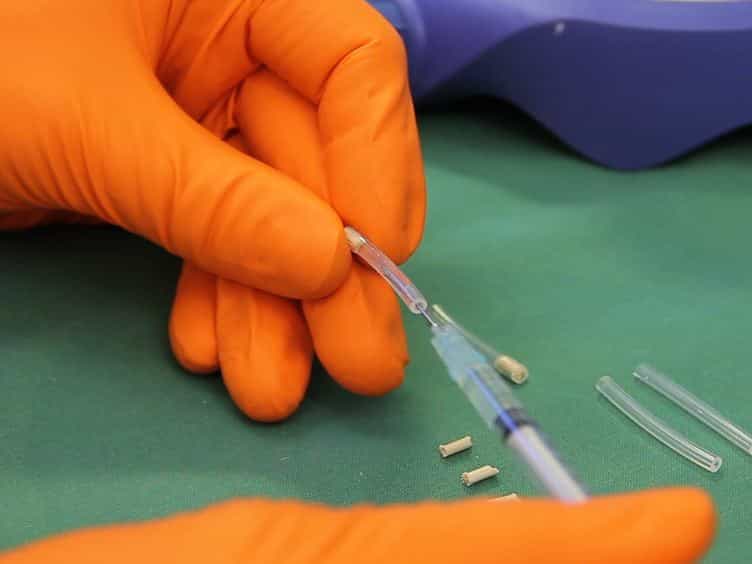

Ovariectomy and 17β-estradiol Replacement in Rats and Mice: A Visual Demonstration
Published on: June 7, 2012
Estrogen plus progestin and the risk of coronary heart disease
JoAnn E Manson1, Judith Hsia, Karen C Johnson
1Division of Preventive Medicine, Brigham and Women's Hospital and Harvard Medical School, Boston, MA 02215, USA. jmanson@rics.bwh.harvard.edu

Background:
Recent randomized clinical trials have suggested that estrogen plus progestin does not confer cardiac protection and may increase the risk of coronary heart disease (CHD). In this report, we provide the final results with regard to estrogen plus progestin and CHD from the Women's Health Initiative (WHI).
Methods:
The WHI included a randomized primary-prevention trial of estrogen plus progestin in 16,608 postmenopausal women who were 50 to 79 years of age at base line. Participants were randomly assigned to receive conjugated equine estrogens (0.625 mg per day) plus medroxyprogesterone acetate (2.5 mg per day) or placebo. The primary efficacy outcome of the trial was CHD (nonfatal myocardial infarction or death due to CHD).
Results:
After a mean follow-up of 5.2 years (planned duration, 8.5 years), the data and safety monitoring board recommended terminating the estrogen-plus-progestin trial because the overall risks exceeded the benefits. Combined hormone therapy was associated with a hazard ratio for CHD of 1.24 (nominal 95 percent confidence interval, 1.00 to 1.54; 95 percent confidence interval after adjustment for sequential monitoring, 0.97 to 1.60). The elevation in risk was most apparent at one year (hazard ratio, 1.81 [95 percent confidence interval, 1.09 to 3.01]). Although higher base-line levels of low-density lipoprotein cholesterol were associated with an excess risk of CHD among women who received hormone therapy, higher base-line levels of C-reactive protein, other biomarkers, and other clinical characteristics did not significantly modify the treatment-related risk of CHD.
Conclusions:
Estrogen plus progestin does not confer cardiac protection and may increase the risk of CHD among generally healthy postmenopausal women, especially during the first year after the initiation of hormone use. This treatment should not be prescribed for the prevention of cardiovascular disease.
More Related Videos
 06:18
An In Vivo Estrogen Deficiency Mouse Model for Screening Exogenous Estrogen Treatments of Cardiovascular Dysfunction After Menopause
Published on: August 13, 2019
 10:03
Coronary Progenitor Cells and Soluble Biomarkers in Cardiovascular Prognosis after Coronary Angioplasty
Published on: January 28, 2020
Related Concept Videos
 01:20
Antiplatelet Drugs: Prostaglandin Synthesis, P2Y12 and Glycoprotein IIb/IIIa Inhibitors
Prostaglandin synthesis inhibitors, exemplified by the widely known aspirin, wield their power by irreversibly acetylating...
 01:23
Treatment for Pulmonary Arterial Hypertension: Prostacyclin Receptor Agonists
These agonists bind to the IPR receptor situated on the plasma membrane of the pulmonary artery smooth muscle cells. This binding triggers a cascade of reactions known as the GS-AC-cAMP-PKA pathway. This pathway results in the relaxation of smooth muscle...
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...
 01:26
Coronary Artery Disease II: Pathophysiology
 01:26
Coronary Artery Disease IV: Preventive Measures
 01:27
Coronary Artery Disease V: Interprofessional Care