Related Experiment Video
Updated: Aug 13, 2026


A Method of Nodose Ganglia Injection in Sprague-Dawley Rat
Published on: November 25, 2014
Bimodal delta-opioid receptors regulate vagal bradycardia in canine sinoatrial node
M Farias1, K Jackson, D Yoshishige
1Department of Integrative Physiology, Cardiovascular Research Institute, University of North Texas Health Science Center, 3500 Camp Bowie Blvd., Fort Worth, TX 76107, USA.

Abstract:
Methionine-enkephalin-arginine-phenylalanine (MEAP) introduced into the interstitium of the canine sinoatrial (SA) node by microdialysis interrupts vagal bradycardia. In contrast, raising endogenous MEAP by occluding the SA node artery improves vagal bradycardia. Both are blocked by the same delta-selective antagonist, naltrindole. We tested the hypothesis that vagal responses to intranodal enkephalin are bimodal and that the polarity of the response is both dose- and opioid receptor subtype dependent. Ultralow doses of MEAP were introduced into the canine SA node by microdialysis. Heart rate frequency responses were constructed by stimulating the right vagus nerve at 1, 2, and 3 Hz. Ultralow MEAP infusions produced a 50-100% increase in bradycardia during vagal stimulation. Maximal improvement was observed at a dose rate of 500 fmol/min with an ED50 near 50 fmol/min. Vagal improvement was returned to control when MEAP was combined with the delta-antagonist naltrindole. The dose of naltrindole (500 fmol/min) was previously determined as ineffective vs. the vagolytic effect of higher dose MEAP. When MEAP was later reintroduced in the same animals at nanomoles per minute, a clear vagolytic response was observed. The delta1-selective antagonist 7-benzylidenenaltrexone (BNTX) reversed the vagal improvement with an ED50 near 1 x 10-21 mol/min, whereas the delta2-antagonist naltriben had no effect through 10-9 mol/min. Finally, the improved vagal bradycardia previously associated with nodal artery occlusion and endogenous MEAP was blocked by the selective delta1-antagonist BNTX. These data support the hypothesis that opioid effects within the SA node are bimodal in character, that low doses are vagotonic, acting on delta1-receptors, and that higher doses are vagolytic, acting on delta2-receptors.
Insights
Methionine-enkephalin-arginine-phenylalanine (MEAP) exhibits dual effects on vagal bradycardia in the SA node. Low doses enhance vagal responses via delta1-receptors, while high doses inhibit them through delta2-receptors.
Area of Science:
- Cardiovascular Physiology
- Neuropharmacology
- Opioid Receptor Research
Background:
- The sinoatrial (SA) node's response to vagal nerve stimulation is crucial for heart rate regulation.
- Endogenous opioids, like methionine-enkephalin-arginine-phenylalanine (MEAP), are present in the SA node, but their precise role in vagal modulation is unclear.
- Previous studies showed conflicting effects of MEAP on vagal bradycardia, suggesting a complex regulatory mechanism.
Purpose of the Study:
- To investigate the hypothesis that intranodal enkephalin responses are bimodal, depending on dose and opioid receptor subtype.
- To determine the specific opioid receptor subtypes (delta1 vs. delta2) mediating the dose-dependent effects of MEAP on vagal bradycardia.
- To elucidate the mechanism by which endogenous MEAP influences vagal responses in the SA node.
Main Methods:
- Microdialysis was used to introduce varying doses of MEAP into the canine SA node.
- Vagal nerve stimulation at different frequencies (1, 2, 3 Hz) was performed to assess heart rate responses.
- Selective opioid receptor antagonists, naltrindole (delta-selective), 7-benzylidenenaltrexone (BNTX, delta1-selective), and naltriben (delta2-selective), were used to block receptor activity.
- SA node artery occlusion was employed to increase endogenous MEAP levels.
Main Results:
- Ultralow doses of MEAP (fmol/min range) significantly increased vagal bradycardia (50-100% enhancement), acting via delta1-receptors as indicated by BNTX blockade.
- Higher doses of MEAP (nmol/min range) induced a vagolytic (inhibitory) effect, which was not blocked by the delta2-selective antagonist naltriben.
- The vagotonic effect of ultralow MEAP was reversed by naltrindole, while the vagolytic effect of higher MEAP doses was not specified in relation to receptor subtypes.
- Increased endogenous MEAP (via artery occlusion) led to improved vagal bradycardia, which was blocked by the delta1-selective antagonist BNTX.
Conclusions:
- Opioid signaling within the SA node exhibits a bimodal response pattern to MEAP.
- Low doses of MEAP act as vagotonic agents, enhancing vagal bradycardia through activation of delta1-opioid receptors.
- Higher doses of MEAP function as vagolytic agents, inhibiting vagal bradycardia, potentially through delta2-opioid receptors, although this requires further investigation.


Related Concept Videos
 01:21
G-Protein Gated Ion Channels
Sensory organs,...
 01:28
Drugs Acting on Autonomic Ganglia: Blockers
 01:26
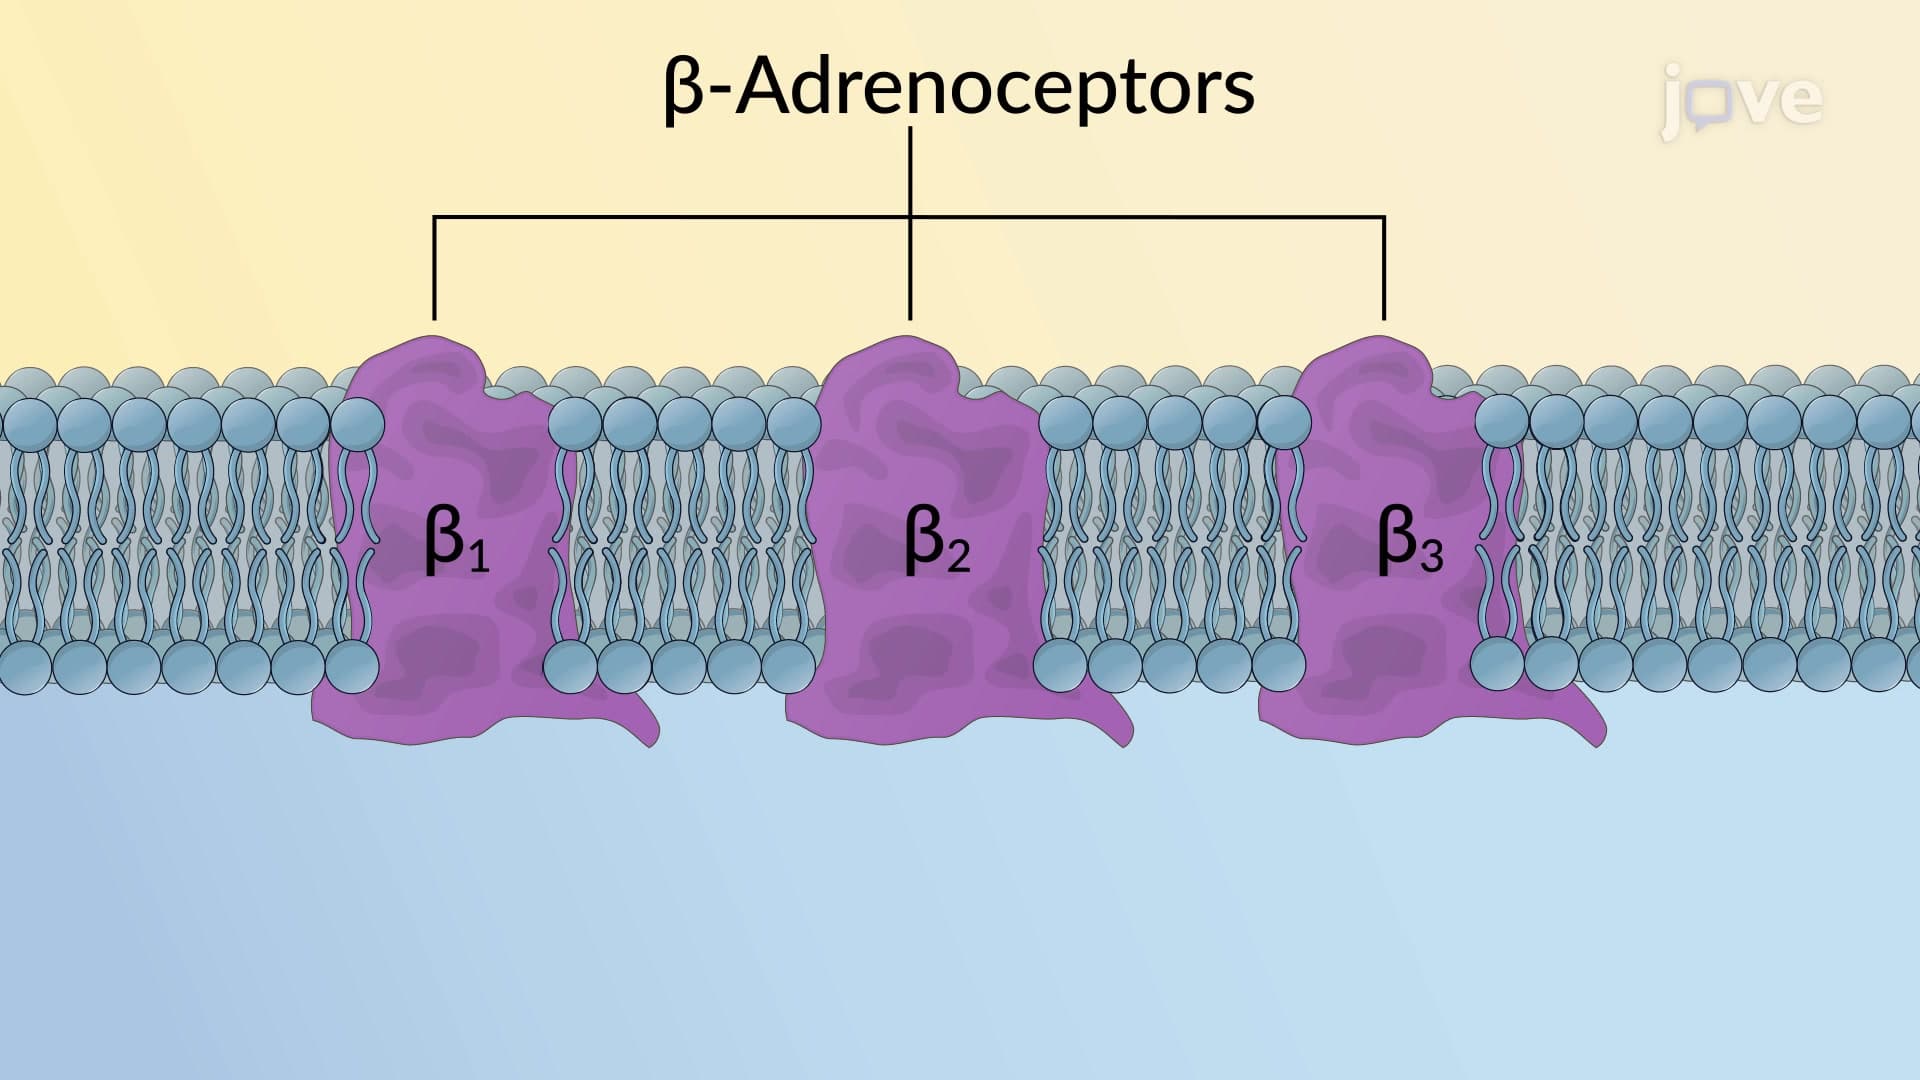
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:19
Conduction System of the Heart
The pacemaker cells are located in two primary nodes: the sinoatrial (SA) node and the atrioventricular (AV) node. The SA node pacemaker cells can autonomously depolarize, triggering an action potential that leads to the...
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias