Related Experiment Video
Updated: Aug 17, 2026

An Affordable HIV-1 Drug Resistance Monitoring Method for Resource Limited Settings
Published on: March 30, 2014
Randomized trial to evaluate indinavir/ritonavir versus saquinavir/ritonavir in human immunodeficiency virus type
Ulrik Bak Dragsted1, Jan Gerstoft, Court Pedersen
1Hvidovre University Hospital, Hvidovre, Denmark. ubd@cphiv.dk

This trial assessed the rate of virological failure at 48 weeks in adult human immunodeficiency virus (HIV) type 1-infected patients assigned indinavir/ritonavir (Idv/Rtv; 800/100 mg 2 times daily) or saquinavir/ritonavir (Sqv/Rtv; 1000/100 mg 2 times daily) in an open-label, randomized (1:1), multicenter, phase 4 design. Three hundred six patients began the assigned treatment. At 48 weeks, virological failure was seen in 43 (27%) of 158 and 37 (25%) of 148 patients in the Idv/Rtv and Sqv/Rtv arms, respectively. The time to virological failure did not differ between study arms (P=.76). When switching from randomized treatment was counted as failure, this was seen in 78 of 158 patients in the Idv/Rtv arm, versus 51 of 148 patients in the Sqv/Rtv arm (P=.009). A switch from the randomized treatment occurred in 64 (41%) of 158 patients in the Idv/Rtv arm, versus 40 (27%) of 148 patients in the Sqv/Rtv arm (P=.013). Sixty-four percent of the switches occurred because of adverse events. A greater number of treatment-limiting adverse events were observed in the Idv/Rtv arm, relative to the Sqv/Rtv arm. In conclusion, Rtv-boosed Sqv and Idv were found to have comparable antiretroviral effects in the doses studied.
This trial assessed the rate of virological failure at 48 weeks in adult human immunodeficiency virus (HIV) type 1-infected patients assigned indinavir/ritonavir (Idv/Rtv; 800/100 mg 2 times daily) or saquinavir/ritonavir (Sqv/Rtv; 1000/100 mg 2 times daily) in an open-label, randomized (1:1), multicenter, phase 4 design. Three hundred six patients began the assigned treatment. At 48 weeks, virological failure was seen in 43 (27%) of 158 and 37 (25%) of 148 patients in the Idv/Rtv and Sqv/Rtv arms, respectively. The time to virological failure did not differ between study arms (P=.76). When switching from randomized treatment was counted as failure, this was seen in 78 of 158 patients in the Idv/Rtv arm, versus 51 of 148 patients in the Sqv/Rtv arm (P=.009). A switch from the randomized treatment occurred in 64 (41%) of 158 patients in the Idv/Rtv arm, versus 40 (27%) of 148 patients in the Sqv/Rtv arm (P=.013). Sixty-four percent of the switches occurred because of adverse events. A greater number of treatment-limiting adverse events were observed in the Idv/Rtv arm, relative to the Sqv/Rtv arm. In conclusion, Rtv-boosed Sqv and Idv were found to have comparable antiretroviral effects in the doses studied.
Related Concept Videos
 01:11
Bioavailability Study Design: Single Versus Multiple Dose Studies
 01:15
Bioavailability Study Design: Healthy Subjects Versus Patients
 01:15
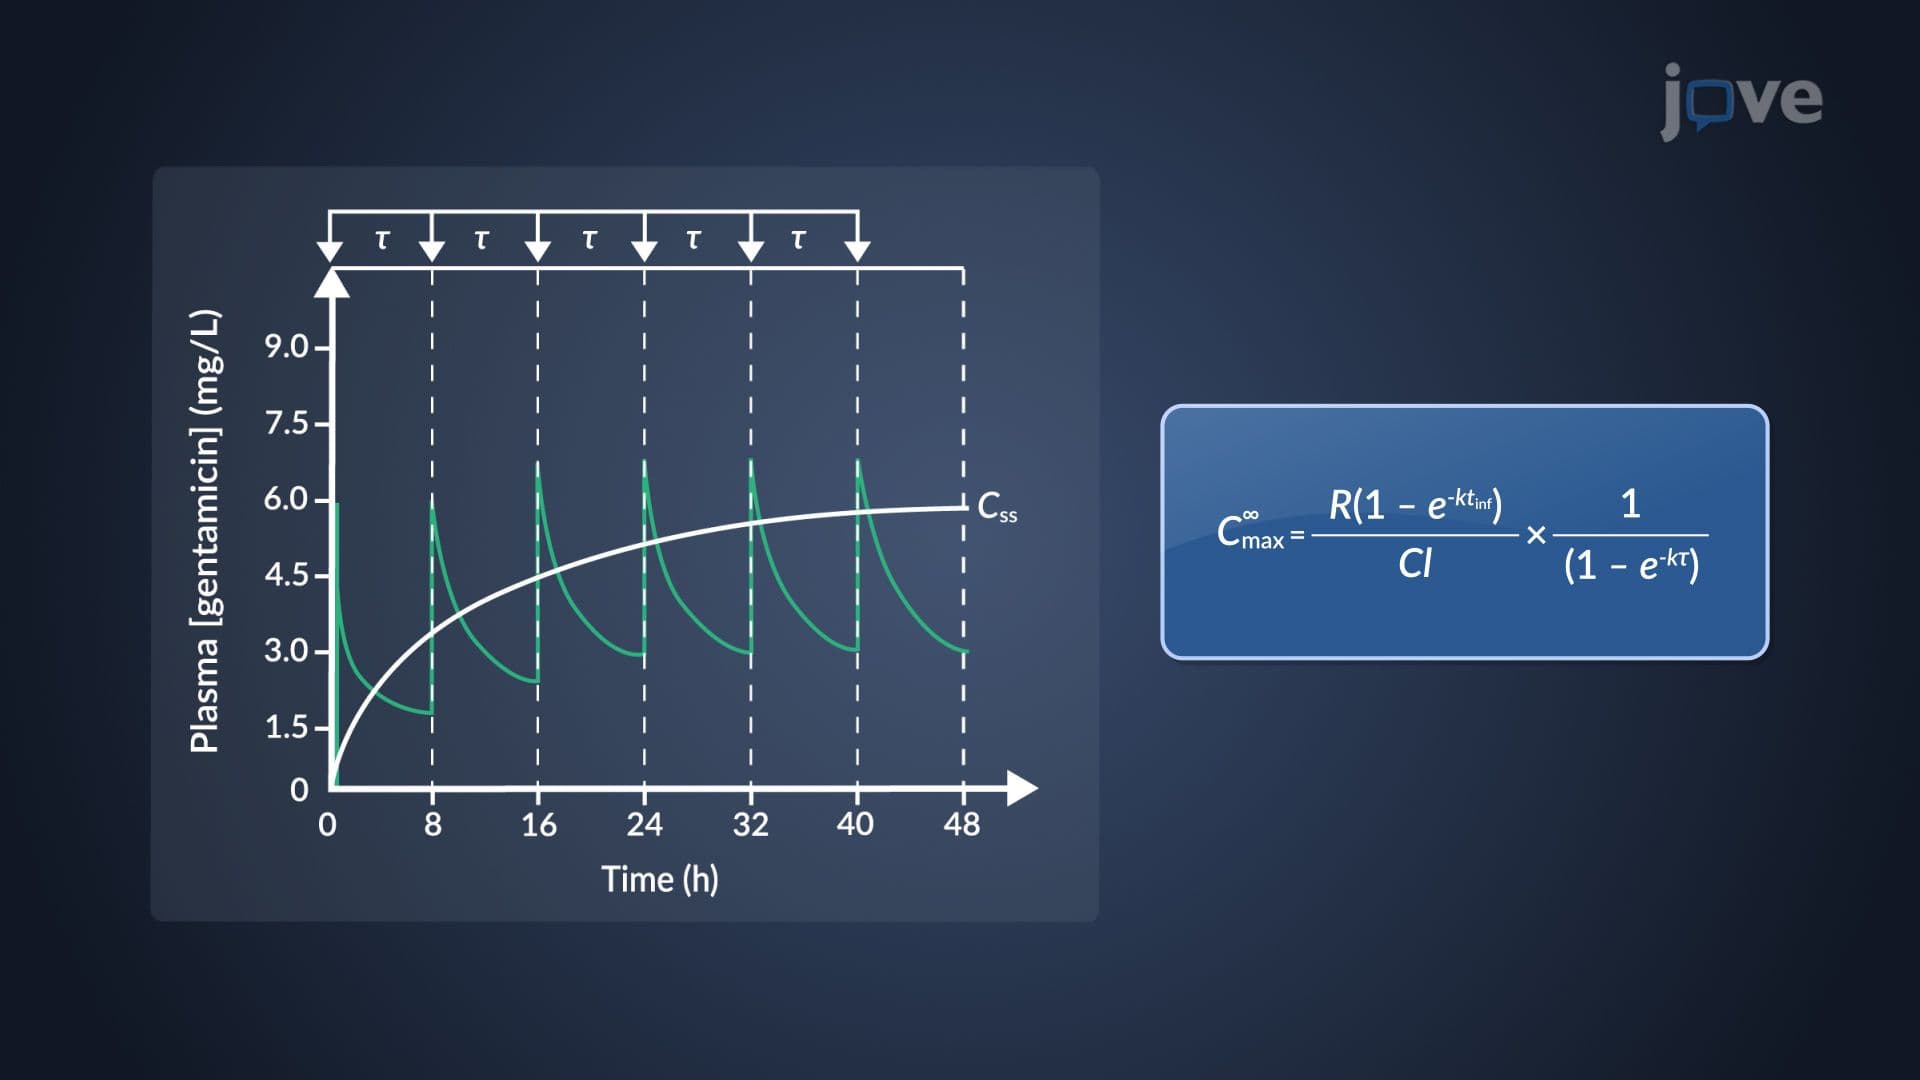
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:22
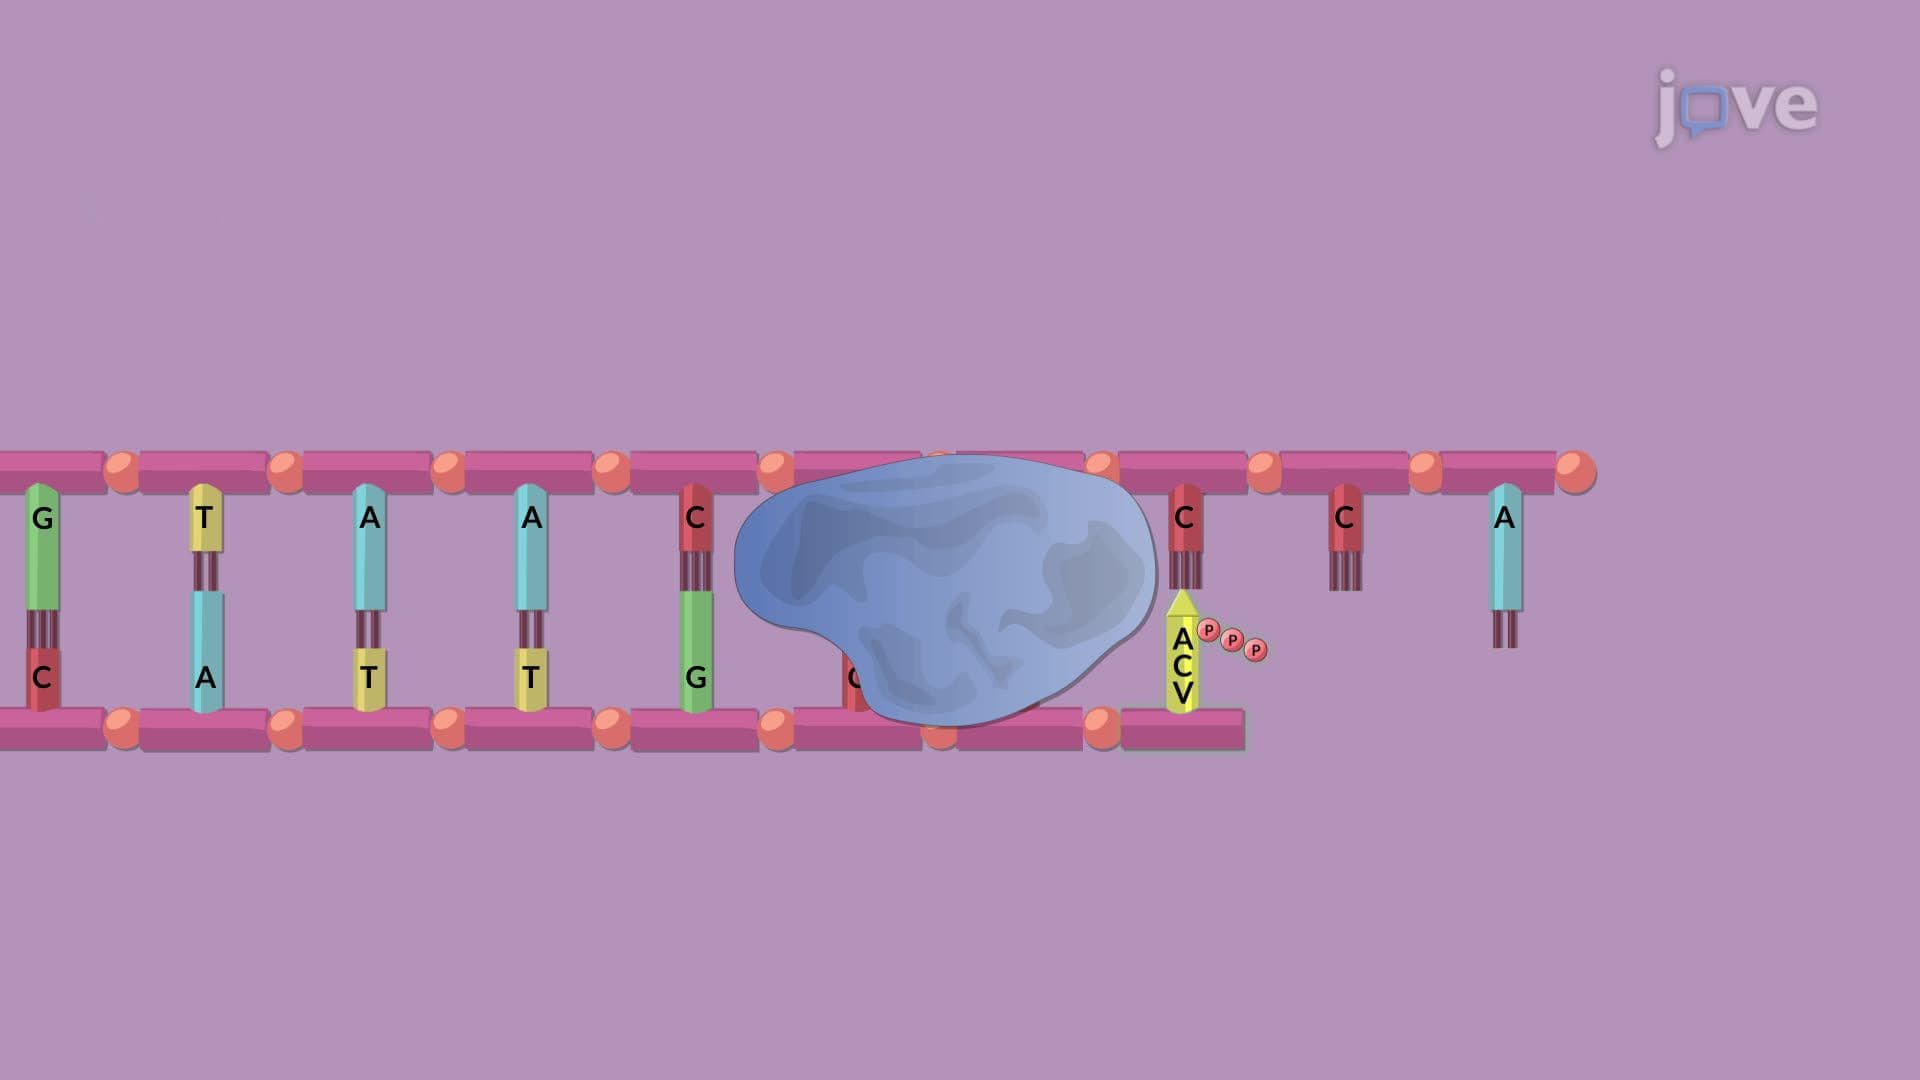
Antiviral Nucleoside Inhibitors