Related Experiment Video
Updated: Sep 20, 2026


Surfactant Depletion Combined with Injurious Ventilation Results in a Reproducible Model of the Acute Respiratory Distress Syndrome (ARDS)
Published on: April 7, 2021
Pressure/volume curves and lung computed tomography in acute respiratory distress syndrome
1Réanimation Chirurgicale Pierre Viars, Dept of Anesthesiology, Hospital Pitié-Salpétrière, University Paris VI, Paris, France. jjrouby.pitie@invivo.edu

Abstract:
Pressure/volume (P/V) curves can be measured by static methods, constant or sinusoidal flow methods and the dynostatic method that allows a breath-to-breath determination of P/V curves. Recent ventilators are equipped with specific flow generators and software aimed at obtaining P/V curves without disconnecting the patient from the ventilator. The most recent generation of computed tomography scanners allows the quantitative determination of lung aeration, lung volumes (gas and tissue), alveolar recruitment and lung overinflation of the whole lung. In the supine position, the acute respiratory distress syndrome (ARDS) lung is characterised by an increase in lung tissue that predominates in upper lobes and a massive loss of aeration that predominates in lower lobes. In a minority of ARDS patients, the loss of aeration is homogeneously distributed. The overall lung volume of upper lobes is preserved suggesting an alveolar flooding-induced loss of aeration. In contrast, the overall lung volume of lower lobes is reduced because the heart and the abdomen exert an external compression that contributes to the loss of aeration. The P/V curve is a lung recruitment curve and the chord compliance indicates the potential for recruitment. In such patients, alveolar recruitment resulting from positive end-expiratory pressure is not accompanied by lung overinflation. In a majority of acute respiratory distress syndrome patients, upper lobes remain partially or totally aerated despite a marked regional increase in lung tissue. The upper lobes' overall lung volume is either normal or increased, suggesting that the lung does not collapse under its own weight as generally believed. In lower lobes, the overall lung volume is reduced because the heart and the abdomen exert an external compression that contributes to the loss of aeration. The pressure/volume curve is influenced by the recruitment of poorly and nonaerated lung regions and by the mechanical properties of the part of the lung remaining aerated. In such patients, alveolar recruitment resulting from positive end-expiratory pressure >10 cmH2O is preceded and accompanied by lung overinflation.

Related Concept Videos
 01:15
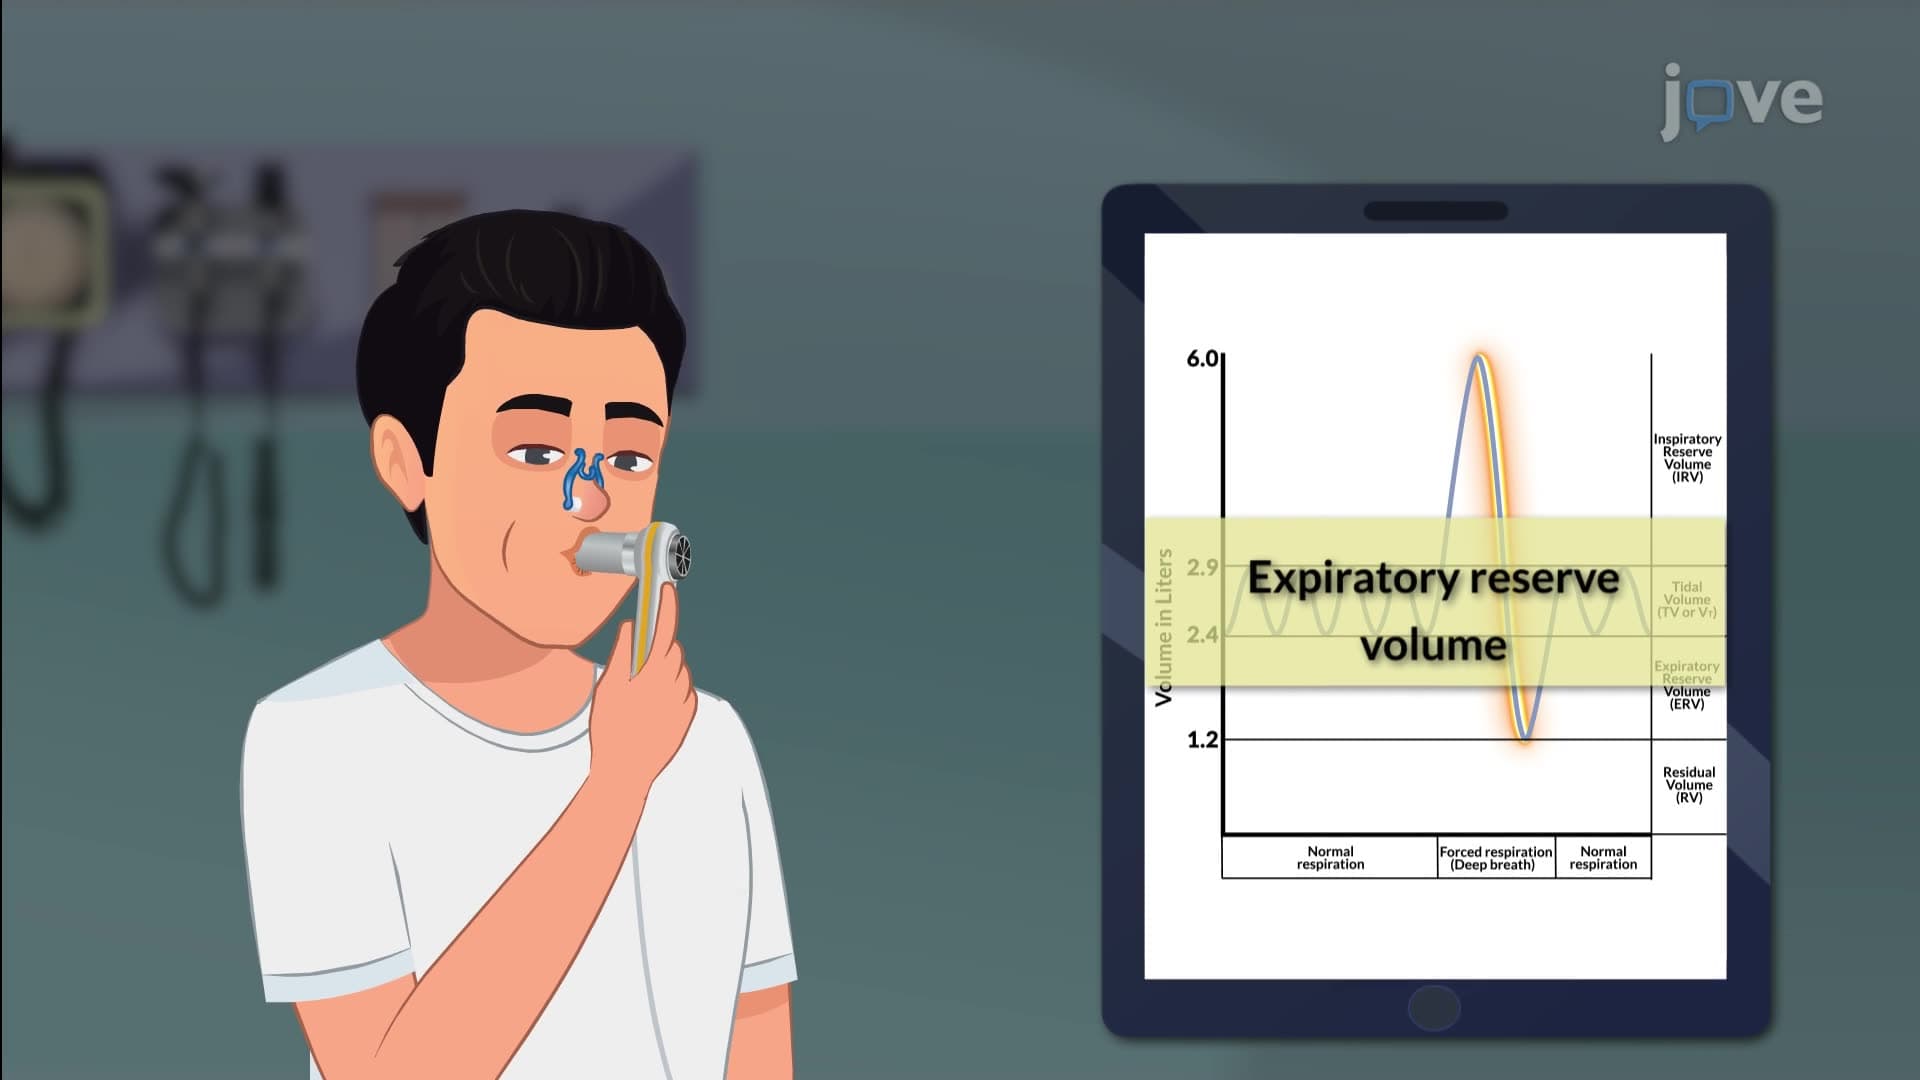
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:30
Acute Respiratory Failure-III
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...
 01:24
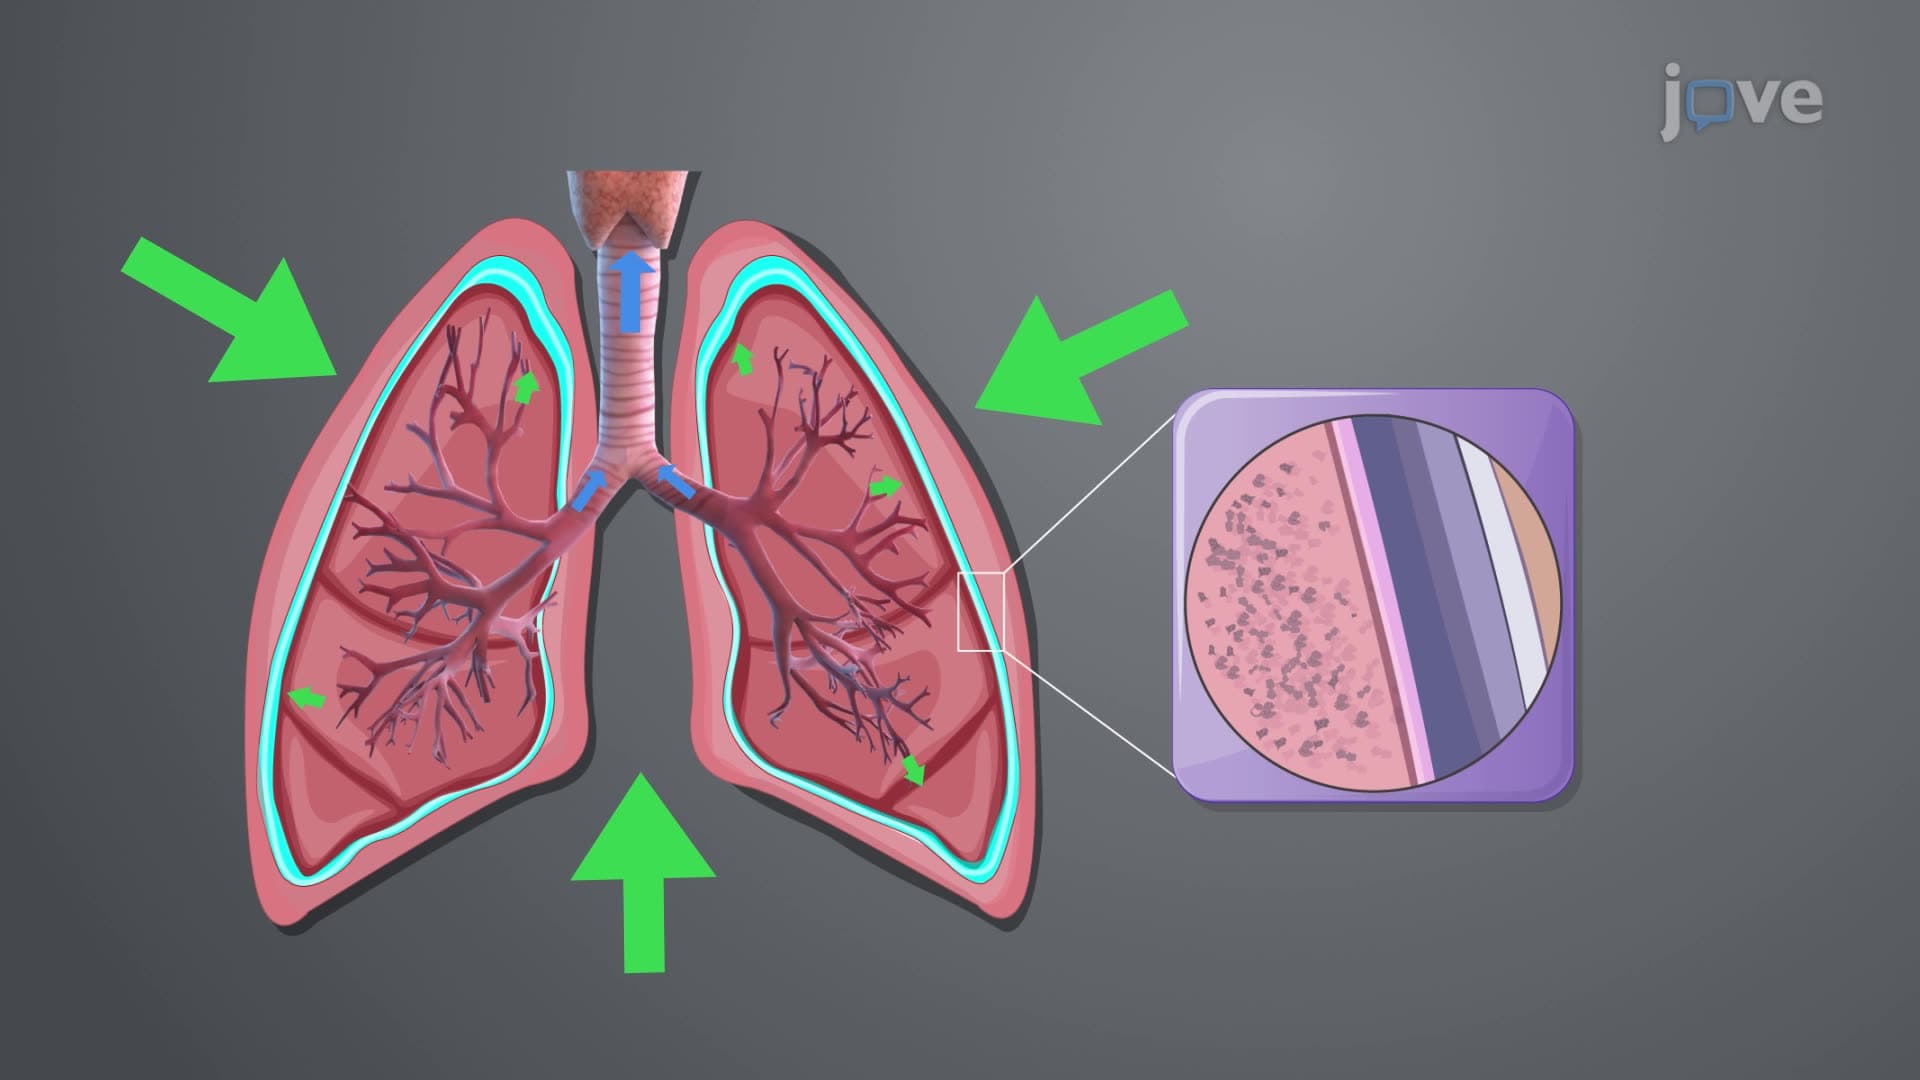
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs during...