Related Experiment Video
Updated: Jul 25, 2026

Fetal Mouse Cardiovascular Imaging Using a High-frequency Ultrasound (30/45MHZ) System
Published on: May 5, 2018
Energy expenditure in infants with congenital heart disease, including a meta-analysis
M van der Kuip1, M B Hoos, P P Forget
1Department of Paediatrics, VU University Medical Centre, Amsterdam, The Netherlands.

Insights
Infants with congenital heart disease (CHD) need significantly more energy due to higher total daily energy expenditure (TDEE), not increased body water. Other factors like vomiting contribute to growth issues in CHD infants with heart failure.
Area of Science:
- Pediatric Cardiology
- Nutritional Science
- Biomedical Engineering
Background:
- Congenital heart disease (CHD) can significantly impact a child's nutritional status and energy needs.
- Accurate assessment of energy requirements is crucial for optimizing growth and development in these vulnerable patients.
Purpose of the Study:
- To evaluate the energy requirements and body composition of infants with congenital heart disease (CHD) before surgery.
- To compare energy expenditure and body water content in infants with CHD to healthy controls.
Main Methods:
- Utilized doubly labeled water technique to measure total daily energy expenditure (TDEE) and total body water (TBW) in 11 infants with CHD.
- Compared patient data with historical controls and conducted meta-analyses with existing literature.
- Analyzed the influence of congestive heart failure on energy expenditure within the CHD group.
Main Results:
- Infants with CHD exhibited significantly increased TBW (66% vs. 58%) and energy expenditure (381 vs. 298 kJ/kg/day) compared to controls.
- Meta-analyses confirmed a 35% increase in TDEE and a 7% increase in TBW in infants with CHD.
- Congestive heart failure did not significantly alter TDEE, but in cases of growth failure, factors like vomiting contributed to a disturbed energy balance.
Conclusions:
- Infants with CHD require substantially higher energy intake (at least 100 kJ/kg/day extra) due to elevated TDEE, independent of body water percentage.
- The presence of coexistent heart failure does not appear to independently increase TDEE.
- In infants with CHD and growth failure, factors beyond elevated TDEE, such as vomiting, play a role in the negative energy balance.
Aim:
To assess energy requirements and body composition in preoperative children with congenital heart disease (CHD).
Methods:
In 11 infants with CHD (2-8 mo), total daily energy expenditure (TDEE) and total body water (TBW) were measured with doubly labelled water and compared with historic data from healthy controls. Within the patient group, energy expenditure of infants with versus those without congestive heart failure was compared. Subsequently, the data were pooled with literature data in meta-analyses.
Results:
CHD patients showed increased TBW (mean +/- SD 66 +/- 3 vs 58 +/- 5% of body weight, p < 0.05) and energy expenditure (381 +/- 42 vs 298 +/- 36 kJ kg(-1) d(-1), p < 0.001). Meta-analyses showed that CHD infants have 35% increased TDEE (376 vs 278 kJ kg(-1) d(-1) , p < 0.00001) and 7% higher TBW (p < 0.0001). Coexistent congestive heart failure (treated with diuretics) had no influence on TDEE (mean difference 14 kJ kg(-1) d(-1) , not significant). In patients with heart failure and growth retardation, an energy balance study showed an average 12% loss of initially ingested energy due to vomiting, increased TDEE and low faecal energy loss, resulting in low energy available for growth, compared with controls (42 +/- 30 vs 96 +/- 61 kJ kg(-1) d(-1) , p < 0.05).
Conclusion:
Many infants with CHD require substantially higher energy intake (at least 100 kJ kg(-1) d(-1) extra) owing to increased TDEE, which is not explained by a higher percentage of body water. Coexistent heart failure does not appear to have an additional influence on TDEE. In infants with CHD and growth failure factors other than elevated TDEE, including vomiting, may explain the disturbed energy balance.


Related Concept Videos
 01:30
Factors Influencing Heart Rate
Let us explore the significant factors affecting heart rate, including age, body temperature, posture, acute pain, chemical influences,...
 01:29
Pathophysiology of Cardiac Performance
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be met...
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
 01:19
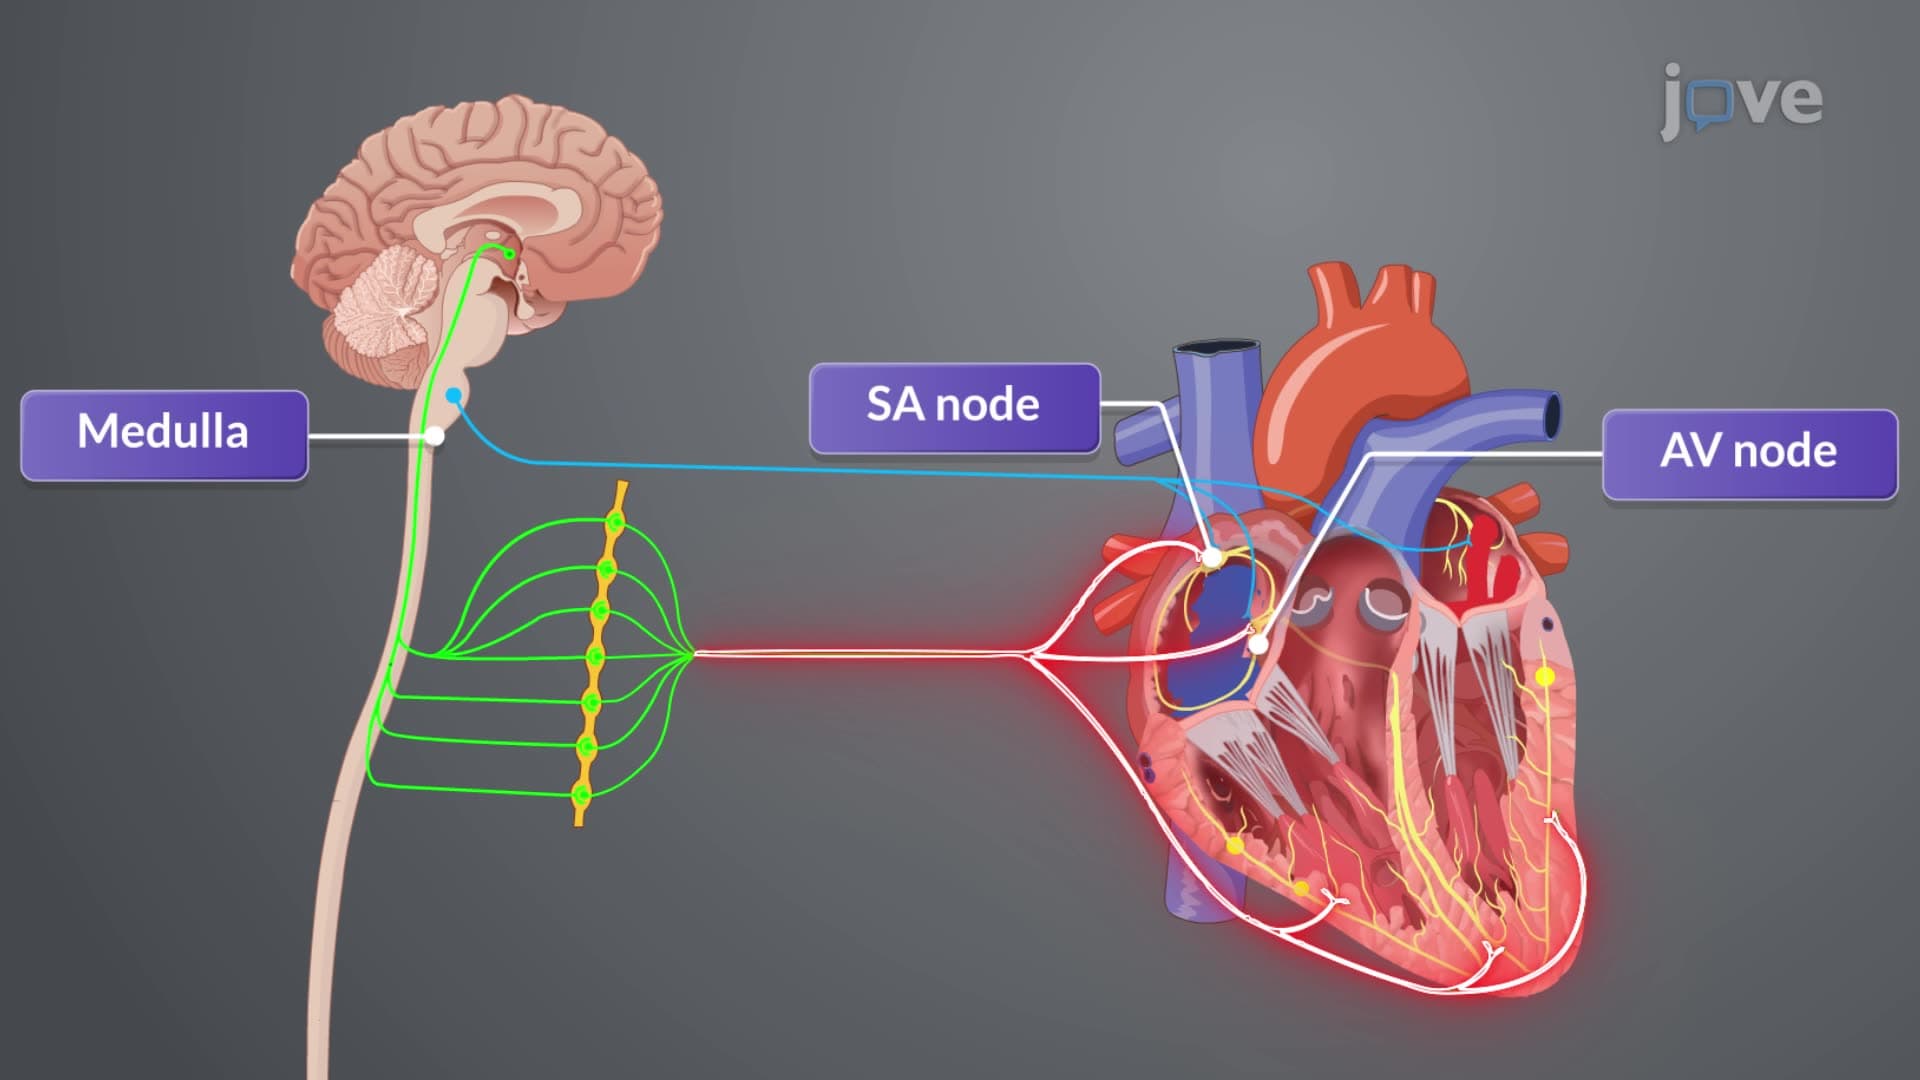
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart rate...