Related Experiment Video
Updated: Jul 14, 2026
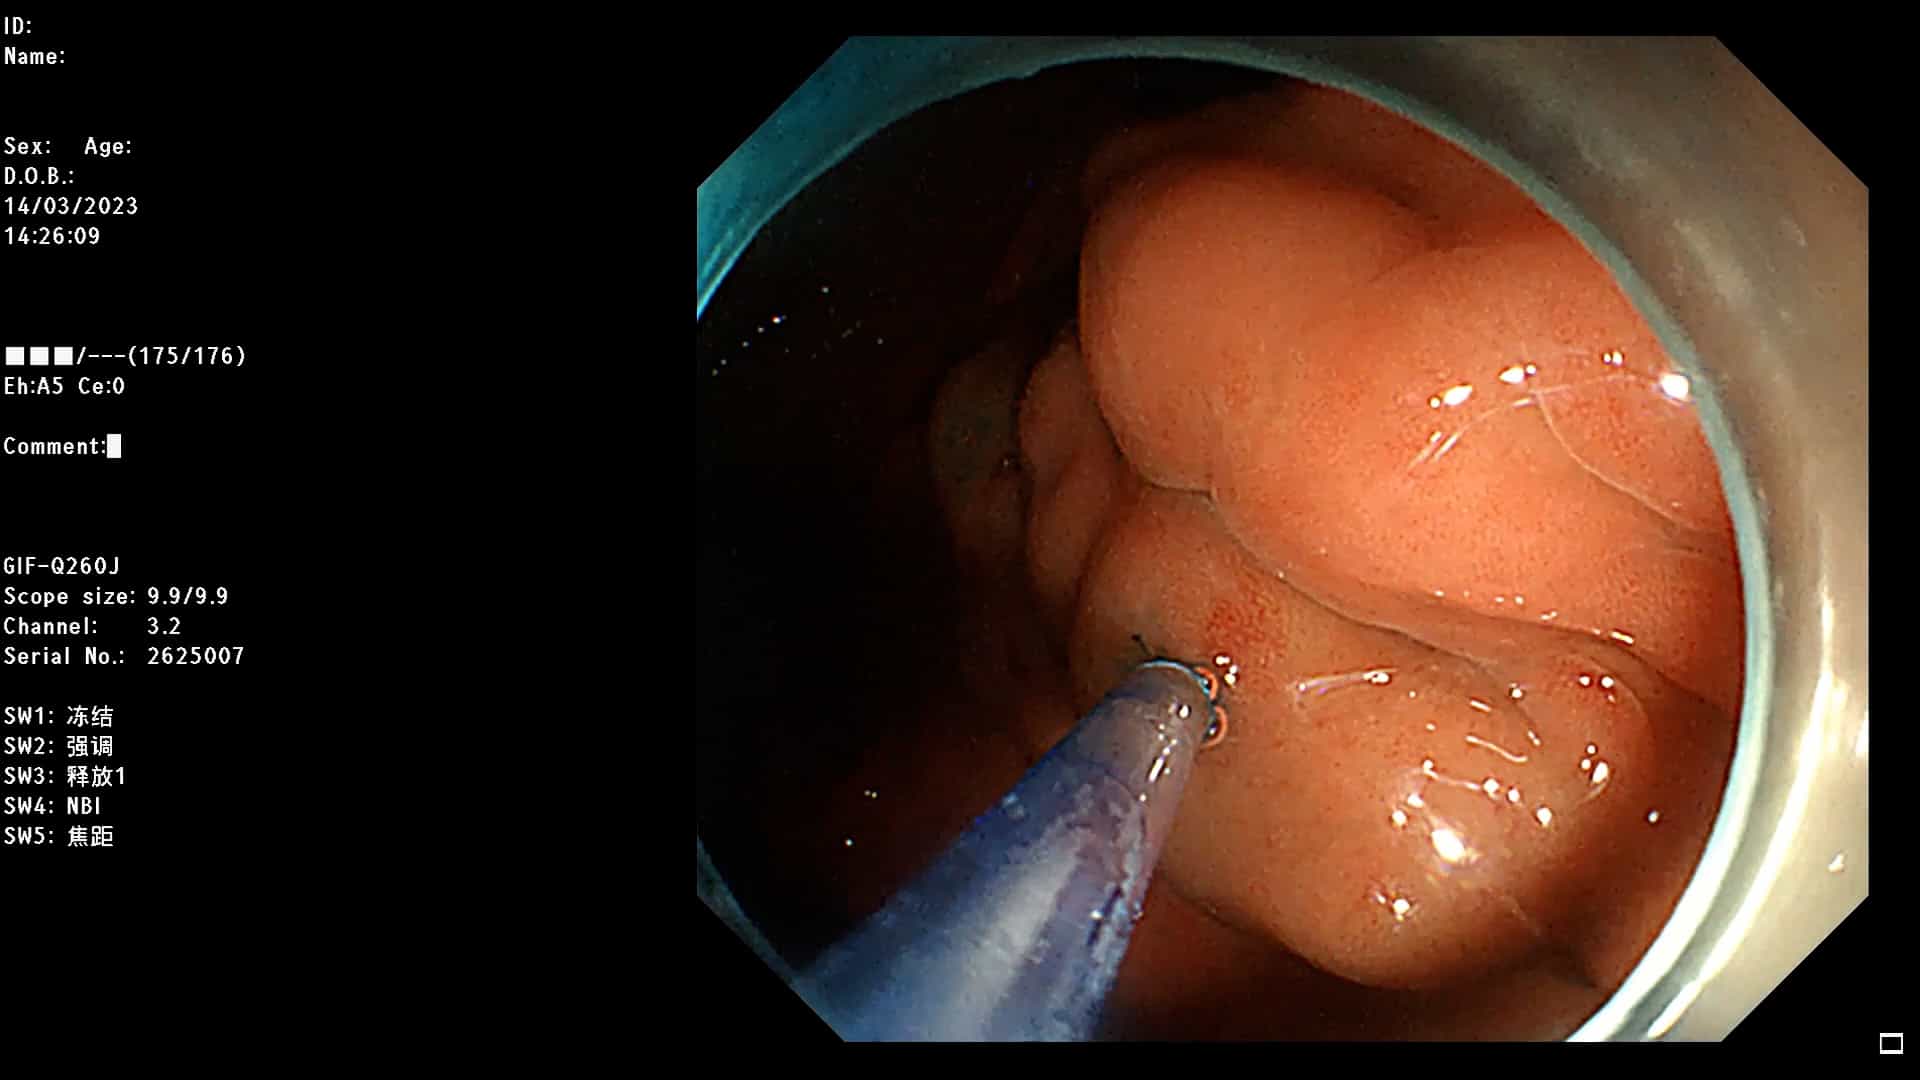
Endoscopic Injection Sclerotherapy Assisted by Cyanoacrylate and Clips for Gastroesophageal Varices
Published on: June 13, 2025
The effect of endoscopic therapy in patients receiving omeprazole for bleeding ulcers with nonbleeding visible
Joseph J Y Sung1, Francis K L Chan, James Y W Lau
1Endoscopy Center, Prince of Wales Hospital, Chinese University of Hong Kong, Shatin, Hong Kong. joesung@cuhk.edu.hk

Background:
The optimal treatment of ulcers with nonbleeding visible vessels and adherent clots is unclear.
Objective:
To compare intravenous omeprazole infusion plus endoscopic therapy with intravenous omeprazole infusion alone for prevention of recurrent bleeding from ulcers with nonbleeding visible vessels or adherent clots.
Design:
Single-blind randomized study with blinded evaluation of study end points.
Setting:
An endoscopy center in a university hospital in Hong Kong.
Patients:
156 persons with upper gastrointestinal bleeding and ulcers showing nonbleeding visible vessels or adherent clots.
Intervention:
Combination of endoscopic therapy and omeprazole infusion versus sham endoscopic therapy and omeprazole infusion.
Measurements:
Recurrent ulcer bleeding before discharge and within 30 days.
Results:
78 patients were recruited in each group. Ulcer bleeding recurred before discharge in seven patients who received intravenous omeprazole alone (9%) and no patients who received combined therapy (difference, 9 percentage points [95% CI, 1.7 to 17.6 percentage points]; P = 0.01). The probability of recurrent bleeding within 30 days was 11.6% (9 patients) in the omeprazole-alone group and 1.1% (1 patient) in the combined therapy group (difference, 10.5 percentage points [CI, 1.7 to 19.8 percentage points]; P = 0.009). Patients in the combined therapy group required less transfusion (difference in median units of blood transfused, 1 unit [CI, 0 to 2 units]; P = 0.02). One patient in the combined therapy group had surgery for ulcer perforation. Four patients receiving omeprazole alone (5.1%) and two patients receiving combined therapy (2.6%) died within 30 days.
Conclusion:
The combination of endoscopic therapy and omeprazole infusion is superior to omeprazole infusion alone for preventing recurrent bleeding from ulcers with nonbleeding visible vessels and adherent clots.

Related Concept Videos
 01:13
Acid Suppressive Drugs for Peptic Ulcer Disease: Proton Pump Inhibitors
Gastric acid, a potent cocktail of hydrogen and chloride ions, is produced in specialized parietal cells within the...
 01:24
Drugs for Peptic Ulcer Disease: Sucralfate as Mucosal Protective Agents
In this scenario, mucosal protective agents like sucralfate play an essential role. Sucralfate, a complex of sulfated sucrose and aluminum hydroxide, demonstrates its usefulness in acidic conditions,...
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...
 01:16
Treating Helicobacter pylori in Peptic Ulcers: Antimicrobial Therapy
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...