Related Experiment Video
Updated: Mar 10, 2026
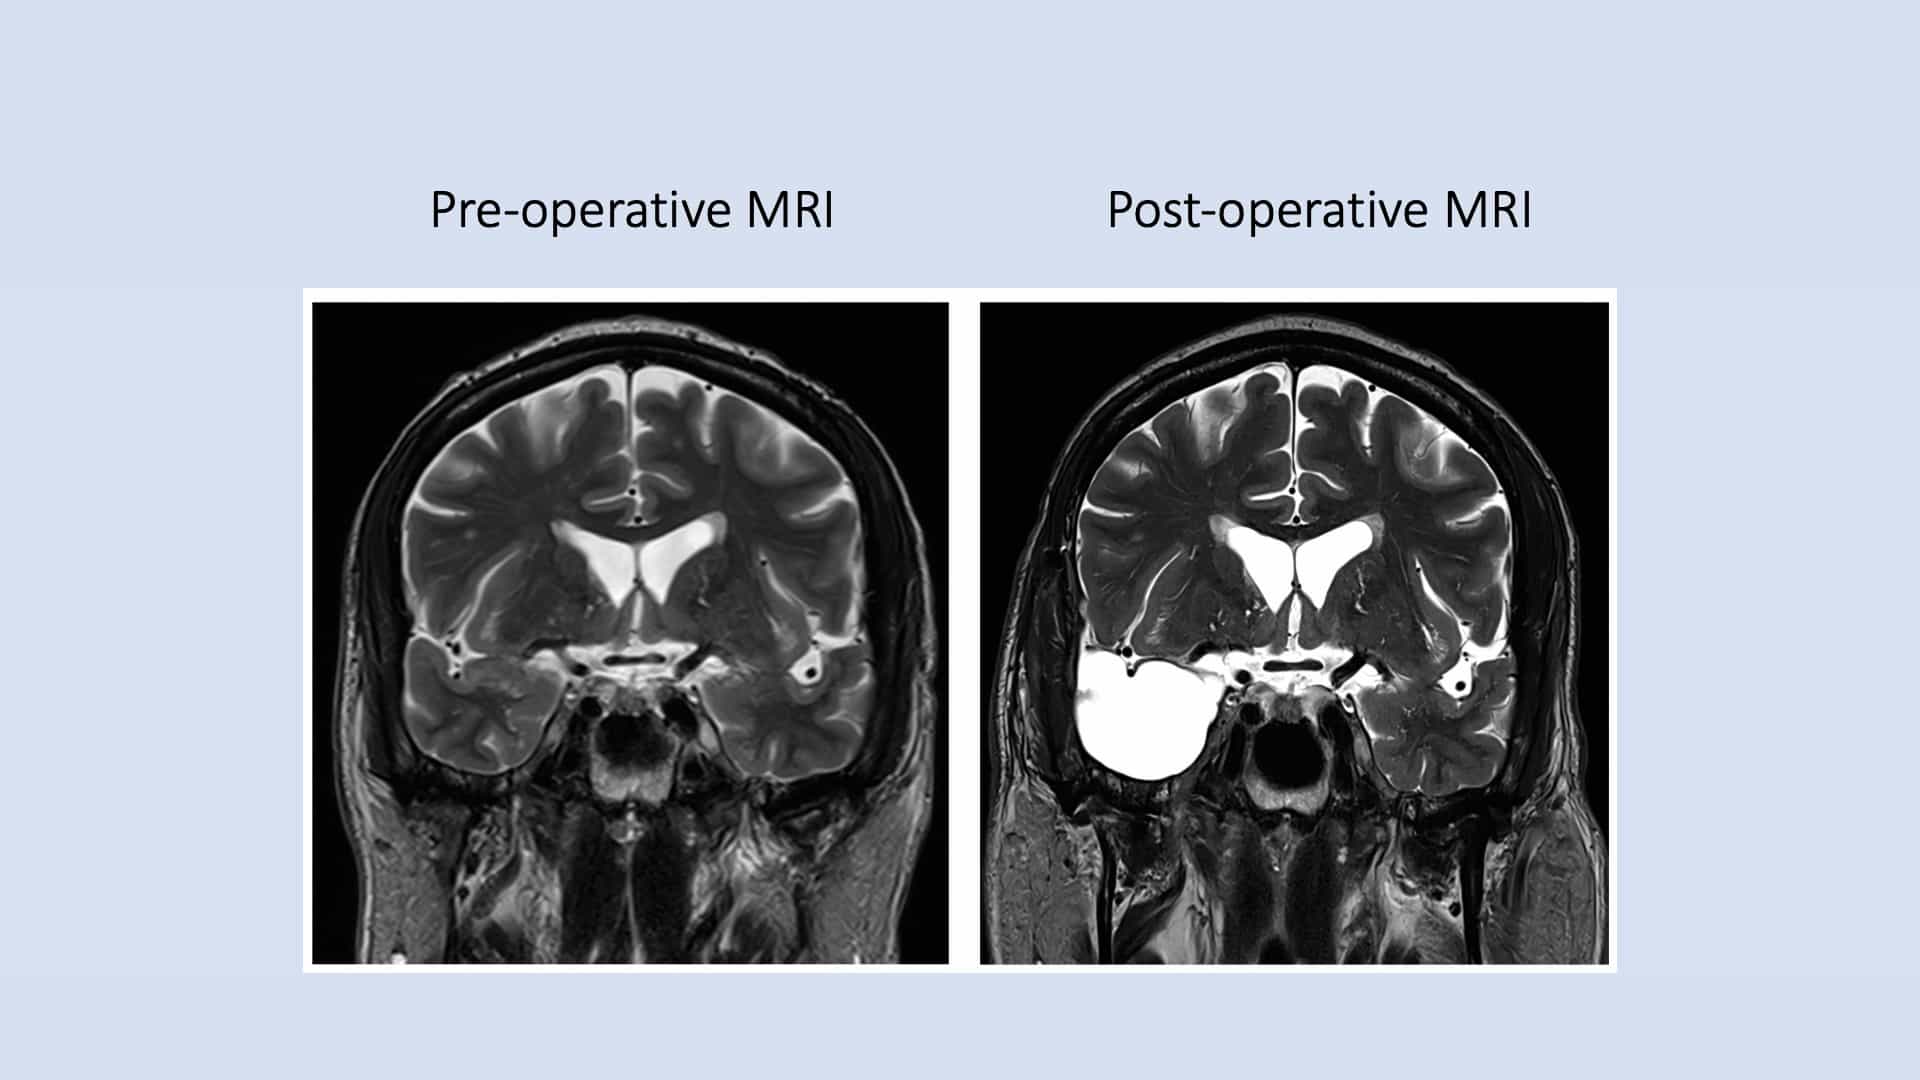

Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
Antiepileptic drug treatment before and after selective amygdalohippocampectomy
Heinz-Gregor Wieser1, Adrian Häne
1Department of Neurology, University Hospital Zurich, University of Zürich, Frauenklinikstrasse 26, CH-8091 Zürich, Switzerland. hgwepi@neurol.unizh.ch

Abstract:
Retrospectively, we analyzed pre and postoperative (po) AED treatment in relation to long-term annual seizure outcome in the Zurich selective amygdalohippocampectomy (AHE) series. In 376 patients (hippocampal sclerosis ("HS"), n:185; other lesions ("lesional"), n:191) with a follow-up of more than 1 year, in the last available outcome (lao), 60% were seizure- and aura-free (ILAE Class 1). During the year prior to surgery, in the "HS" group a mean of 2.3 +/- 0.8 AEDs were taken. The percentage of patients without AEDs increases to 36.1% in the po years 1-5 (po year 5: "HS" (n:133) 27.8%; "lesional" (n:111) 45.9%). In po years 7-11 this percentage is between 40 and 43% (po year 10: "HS" (n:75) 29.3%; "lesional" (n:65) 55.4%). In the ILAE Class 1a, at po year 5 63/85 (74.1%) patients have discontinued AED intake. At lao 36.2% of patients were off AEDs and additional 18.9% had a "substantial" reduction (i.e. from polytherapy to monotherapy, or a reduction of the existing monotherapy by at least 66% compared to the year before AHE). The relapse rate is similar for patients who were free of disabling seizures (a) for > or =1 year and without AEDs (17.1%), (b) immediately after surgery with or without AEDs (18.4%), and (c) had a "substantial" AED reduction over the entire follow-up period (18.9%). The rate of re-gained full seizure control, however, is significantly better for group (b) compared to (c) (77% versus 53%). 10.9% of patients showed the "running down phenomenon," i.e. had seizures during the first po year, but then became seizure-free for 1 or more years. The percentage of patients free of "disabling" seizures, who did not follow the medical advice to discontinue/reduce AEDs, is about 30% after the 10th po year. In the 15th po year this figure is 4.2 times higher for "HS" versus "lesional" patients. We conclude that the time of discontinuation of AEDs after AHE should be tailored based on the results of the presurgical evaluation, the early po seizure outcome, the histopathological findings, the intraoperative ECoG findings and the po EEG. In an optimal constellation, "substantial" AED reduction with the goal of a monotherapy can be advised 1 year and discontinuation 2 years after surgery.
More Related Videos


Related Concept Videos
 01:14
Antiepileptic Drugs: Glutamate Antagonists
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...
 01:20
Antiepileptic Drugs: Potassium Channel Activators
Ezogabine has gained approval as an adjunctive treatment...
 01:30
Electroconvulsive Therapy