Giant emphysematous bullae of the lung
Related Experiment Video
Updated: Oct 8, 2026

06:15
Protocol and Guidelines for Point-of-Care Lung Ultrasound in Diagnosing Neonatal Pulmonary Diseases Based on International Expert Consensus
Published on: March 6, 2019
D Ray1, D J Christopher, P S Jairaj
1Department of Chest Diseases, Christian Medical College, Vellore.
The Indian Journal of Chest Diseases & Allied Sciences
|October 1, 1992

Abstract:
Emphysematous bullae may at times assume large proportions. We report a case of symptomatic giant bullae in a female which were removed surgically. The relevant literature has also been reviewed.
Related Concept Videos
 01:17
Gross Anatomy of the Lungs
The lungs are a pair of vital organs connected to the trachea via the left and right bronchi. The base of these organs meets the dome-shaped muscle known as the diaphragm. Encased by the pleurae, the lungs contact the mediastinum. The right lung is shorter yet wider, and has a larger volume than the left lung. The left lung has an indentation known as the cardiac notch. The superior region of the lungs is referred to as the apex, whereas the base is the lower region near the diaphragm. The...
 01:13
Pleura of the Lungs
The lungs are nestled in a cavity, shielded by the pleura. The pleura, a form of serous membrane, wraps around each lung. This membrane arrangement consists of two layers: the visceral and parietal pleurae. The visceral pleura lines the surface of the lungIn contrast, the parietal pleura is the outer layer and contacts to the thoracic wall, the mediastinum, and the diaphragm. The hilum is the point of connection between the visceral and parietal layers. The space between the parietal and...
 01:28
Pulmonary Tuberculosis II
Tuberculosis, or TB, is a bacterial infectious disease caused by Mycobacterium tuberculosis. While its primary impact is on the lungs, leading to pulmonary tuberculosis, it can also affect various other organs, a condition referred to as extrapulmonary tuberculosis.
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Obstructive Pulmonary Disease (COPD) pathophysiology is intricate and multifaceted, involving a complex interplay of physiological processes. Understanding these mechanisms is crucial for effectively managing and treating COPD. Here is an in-depth look at the critical elements in the pathophysiology of COPD:
Chronic Inflammation
Chronic Inflammation
 01:23
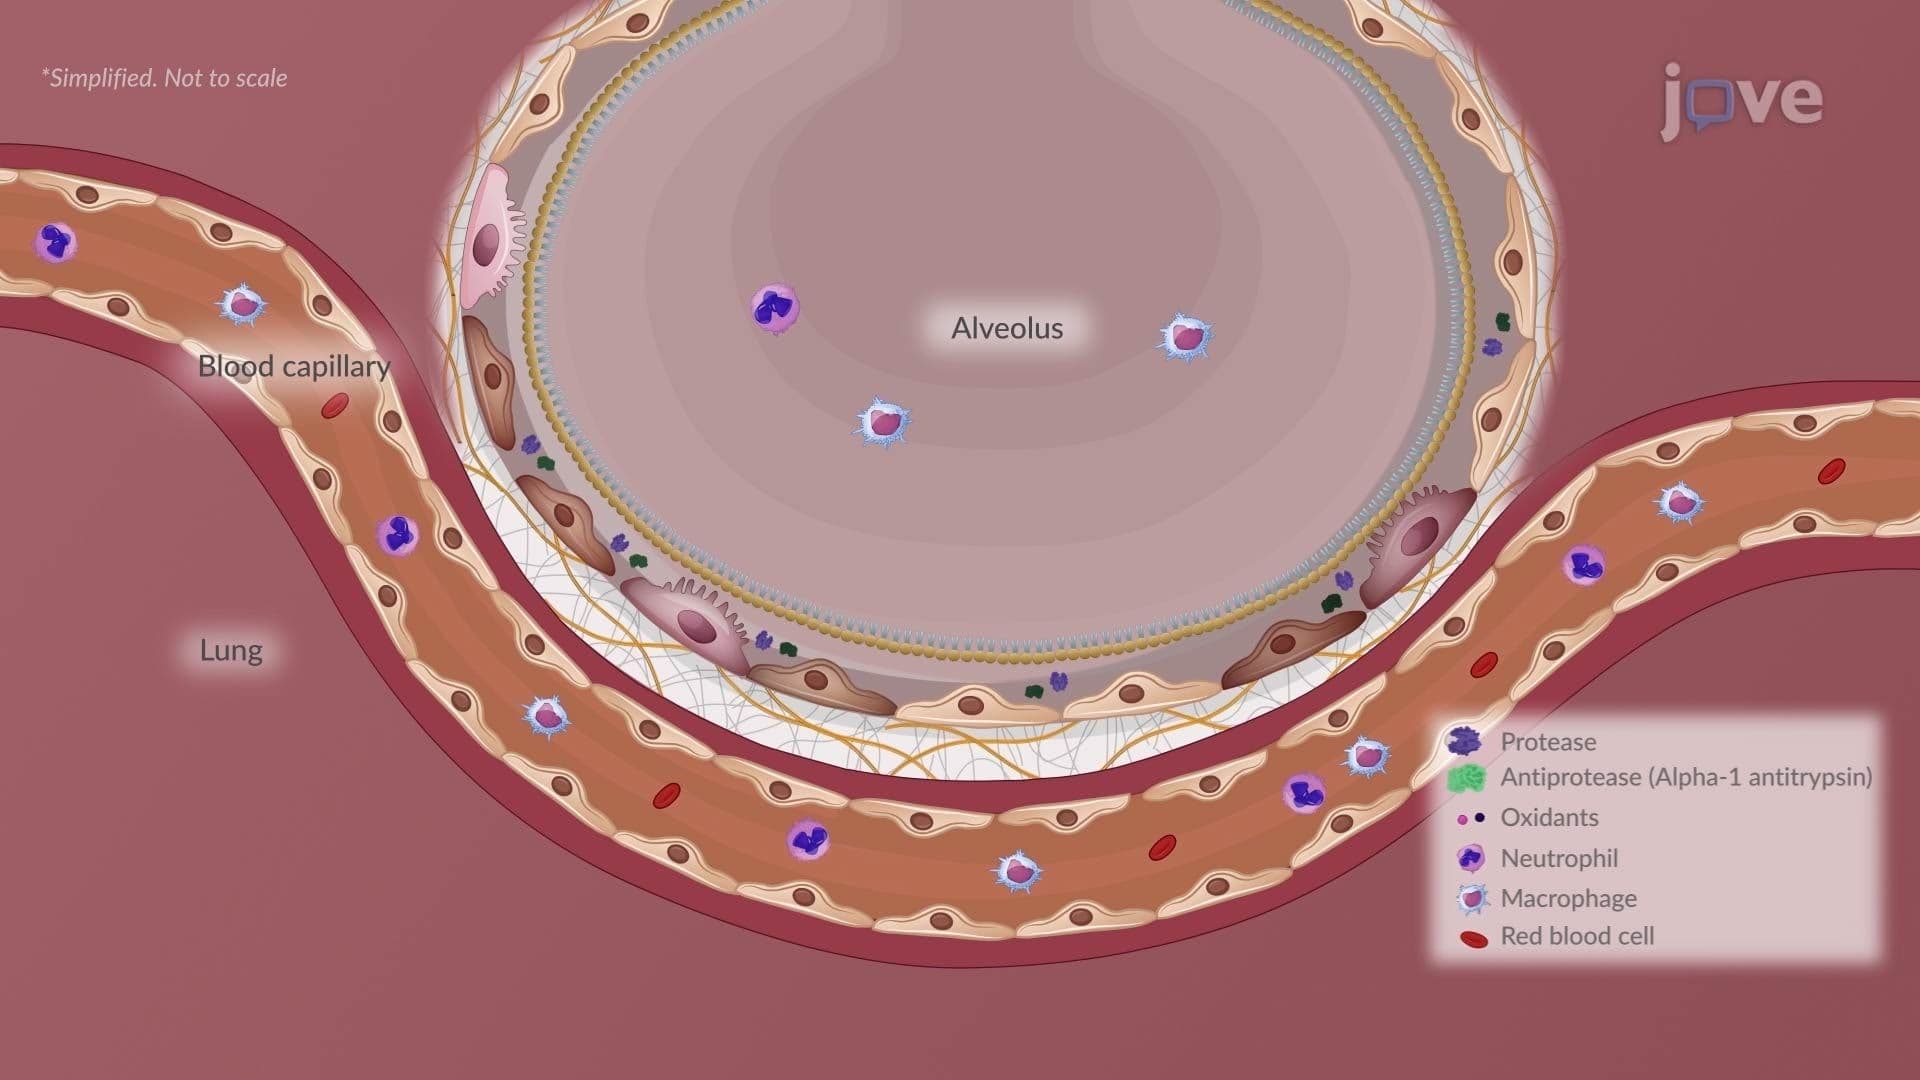
Chronic Obstructive Pulmonary Disease II: Emphysema
Emphysema, a major phenotype of chronic obstructive pulmonary disease (COPD), is characterized by irreversible destruction of alveolar walls and permanent enlargement of distal airspaces. Unlike chronic bronchitis, which primarily affects the airways, emphysema predominantly involves the lung parenchyma, where structural damage leads to airflow limitation.PathophysiologyIt most commonly results from prolonged exposure to cigarette smoke and other toxic gases, particularly cigarette smoke.
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
Chronic bronchitis is a key phenotype of chronic obstructive pulmonary disease (COPD), characterized by airway-centered inflammation and mucus overproduction. It develops from long-term exposure to harmful particles or gases, most commonly cigarette smoke, which triggers a persistent inflammatory response.Cellular and Structural ChangesInflammation initially affects the large bronchi and later the smaller airways, with infiltration by immune cells, including neutrophils, macrophages, and...