Related Experiment Video
Updated: Aug 14, 2026


Continuous Manual Exchange Transfusion for Patients with Sickle Cell Disease: An Efficient Method to Avoid Iron Overload
Published on: March 14, 2017
Prothrombotic effect of erythropoietin in dialysis patients
J E Taylor1, M McLaren, I S Henderson
1Renal Unit, Ninewells Hospital and Medical School, Dundee, Scotland, UK.

Thrombin-antithrombin III complex concentrations (TAT-III) were measured in 18 anaemic haemodialysis patients treated with erythropoietin (Epo) and in four haemodialysis patients treated with i.v. iron dextran. There was a significant early increase in thrombin-antithrombin III in erythropoietin-treated patients which appeared to be independent of the response to erythropoietin (Epo responders (n = 14), pretreatment TAT-III median (range) 3.10 (2.70-9.10) micrograms/l; maximum TAT-III 19.48 (11.18-60.00) micrograms/l, P less than 0.001, Wilcoxon; Epo non-responders (n = 4), pretreatment TAT-III 3.15 (2.90-4.50) micrograms/l, maximum TAT-III 16.00 (10.31-36.12) micrograms/l, P less than 0.001). This was not seen in iron-dextran-treated patients (Pretreatment TAT-III 2.05 (1.90-9.48) micrograms/l, maximum TAT-III 5.60 (2.10-14.50) micrograms/l). The change was not related to haemoglobin, erythropoietin dose, or method of administration, and was transient in nature, thrombin-antithrombin III returning to pretreatment values after approximately 6 months in all patients (Epo responders 6.0(4.0-9.0) months, TAT-III 2.47 (1.30-9.23) micrograms/l; Epo non-responders 7.0 months, TAT-III 5.04 (2.10-7.00) micrograms/l). Increased thrombin-antithrombin III complex may reflect an effect of erythropoietin on microcirculatory factors, which could be relevant to the occurrence of adverse events during treatment.
Thrombin-antithrombin III complex concentrations (TAT-III) were measured in 18 anaemic haemodialysis patients treated with erythropoietin (Epo) and in four haemodialysis patients treated with i.v. iron dextran. There was a significant early increase in thrombin-antithrombin III in erythropoietin-treated patients which appeared to be independent of the response to erythropoietin (Epo responders (n = 14), pretreatment TAT-III median (range) 3.10 (2.70-9.10) micrograms/l; maximum TAT-III 19.48 (11.18-60.00) micrograms/l, P less than 0.001, Wilcoxon; Epo non-responders (n = 4), pretreatment TAT-III 3.15 (2.90-4.50) micrograms/l, maximum TAT-III 16.00 (10.31-36.12) micrograms/l, P less than 0.001). This was not seen in iron-dextran-treated patients (Pretreatment TAT-III 2.05 (1.90-9.48) micrograms/l, maximum TAT-III 5.60 (2.10-14.50) micrograms/l). The change was not related to haemoglobin, erythropoietin dose, or method of administration, and was transient in nature, thrombin-antithrombin III returning to pretreatment values after approximately 6 months in all patients (Epo responders 6.0(4.0-9.0) months, TAT-III 2.47 (1.30-9.23) micrograms/l; Epo non-responders 7.0 months, TAT-III 5.04 (2.10-7.00) micrograms/l). Increased thrombin-antithrombin III complex may reflect an effect of erythropoietin on microcirculatory factors, which could be relevant to the occurrence of adverse events during treatment.

Related Concept Videos
 01:14
Erythropoiesis
01:14Erythropoiesis
 01:27
Disorders of Erythrocytes
Erythrocyte disorders can be broadly categorized into two main types: anemic and polycythemic conditions.
A low oxygen-carrying capacity of the blood due to the loss, lower production, or destruction of erythrocytes is termed anemia. Hemorrhagic anemia, for example, occurs when bleeding from an external wound or internal ulcer reduces erythrocyte counts.
On the other...
 01:24
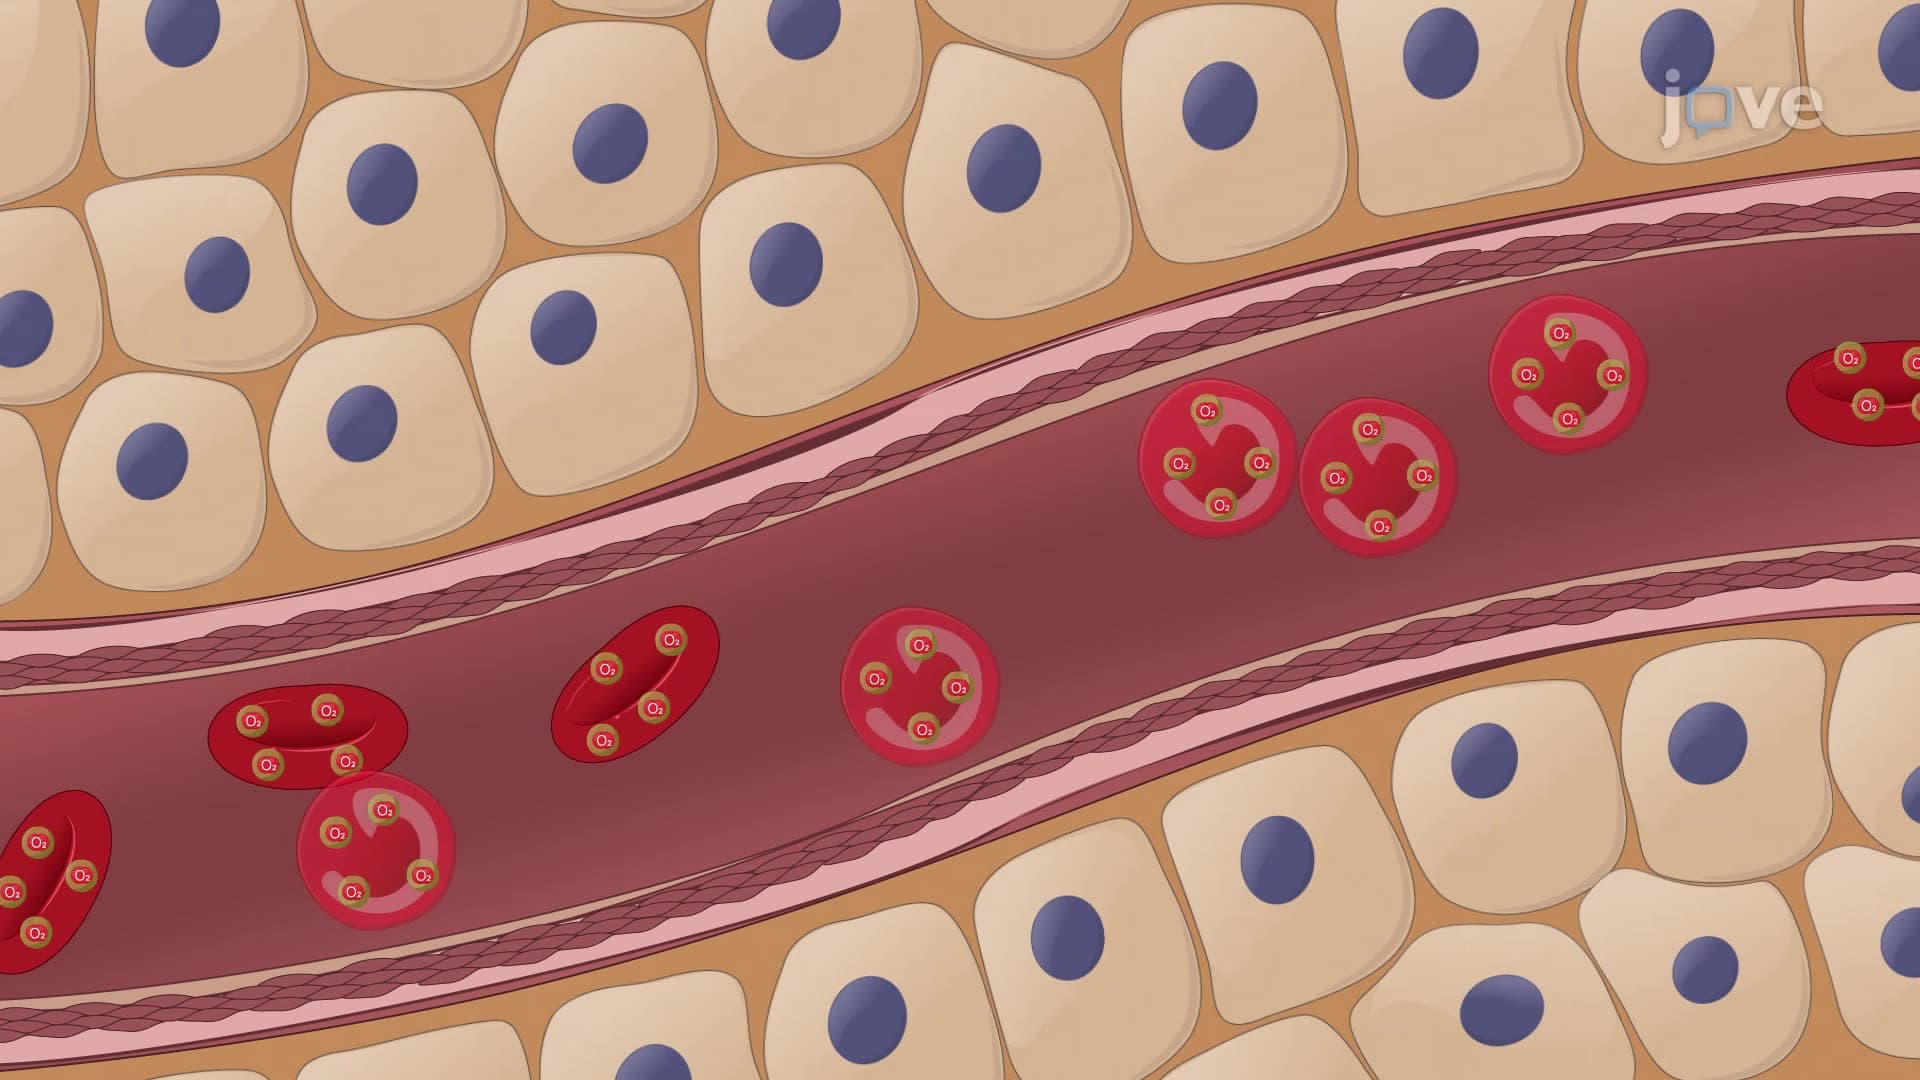
Factors Affecting Erythropoiesis
Several factors influence the erythrocyte production rate, with tissue oxygen level being among the most critical. Intense exercise or high altitudes can cause tissue hypoxia, which triggers the kidneys to release more erythropoietin (EPO) into the bloodstream.
EPO then...
 01:30
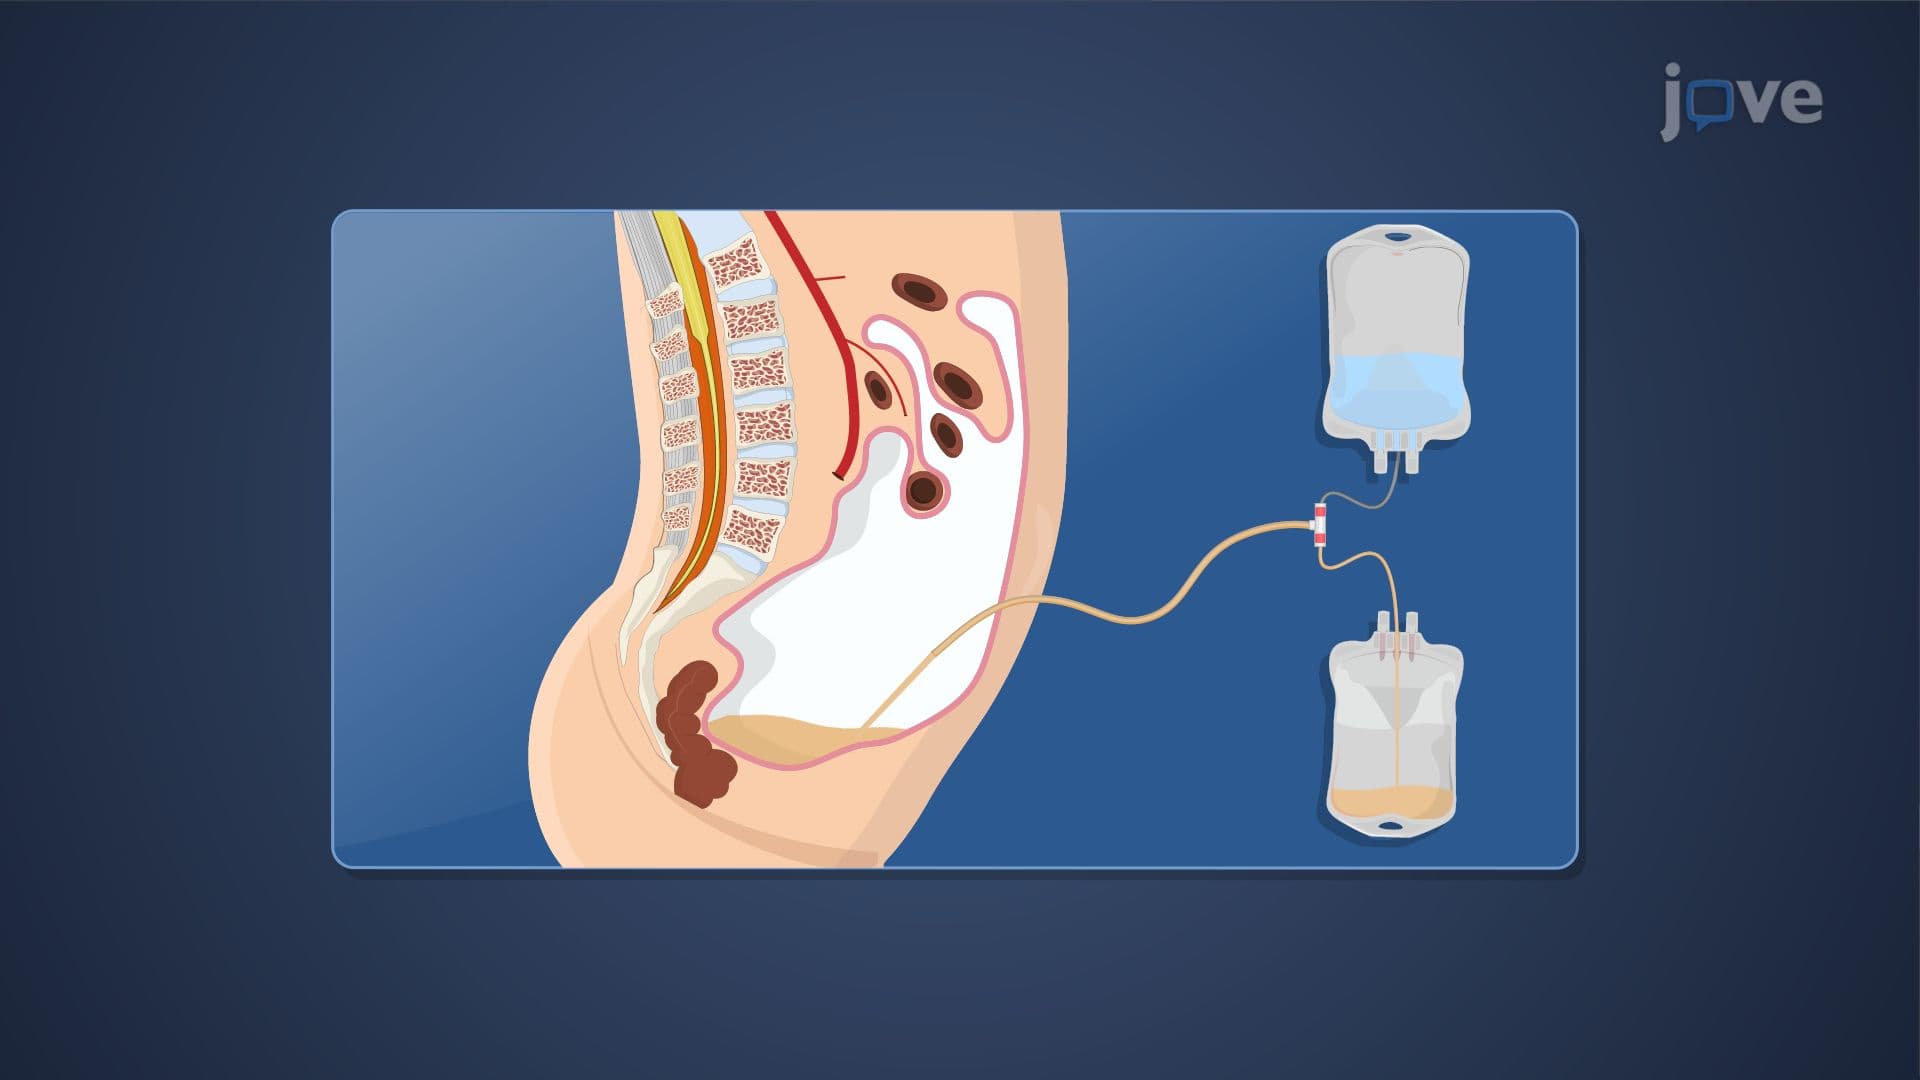
Extracorporeal Removal of Drugs: Peritoneal Dialysis and Hemodialysis
 01:25
Hemodialysis I: Introduction