Related Experiment Videos
Pregnancy-associated thrombosis
Ingrid Pabinger1, Helga Grafenhofer
1Division of Haematology and Blood Coagulation, Department of Internal Medicine I, University Hospital, Vienna, Austria. ingrid.pabinger@akh-wien.ac.at

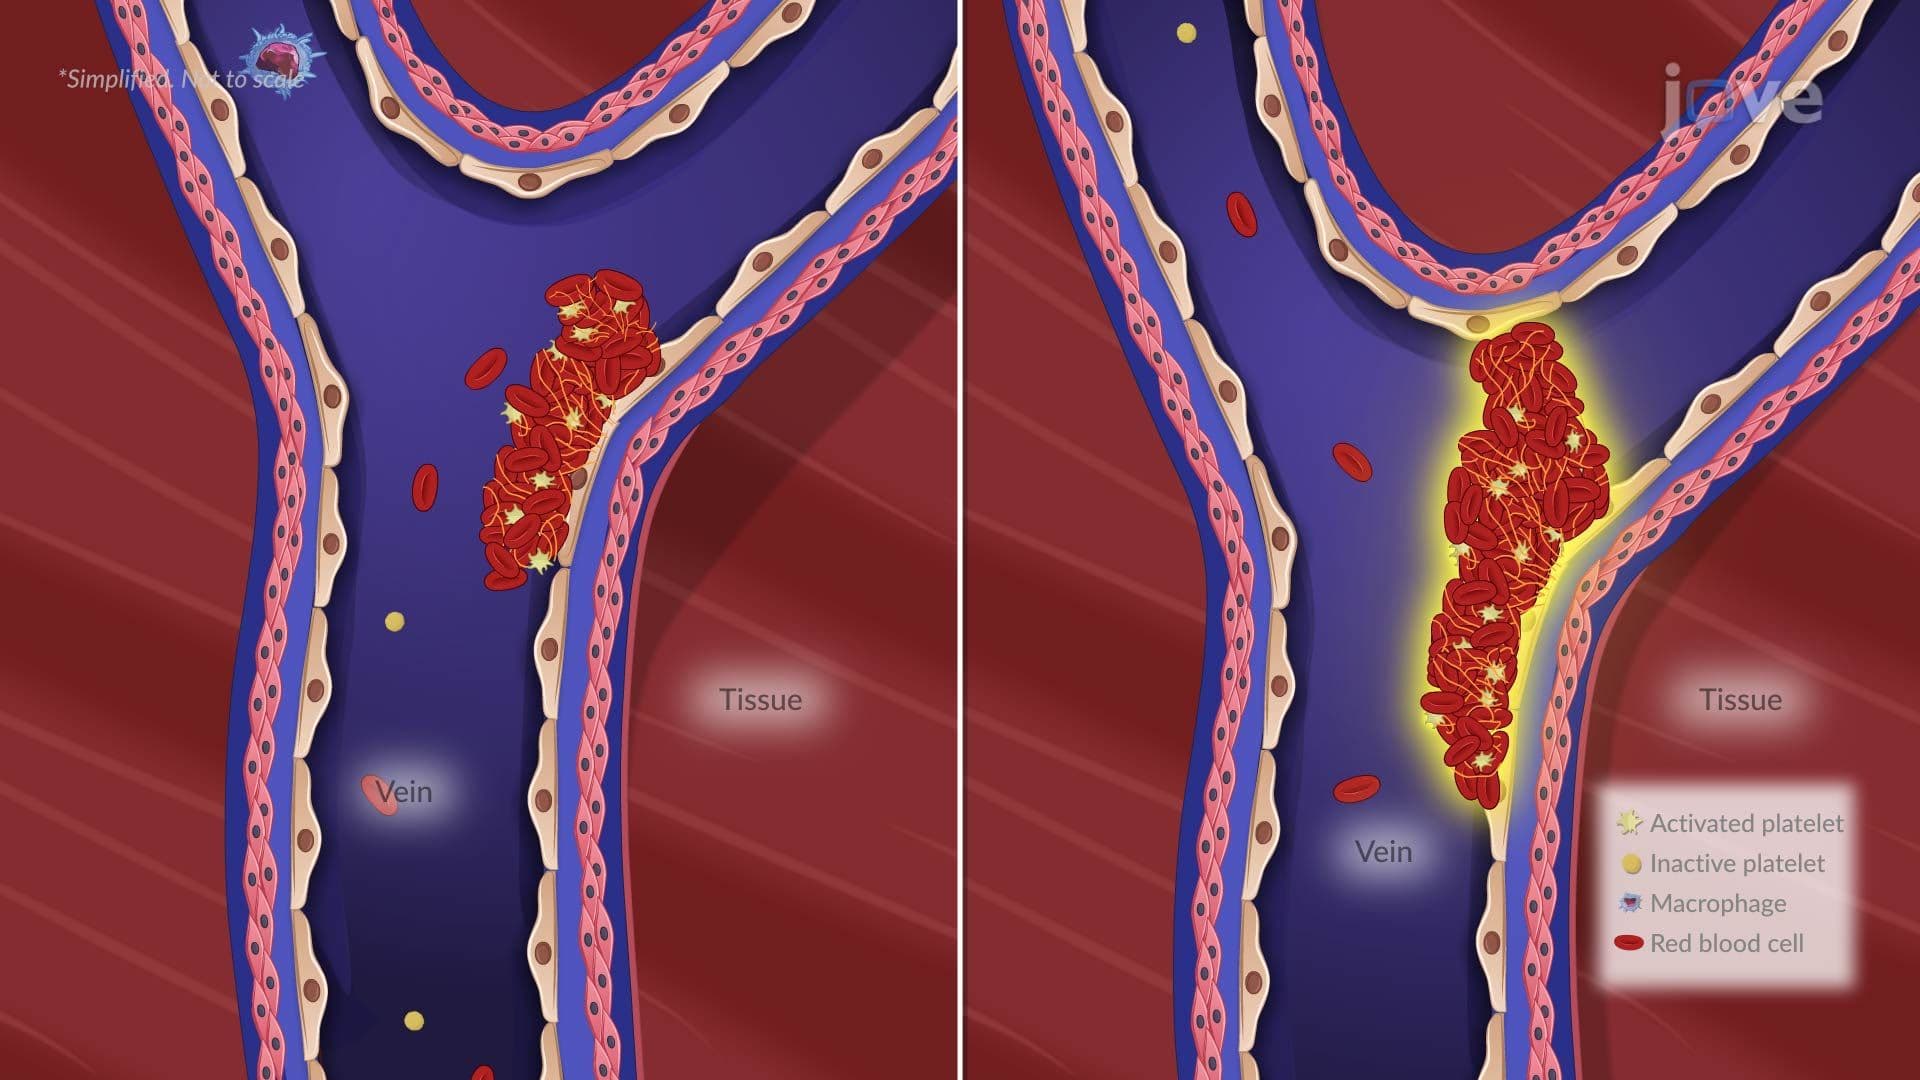
Venous thromboembolism (VTE) occurs infrequently but is a leading cause of illness and death during pregnancy and the puerperium. In the general population the incidence of pregnancy associated VTE is approximately 1 in 1500 deliveries The risk of VTE is five times higher in a pregnant than in a non-pregnant woman. Postpartum the VTE-risk is even higher. Women with congenital abnormalities or persistent presence of antiphospholipid antibodies have an increased risk of VTE during pregnancy and the puerperium. In individuals with well defined hereditary thrombosis risk factors, such as the factor V:R506Q mutation, the factor II:G20210A variation, antithrombin-deficiency or protein C-deficiency, a relative risk of pregnancy associated VTE between 3.4 and 15.2 has been found. Women with previous VTE have an approximately 3.5 fold increased risk of recurrent VTE during pregnancy compared to non-pregnant periods. Our ability to diagnose pregnancy-associated VTE clinically is generally poor, since dyspnea, tachypnea, swelling and discomfort in the legs are common. Objective diagnosis is essential for treatment decisions. Exposure to radiation of less than 50,000 microGy (5 rad) has not been associated with a significant risk of fetal injury Therefore, besides sonography, routine diagnostic procedures should be performed, if clinically necessary. Heparin does not cross the placenta and is therefore the anticoagulant of choice. In case of acute thrombosis during pregnancy, treatment is performed like in nonpregnant patients. There is ongoing debate, whether or not pregnant women with previous venous thrombosis should routinely receive prophylactic anticoagulation. In patients who have hereditary antithrombin deficiency, antiphospholipid antibodies, a combined abnormality or a history of a severe thrombotic event (pulmonary embolism, extended deep vein thrombosis) should be advised to use prophylactic heparin during pregnancy, starting during the first trimester. Post partum prophylaxis should be given in all women with an increased risk for VTE.
Venous thromboembolism (VTE) occurs infrequently but is a leading cause of illness and death during pregnancy and the puerperium. In the general population the incidence of pregnancy associated VTE is approximately 1 in 1500 deliveries The risk of VTE is five times higher in a pregnant than in a non-pregnant woman. Postpartum the VTE-risk is even higher. Women with congenital abnormalities or persistent presence of antiphospholipid antibodies have an increased risk of VTE during pregnancy and the puerperium. In individuals with well defined hereditary thrombosis risk factors, such as the factor V:R506Q mutation, the factor II:G20210A variation, antithrombin-deficiency or protein C-deficiency, a relative risk of pregnancy associated VTE between 3.4 and 15.2 has been found. Women with previous VTE have an approximately 3.5 fold increased risk of recurrent VTE during pregnancy compared to non-pregnant periods. Our ability to diagnose pregnancy-associated VTE clinically is generally poor, since dyspnea, tachypnea, swelling and discomfort in the legs are common. Objective diagnosis is essential for treatment decisions. Exposure to radiation of less than 50,000 microGy (5 rad) has not been associated with a significant risk of fetal injury Therefore, besides sonography, routine diagnostic procedures should be performed, if clinically necessary. Heparin does not cross the placenta and is therefore the anticoagulant of choice. In case of acute thrombosis during pregnancy, treatment is performed like in nonpregnant patients. There is ongoing debate, whether or not pregnant women with previous venous thrombosis should routinely receive prophylactic anticoagulation. In patients who have hereditary antithrombin deficiency, antiphospholipid antibodies, a combined abnormality or a history of a severe thrombotic event (pulmonary embolism, extended deep vein thrombosis) should be advised to use prophylactic heparin during pregnancy, starting during the first trimester. Post partum prophylaxis should be given in all women with an increased risk for VTE.
Related Concept Videos
 01:07
Teratogenicity
 01:19
Pulmonary Embolism I: Introduction
 01:29
Pulmonary Embolism I: Introduction
 01:19
Mitral Valve Prolapse III: Nursing Management
 01:30
Venous Thrombosis I: Introduction
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care