Related Experiment Video
Updated: Aug 12, 2026


Quantifying Acute Changes in Renal Sympathetic Nerve Activity in Response to Central Nervous System Manipulations in Anesthetized Rats
Published on: September 11, 2018
Selective adenosine-2 agonist produces both direct and reflex tachycardia in normotensive rats
R W Lappe1, J H Sheldon, B F Cox
1Rhône-Poulenc Rorer Central Research, King of Prussia, Pennsylvania.

Abstract:
Hemodynamic responses to intravenous (i.v.) injection of DPMA [N6-[2-(3,5-dimethoxyphenyl)-2-(2-methylphenyl)ethyl] adenosine); PD 125,944], a potent adenosine agonist with a 32-fold selectivity for the adenosine-2 (A2) receptor subtype, were characterized in conscious and anesthetized rats. In conscious rats instrumented with miniaturized pulsed-Doppler flow probes, i.v. injection of increasing doses of DPMA (3-30 micrograms/kg) had little effect on mean arterial pressure (MAP, maximal decrease -8 +/- 4 mm Hg) or renal and mesenteric resistance (maximal change 8 +/- 14 and 0 +/- 15%, respectively). In contrast, DPMA markedly reduced MAP (maximal decrease -61 +/- 8 mm Hg) in a dose-dependent (1-30 micrograms/kg) fashion in pentobarbital-anesthetized rats. The A2 agonist also caused a sustained, dose-dependent increase in heart rate (HR, maximal increase 75 +/- 12 beats/min) in conscious rats. The tachycardia and decrease in arterial pressure were completely reversed by i.v. administration of CGS 15943 (250 micrograms/kg), a selective adenosine receptor antagonist. Pretreatment with propranolol or hexamethonium significantly reduced but did not abolish the tachycardia, suggesting that the increase in HR was mediated only partially through reflex increases in sympathetic tone. These data indicate that (a) anesthesia potentiates the depressor actions of DPMA and (b) stimulation of A2 receptors increases HR through both direct and indirect mechanisms of action.


Related Concept Videos
 01:31
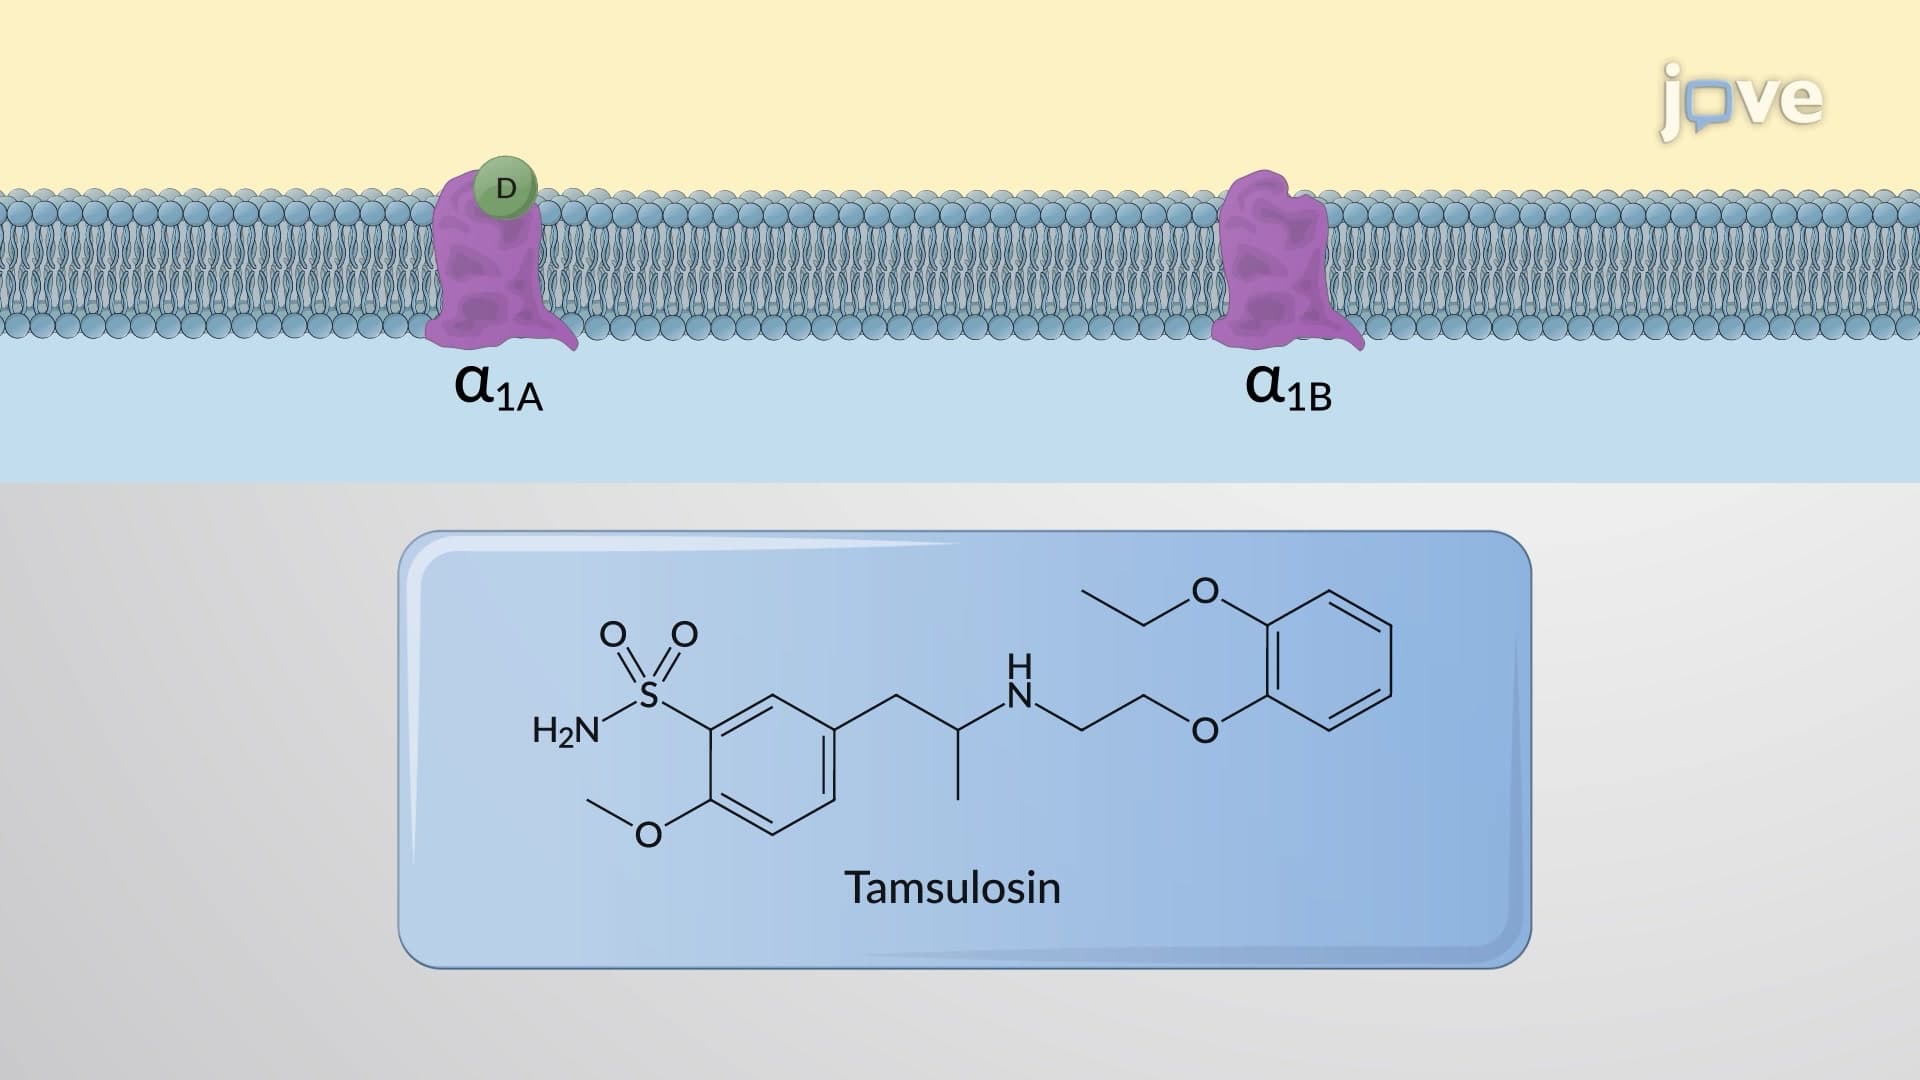
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:26
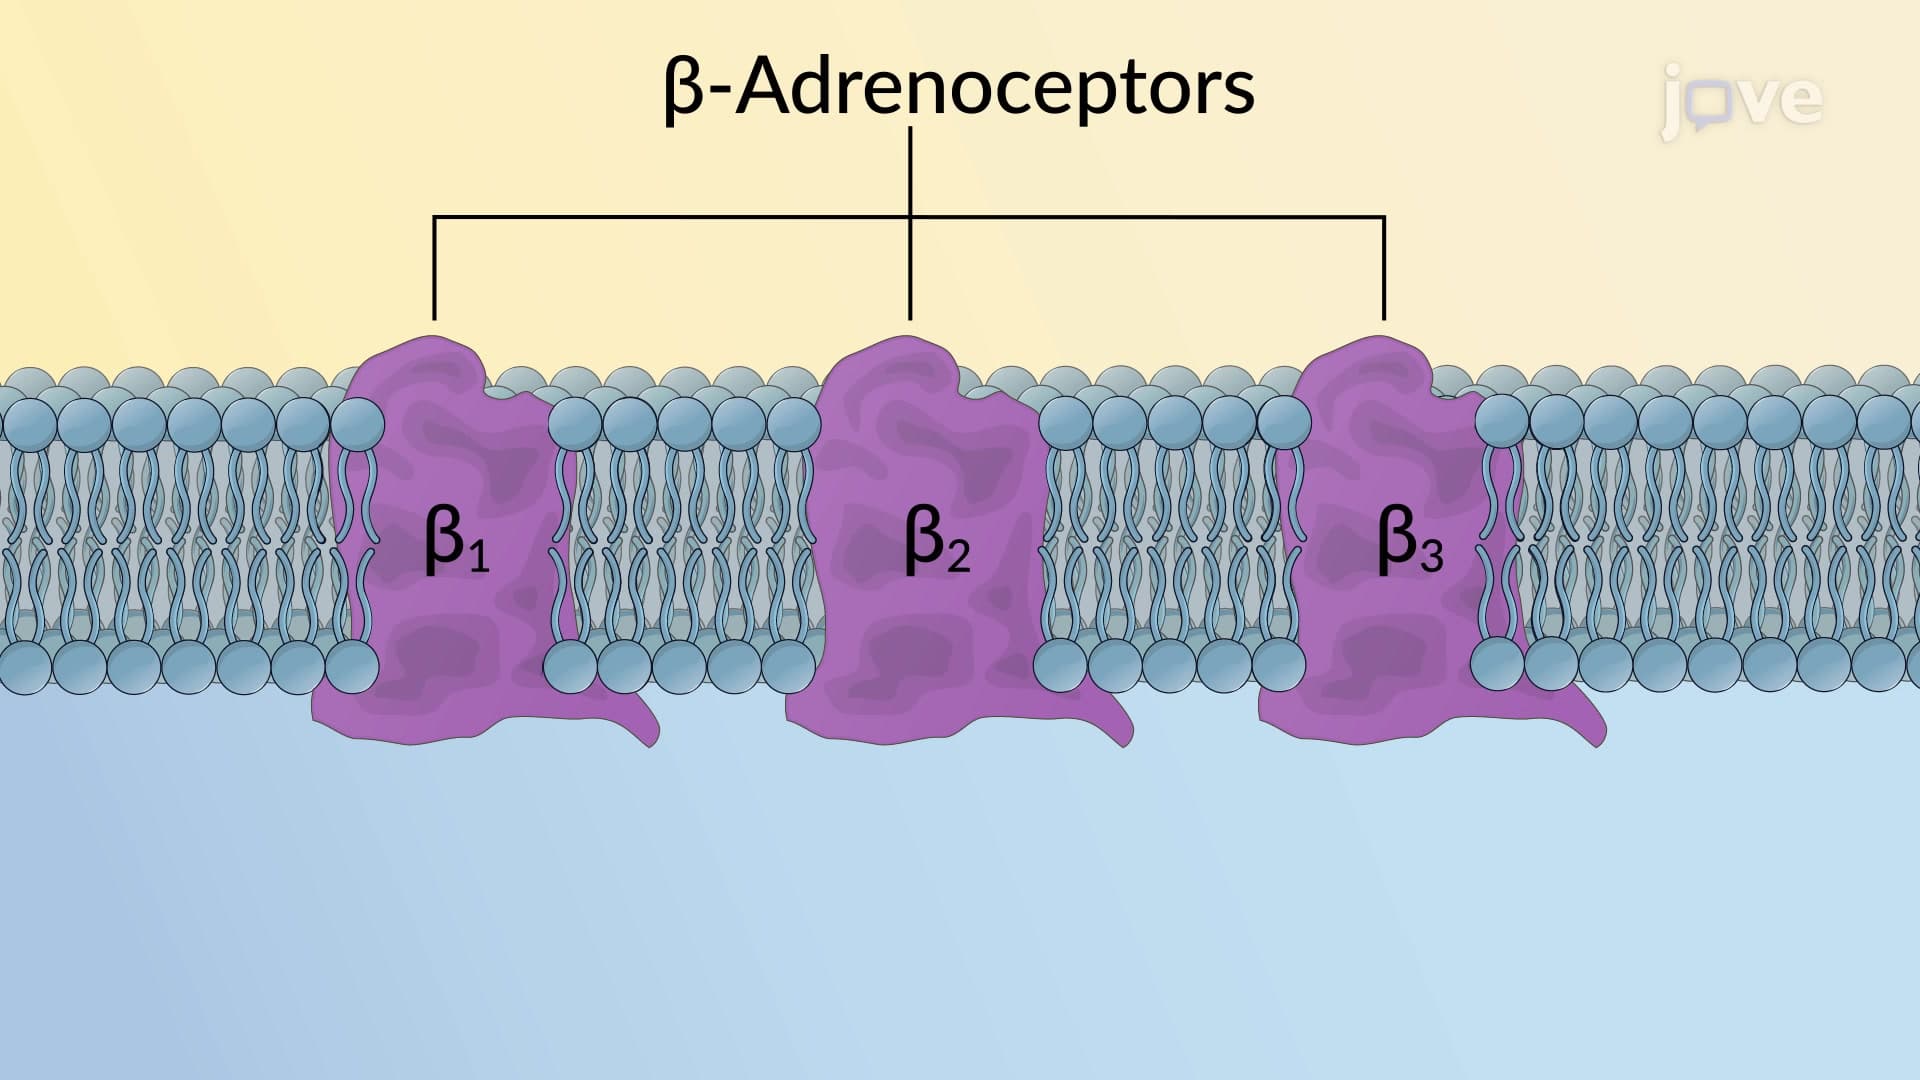
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:30
Adrenergic Agonists: Direct-Acting Agents
These agents can be classified...
 01:25
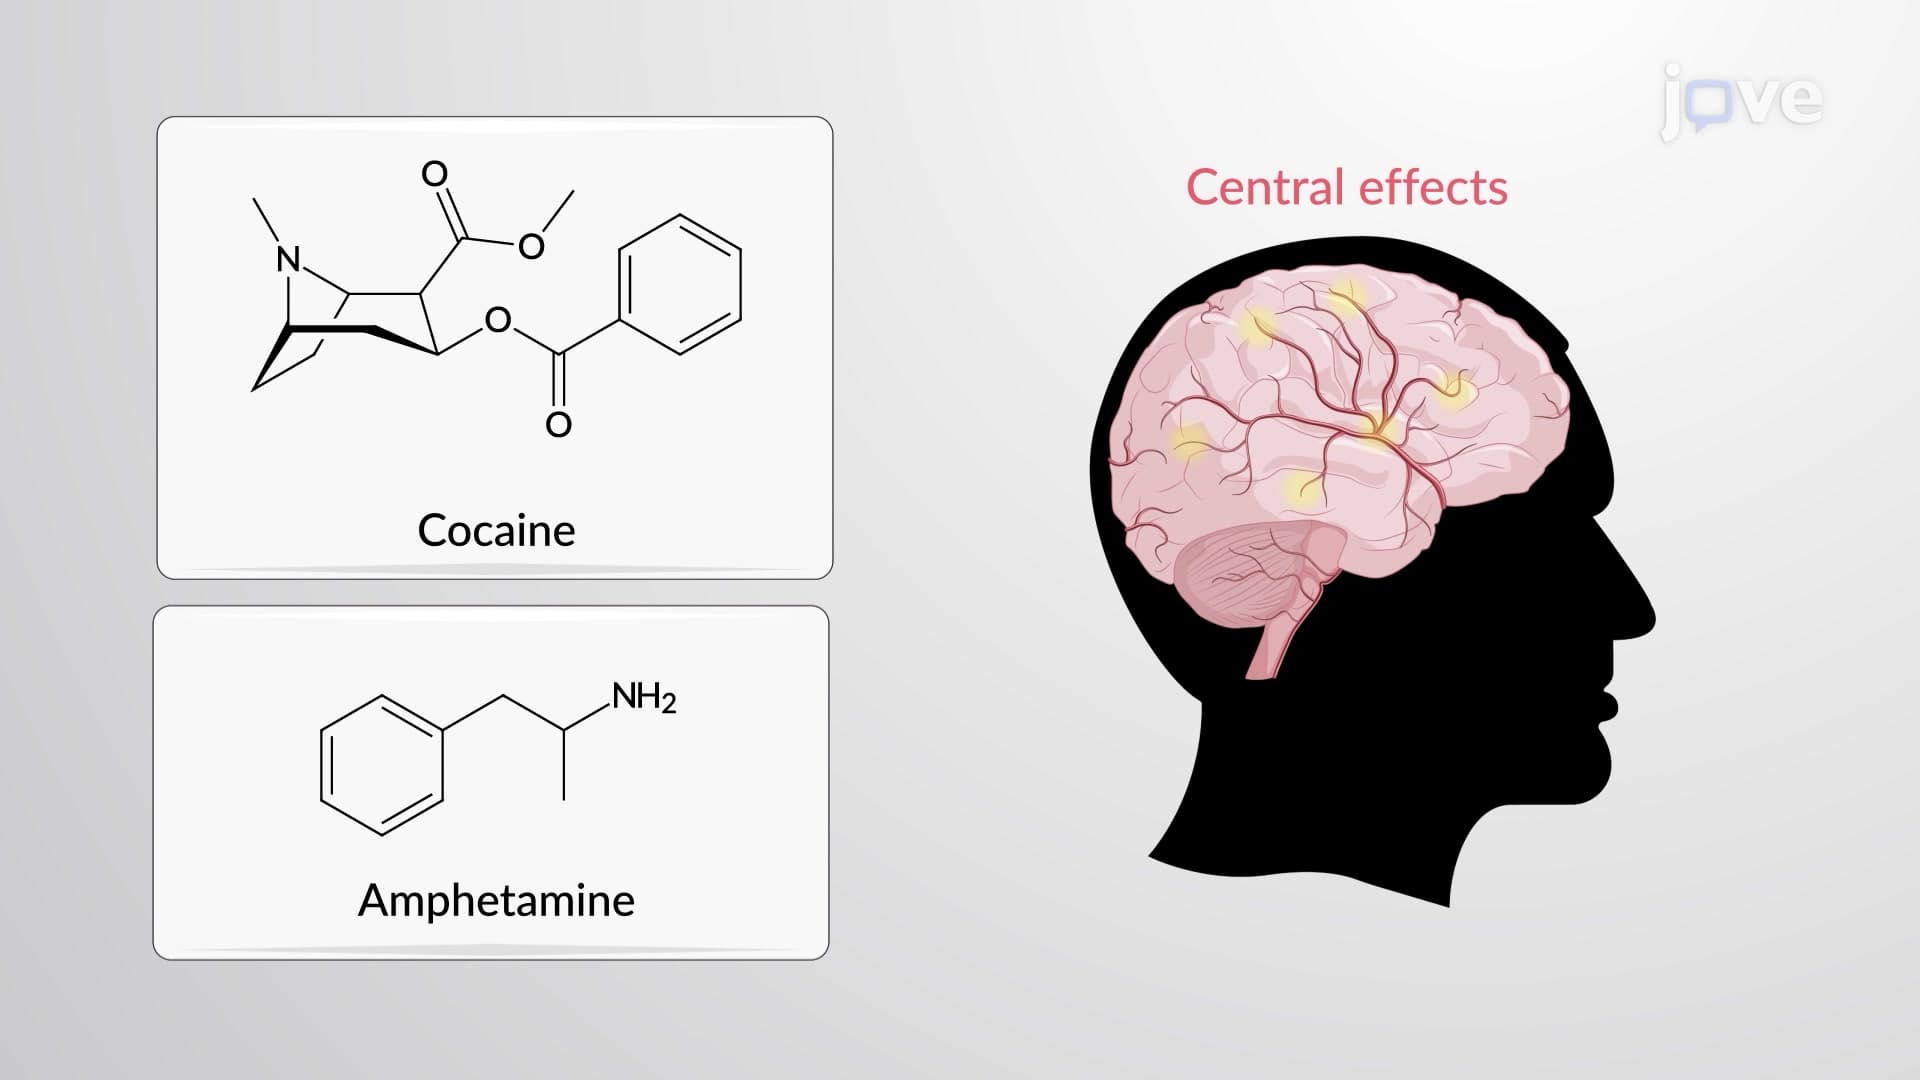
Adrenergic Agonists: Indirect-Acting Agents
One mechanism involves depleting stored catecholamines by displacing them from synaptic vesicles. These agents, known as "displacers," are transported into vesicles at the expense of noradrenaline. Examples include amphetamine and tyramine, which lack a catechol moiety, resulting in prolonged action, improved oral bioavailability, and...
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers