Related Experiment Video
Updated: Aug 12, 2026
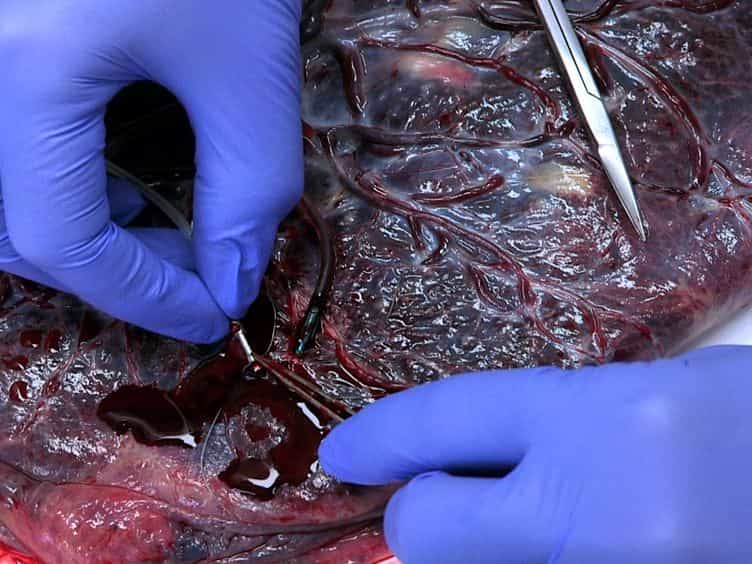

Determination of the Transport Rate of Xenobiotics and Nanomaterials Across the Placenta using the ex vivo Human Placental Perfusion Model
Published on: June 18, 2013
Placental glucose transport in heat-induced fetal growth retardation
P J Thureen1, K A Trembler, G Meschia
1Department of Pediatrics, University of Colorado School of Medicine, Denver 80262.

In six ewes heat stressed from 39 to 125 days gestation and studied in a normothermic environment at 135 days, fetal and placental masses were less than in control sheep (1,645 vs. 3,112 and 149 vs. 356 g, respectively, P less than 0.01). Umbilical glucose uptakes (Rf,UP) were measured keeping maternal arterial plasma glucose at 70 mg/dl at spontaneously occurring fetal plasma glucose values (state A) and at two additional fetal glucose levels, to determine the transplacental glucose difference (delta) vs. Rf,UP relation. At normal delta of 49.2 mg/dl, Rf,UP was less in the experimental group (3.2 vs. 5.6 mg.min-1.kg fetus-1, P less than 0.05). Differences in placental perfusion and glucose consumption could not account for this result, thus indicating a reduced placental glucose transport capacity. In state A, fetal hypoglycemia enlarged significantly (P less than 0.01) the delta to 56.7 mg/dl and increased Rf,UP approximately 50% over the Rf,UP at a normal delta. In heat-induced fetal growth retardation, fetal hypoglycemia increases the flux of maternal glucose across a placenta with reduced glucose transport capacity.
In six ewes heat stressed from 39 to 125 days gestation and studied in a normothermic environment at 135 days, fetal and placental masses were less than in control sheep (1,645 vs. 3,112 and 149 vs. 356 g, respectively, P less than 0.01). Umbilical glucose uptakes (Rf,UP) were measured keeping maternal arterial plasma glucose at 70 mg/dl at spontaneously occurring fetal plasma glucose values (state A) and at two additional fetal glucose levels, to determine the transplacental glucose difference (delta) vs. Rf,UP relation. At normal delta of 49.2 mg/dl, Rf,UP was less in the experimental group (3.2 vs. 5.6 mg.min-1.kg fetus-1, P less than 0.05). Differences in placental perfusion and glucose consumption could not account for this result, thus indicating a reduced placental glucose transport capacity. In state A, fetal hypoglycemia enlarged significantly (P less than 0.01) the delta to 56.7 mg/dl and increased Rf,UP approximately 50% over the Rf,UP at a normal delta. In heat-induced fetal growth retardation, fetal hypoglycemia increases the flux of maternal glucose across a placenta with reduced glucose transport capacity.


Related Concept Videos
 01:27
Glucose Transporters
Facilitated diffusion-glucose transporters (GLUTs) are encoded by the solute-linked carrier (SLC) family 2, subfamily A gene family, or SLC2A. The 14 GLUT protein members are distributed into three classes:
 01:26
Glucose Absorption Into the Small Intestine
 01:15
Transcytosis of IgG
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:02
Glucose Homeostasis: Regulation of Blood Glucose
During fasting, when blood glucose levels are low, the pancreas secretes glucagon. it...
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility, suggesting a...