Related Experiment Video
Updated: Jul 19, 2026
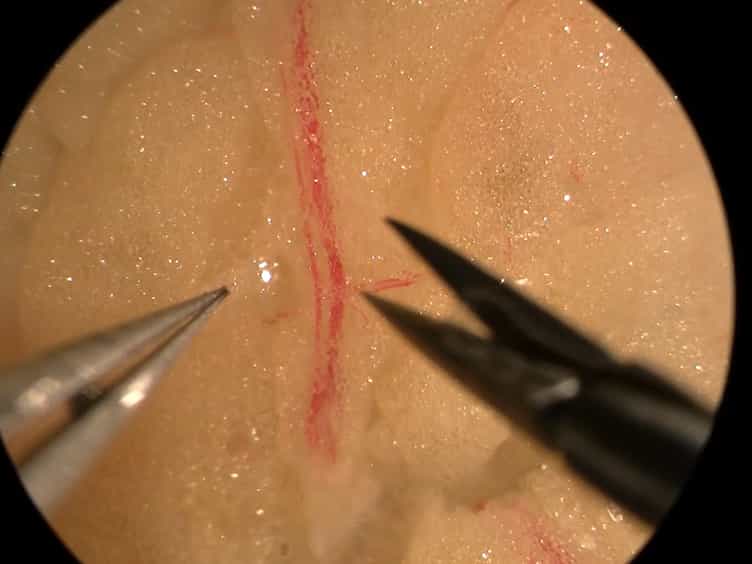

Assessment of Human Adipose Tissue Microvascular Function Using Videomicroscopy
Published on: September 29, 2017
Vasodilatory effects of adenosine A2 receptor agonists CGS 21680 and CGS 22492 in human vasculature
S R Makujina1, M H Sabouni, S Bhatia
1Department of Pharmacology, School of Medicine, East Carolina University, Greenville, NC 27858-4354.

Abstract:
The vasodilatory effects of the adenosine analogs, 5'-N-ethylcarboxamidoadenosine (NECA), 2-[p-(2-carboxyethyl)phenethyl amino]-5'-N-ethylcarboxamidoadenosine (CGS 21680) and 2-[(2-cyclohexylethyl)amino]adenosine (CGS 22492) in human coronary, internal mammary artery and saphenous vein were examined in vitro. All produced concentration-dependent relaxations in arterial as well as venous rings contracted with 35 mM KCl. The concentration-response curves for NECA and CGS 21680 were parallel in the coronary. The adenosine A2 receptor antagonist, 9-chloro-2-(2-furyl)[1,2,4]triazolo[1,5-c]quinazolin-5-amine (CGS 15943A) significantly attenuated the relaxing response to the adenosine analogs in coronary artery. Although NECA and CGS 22492 were equally as effective at the highest concentration administered (both achieving approximately 70% relaxation at 10(-4) M) NECA (EC50 = 1.25 +/- 0.11 microM) induced greater vasodilation at lower concentrations than CGS 22492 (EC50 = 11.27 +/- 1.53 microM). CGS 21680 was the least potent of the agents tested achieving only 44% relaxation at 10(-4) M (EC50 = 4.71 +/- 0.46 microM). Coronary artery appeared to be more responsive than internal mammary artery or saphenous vein which displayed only marginal relaxation to these agents.
More Related Videos


Related Concept Videos
 01:31
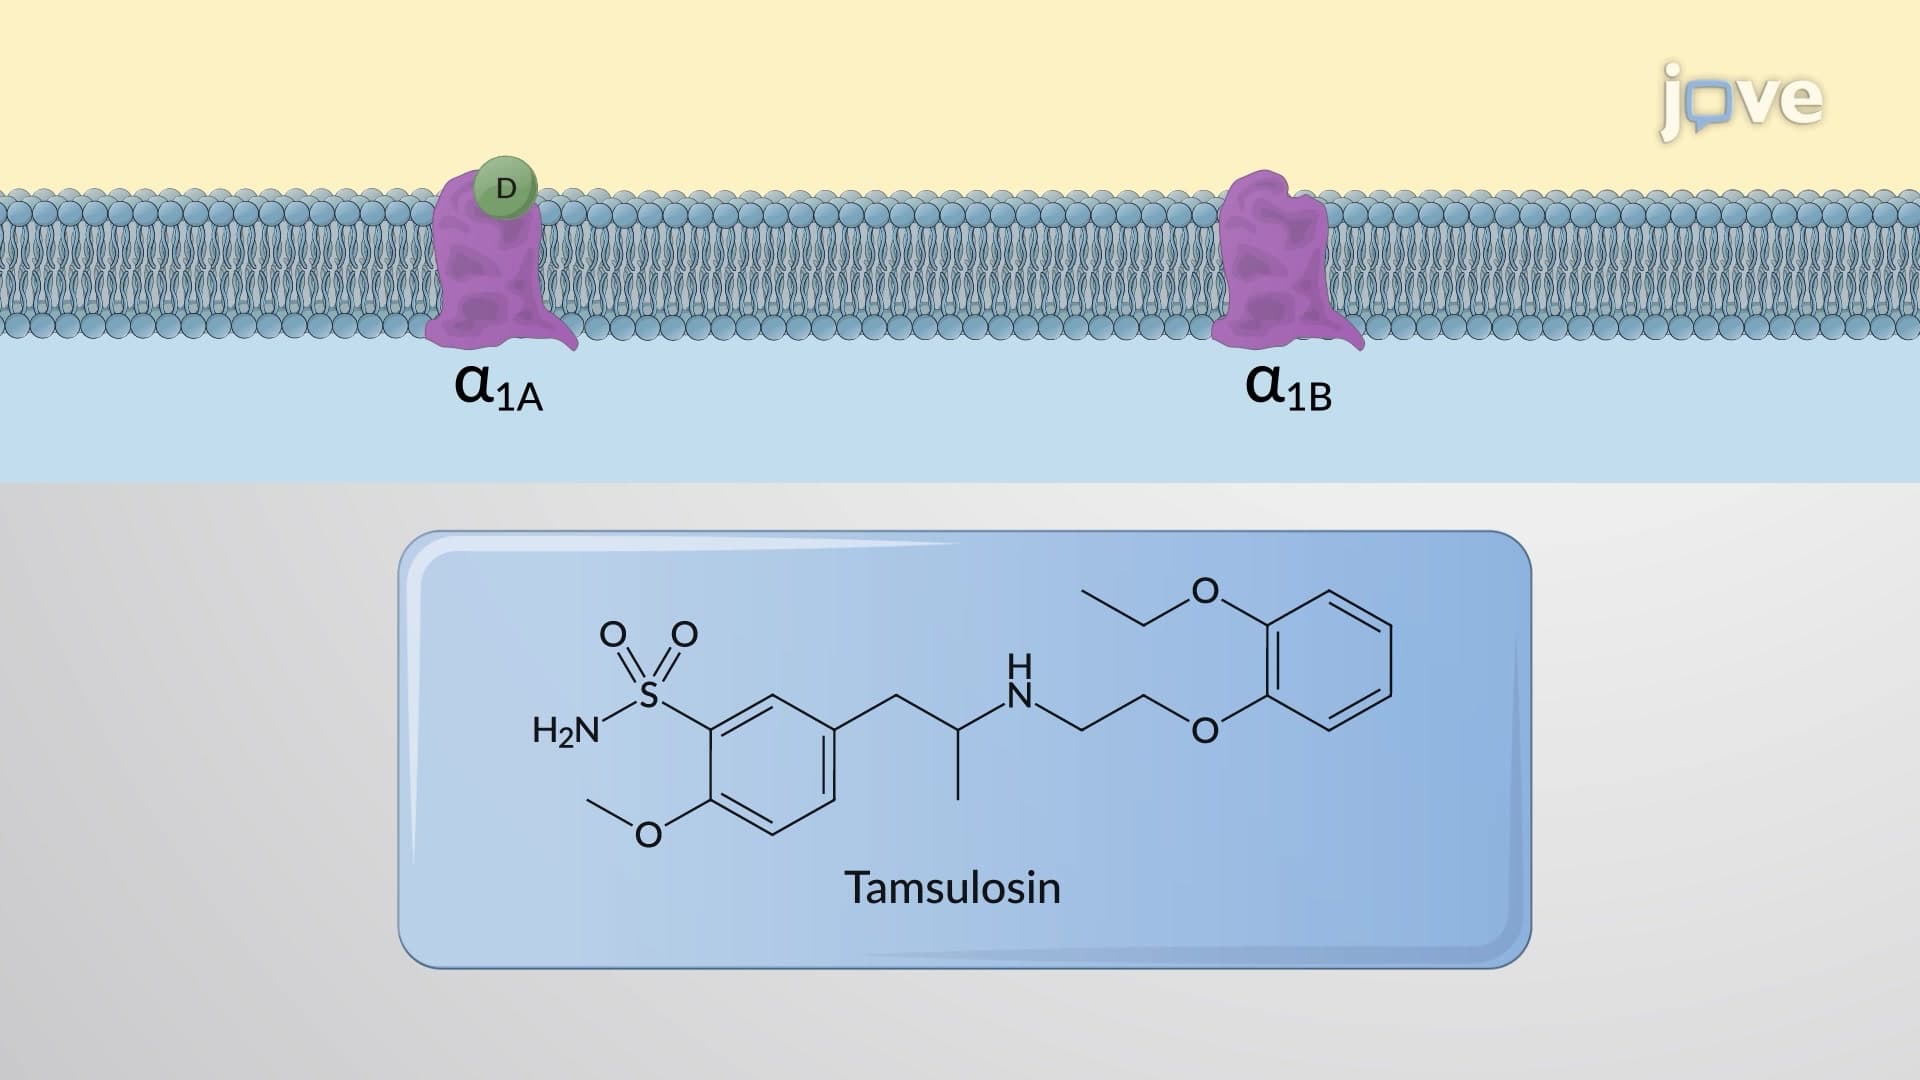
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:23
Antihypertensive Drugs: Vasodilators
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:16
Antianginal Drugs: Nitrates and β-Blockers
Organic nitrates, such as nitroglycerin, play a pivotal role. Once metabolized, they liberate nitric oxide, a molecular marvel. Nitric oxide triggers guanylyl cyclase and augments cGMP production. This biochemical cascade orchestrates the relaxation of vascular smooth muscles, ushering in vasodilation and enhancing coronary blood flow. Administered...
 01:25
Antianginal Drugs: Calcium Channel Blockers and Ranolazine
CCBs, a diverse class that includes dihydropyridines (nifedipine) and diphenylalkylamines (verapamil and diltiazem), exert their effect by blocking calcium channels in cardiac and smooth muscle cells. This...