Related Experiment Video
Updated: Aug 11, 2026


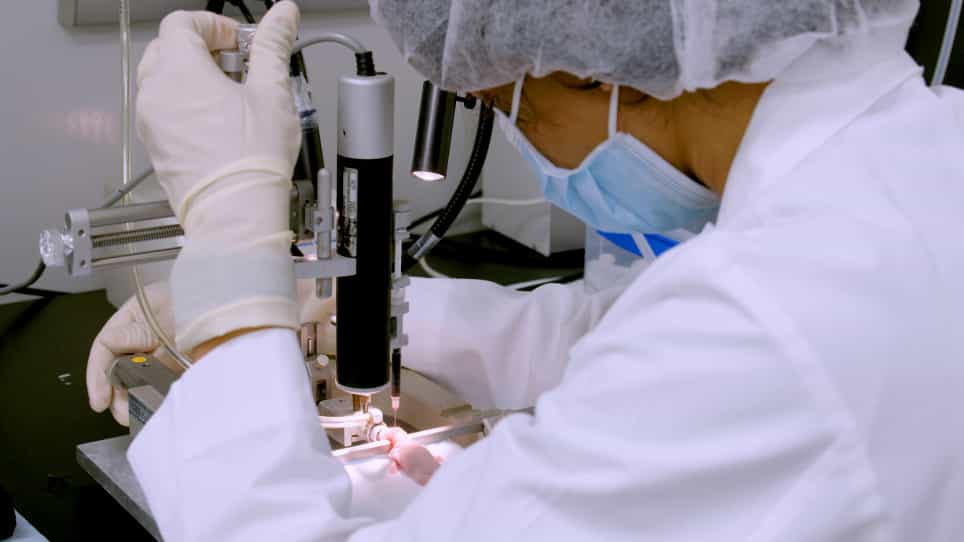
A Rat Model of Mild Intrauterine Hypoperfusion with Microcoil Stenosis
Published on: January 7, 2018
Risk factors for early intraventricular hemorrhage in low birth weight infants
1Department of Pediatrics, Yale University School of Medicine, New Haven, Connecticut 06511.

Insights
Early intraventricular hemorrhage (IVH) in preterm infants increases the risk of severe IVH and death. Mode of delivery, fetal presentation, and birth weight are key predictors of IVH in neonates.
Area of Science:
- Neonatal Medicine
- Pediatric Neurology
- Perinatal Research
Background:
- Germinal matrix hemorrhage/intraventricular hemorrhage (GMH/IVH) is a significant concern in preterm infants.
- Early GMH/IVH (within 12 postnatal hours) is associated with higher risks of severe hemorrhage and neurodevelopmental issues.
Purpose of the Study:
- To identify risk factors for early GMH/IVH in preterm neonates.
- To analyze the association between early GMH/IVH and subsequent severe hemorrhage, mortality, and delivery characteristics.
Main Methods:
- A multicenter study involving 229 neonates (600-1250 gm birth weight).
- Prospective data collection on risk factors and serial echoencephalography (ECHO) within the first 11 hours and for 20 days.
- Multivariate analysis to determine independent prognostic indicators.
Main Results:
- 43 infants experienced GMH/IVH within 5-11 hours.
- Early IVH group showed higher rates of vertex presentation (79% vs 55%), fewer maternal tocolytic uses (42% vs 60%), and more vaginal deliveries (67% vs 44%).
- Severe IVH developed more frequently in infants with early IVH (p < 0.001), along with increased neonatal mortality (16% vs 6%, p = 0.035).
Conclusions:
- Mode of delivery, fetal presentation, and birth weight are significant independent predictors of IVH.
- Early detection and management of risk factors may be crucial for improving outcomes in preterm infants at risk for IVH.
Abstract:
Because earlier studies suggested that preterm infants with germinal matrix hemorrhage or intraventricular hemorrhage or both (GMH/IVH) present within the first 12 postnatal hours are at greatest risk for the development of high-grade hemorrhage and neurodevelopmental disability, we examined the risk factors for this insult among 229 neonates of 600 to 1250 gm birth weight in a multicenter study. All had echoencephalography (ECHO) within the first 11 hours and serially for the next 20 days; risk factor data were collected prospectively. Forty-three infants had GMH/IVH within the first 5 to 11 hours (mean age at ECHO 7.7 hours): 18 GMH and 21 grade II, 1 grade III, and 3 grade IV IVH. One hundred eighty-six infants did not have GMH/IVH at a mean age of 7.9 hours. Both groups of infants were similar in birth weight, gestational age, maternal risk factors, cord pH values, and surfactant therapy before ECHO. The group with early IVH had more vertex presentations than the group without early IVH (79% vs 55%, p = 0.043), less maternal tocolytic use (42% vs 60%, p = 0.029), and more vaginal deliveries (67% vs 44%, p = 0.005). In the first 21 days, severe IVH developed in 12 infants with early IVH and in 6 infants without early IVH (p < 0.001). There were more neonatal deaths (16% vs 6%, p = 0.035) and more deaths at any time during the primary hospitalization (23% vs 9%, p = 0.010) among the early IVH group than among the group without early IVH. Multivariate analysis indicated that the mode of delivery, fetal presentation, and birth weight were important and independent prognostic indicators of IVH.

Related Concept Videos
 01:17
Hemorrhagic Stroke l: Introduction
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:14
Increased Intracranial Pressure l: Introduction