Related Experiment Video
Updated: Aug 5, 2026
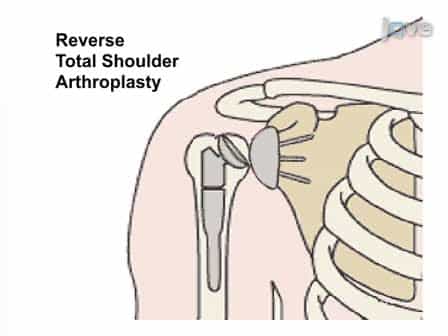
Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
The diagnosis and management of dystocia of the shoulder
J C Morrison1, J R Sanders, E F Magann
1Department of Obstetrics and Gynecology, University of Mississippi Medical Center, Jackson.

Dystocia of the shoulder is an unpredictable obstetric emergency that may result in injury to the mother or fetus. In an effort to reduce such risks, attempts have been made to identify patients having a fetus who may subsequently develop shoulder dystocia. The literature, however, clearly reflects that even the combination of prenatal historic facts, estimated fetal weight and sequence of intrapartum events is ineffective in prospectively identifying infants whose births are complicated by shoulder dystocia. During a ten year period at the University of Mississippi Medical Center, the incidence of macrosomia, shoulder dystocia and subsequent brachial plexus injury was reviewed. The majority of instances (89 percent) of shoulder dystocia occurred in patients weighing less than 8 pounds 13 ounces at birth. In the current retrospective review, only 11 percent of the women had risk factors for macrosomia or shoulder dystocia and among these, none were identified prospectively. Additionally, 91 percent of patients with brachial plexus injury recovered with no sequelae. One instance of brachial plexus injury occurred at the time of cesarean section. These data reveal that macrosomia and subsequent shoulder dystocia cannot be predicted. Therefore, it is not feasible to prevent brachial plexus injury prospectively by prophylactic cesarean section. Great clinical acumen and technical expertise by the obstetrician using a variety of methods may be useful in avoiding, as much as possible, injury to the mother and fetus when shoulder dystocia does occur.
Dystocia of the shoulder is an unpredictable obstetric emergency that may result in injury to the mother or fetus. In an effort to reduce such risks, attempts have been made to identify patients having a fetus who may subsequently develop shoulder dystocia. The literature, however, clearly reflects that even the combination of prenatal historic facts, estimated fetal weight and sequence of intrapartum events is ineffective in prospectively identifying infants whose births are complicated by shoulder dystocia. During a ten year period at the University of Mississippi Medical Center, the incidence of macrosomia, shoulder dystocia and subsequent brachial plexus injury was reviewed. The majority of instances (89 percent) of shoulder dystocia occurred in patients weighing less than 8 pounds 13 ounces at birth. In the current retrospective review, only 11 percent of the women had risk factors for macrosomia or shoulder dystocia and among these, none were identified prospectively. Additionally, 91 percent of patients with brachial plexus injury recovered with no sequelae. One instance of brachial plexus injury occurred at the time of cesarean section. These data reveal that macrosomia and subsequent shoulder dystocia cannot be predicted. Therefore, it is not feasible to prevent brachial plexus injury prospectively by prophylactic cesarean section. Great clinical acumen and technical expertise by the obstetrician using a variety of methods may be useful in avoiding, as much as possible, injury to the mother and fetus when shoulder dystocia does occur.
Related Concept Videos
 01:23
Muscles of the Shoulder
Anterior Thoracic Muscles
The anterior thoracic muscles include the serratus anterior, subclavius, and...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...