Related Experiment Video
Updated: Aug 9, 2026
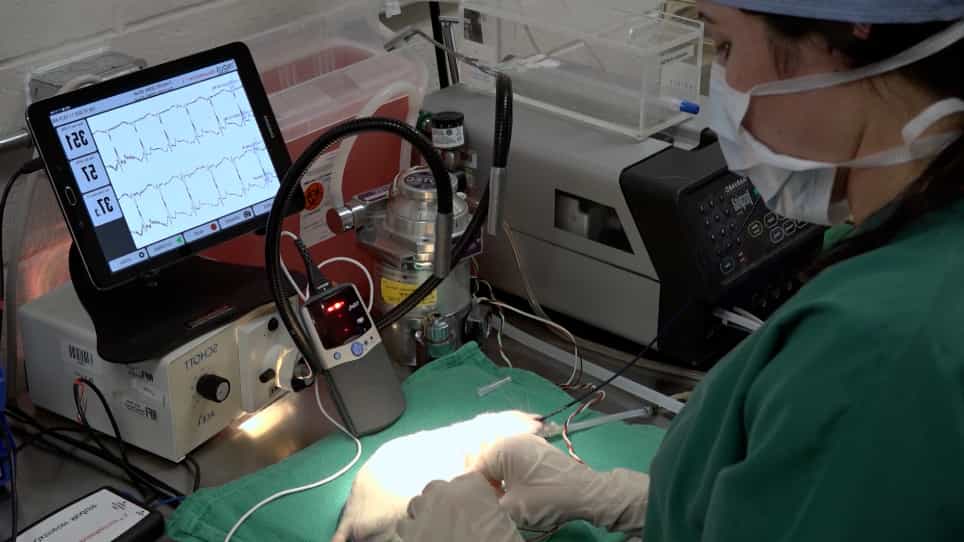

An Image Guided Transapical Mitral Valve Leaflet Puncture Model of Controlled Volume Overload from Mitral Regurgitation in the Rat
Published on: May 19, 2020
Mitral valve billowing and prolapse--an overview
1Department of Cardiology, University of the Witwatersand, Parktown, South Africa.

Insights
Mitral valve prolapse, often termed
Area of Science:
- Cardiology
- Pathology
- Echocardiography
Background:
- The origin of nonejection systolic clicks and late systolic murmurs is the mitral valve.
- A specific syndrome is linked to primary degenerative mitral valve lesions.
- Confusion persists regarding the term 'prolapse' for mitral valve anomalies.
Purpose of the Study:
- To clarify the distinction between normal mitral valve variants and pathological prolapse.
- To define the progression of mitral valve prolapse and its complications.
- To outline management strategies for mitral valve prolapse symptoms.
Main Methods:
- Echocardiography for evaluating mitral valve morphology.
- Morphological and histological examination of mitral valve tissue.
- Clinical assessment of patients with mitral valve prolapse.
Main Results:
- A spectrum exists from normal mitral leaflet billowing to advanced prolapse.
- True prolapse occurs with leaflet edge apposition failure, leading to mitral regurgitation.
- Complications include systemic emboli, infective endocarditis, arrhythmias, and autonomic dysfunction.
Conclusions:
- Distinguishing normal variants from pathological mitral valve prolapse is challenging.
- Mitral valve prolapse can progress to severe regurgitation and associated complications.
- Rheumatic anterior leaflet prolapse remains prevalent in certain regions.
Abstract:
Three decades after it was demonstrated that nonejection systolic clicks and late systolic murmurs have a mitral valve origin and that a specific syndrome is associated with the primary degenerative mitral lesion, numerous questions remain unanswered. A principal cause of confusion is the use of the term 'prolapse', which essentially implies a pathological state, in many patients with minimal evidence of a mitral valve anomaly. It should be recognised that no specific feature, whether evaluated by high standard echocardiography or indeed by careful morphological and histological examination, can be defined which distinguishes a normal variant from a pathological valve. There is a gradation from the normal billowing during ventricular systole of mitral leaflet bodies to marked billowing. With advanced billowing or floppy leaflets, failure of leaflet edge apposition supervenes (true prolapse). This is functionally abnormal and allows mitral regurgitation. Prolapse in turn may progress to a flail leaflet and hence gross regurgitation. Relatively rare complications of this degenerative mitral valve anomaly include systemic emboli, infective endocarditis, arrhythmias and, arguably, autonomic nervous system abnormalities. An attempt is made to clarify the management of some symptoms and other aspects of mitral prolapse-including rheumatic anterior leaflet prolapse (without billowing) which remains prevalent in South Africa and Third World countries.


Related Concept Videos
 01:27
Mitral Valve Prolapse I: Introduction
 01:22
Mitral Valve Prolapse II: Assessment and Management
 01:20
Mitral Regurgitation I: Introduction
 01:23
Mitral Regurgitation II: Clinical Features and Diagnostic Tests
 01:28
Mitral Regurgitation IV: Nursing Management
 01:22
Mitral Stenosis I: Introduction