Related Experiment Video
Updated: Aug 31, 2026
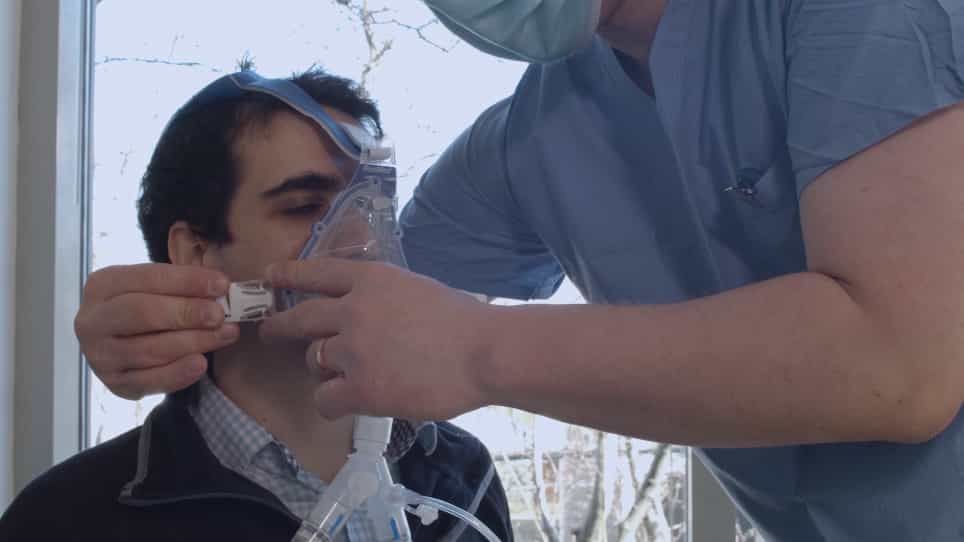

A Novel Inhalation Mask System to Deliver High Concentrations of Nitric Oxide Gas in Spontaneously Breathing Subjects
Published on: May 4, 2021
Inhaled nitric oxide for acute hypoxic respiratory failure in children and adults: a meta-analysis
Jennifer Sokol1, Susan Elizabeth Jacobs, Desmond Bohn
1*Department of Critical Care Medicine, Hospital for Sick Children, University of Toronto, Toronto, Ontario, Canada; †Department of Neonatology, School of Paediatrics and Child Health, University of Western Australia, Perth, Western Australia; and ‡Division of Neonatology, Royal Women's Hospital, University of Melbourne, Melbourne, Australia.

Abstract:
We systematically reviewed randomized controlled trials examining inhaled nitric oxide (INO) for the treatment of acute respiratory distress syndrome or acute lung injury in children and adults. Qualitative assessments of identified trials were made, and metaanalyses were performed according to Cochrane methodology. Five randomized controlled trials (n = 535) met entry criteria. One study demonstrated significant improvement in oxygenation in the first 4 days of treatment, with no difference after this. There was no difference in ventilator-free days between treatment and placebo groups, and no specific dose of INO was more advantageous than any other. INO had no effect on mortality in trials without crossover of treatment failures to open-label INO (relative risk, 0.98; 95% confidence interval, 0.66-1.44). Other clinical indicators of effectiveness, such as duration of hospital and intensive care stay, were inconsistently reported. Lack of data prevented assessment of all outcomes. If further trials assessing INO in acute respiratory distress syndrome or acute lung injury are to proceed, they should be stratified for primary etiology, incorporate other modalities that may affect outcome, and evaluate clinically relevant outcomes before any benefit of INO can be excluded.
Insights
Inhaled nitric oxide (INO) did not improve outcomes for acute respiratory distress syndrome or acute lung injury in children and adults. Further research is needed to determine potential benefits of INO in specific patient groups.
Area of Science:
- Critical Care Medicine
- Pulmonology
- Pediatric Critical Care
Background:
- Acute respiratory distress syndrome (ARDS) and acute lung injury (ALI) are severe conditions with high mortality.
- Inhaled nitric oxide (INO) has been investigated as a potential treatment to improve oxygenation and reduce lung injury.
Purpose of the Study:
- To systematically review randomized controlled trials (RCTs) evaluating the efficacy of INO in pediatric and adult patients with ARDS or ALI.
- To assess the impact of INO on mortality, oxygenation, and other clinical outcomes.
Main Methods:
- Systematic review and meta-analysis of RCTs adhering to Cochrane methodology.
- Included five RCTs with a total of 535 participants.
- Qualitative assessment and quantitative meta-analysis of pooled data.
Main Results:
- One study showed transient improvement in oxygenation within the first four days of INO treatment.
- No significant differences were observed in ventilator-free days or mortality between INO and placebo groups.
- No specific INO dosage demonstrated superior efficacy; inconsistent reporting of other clinical outcomes like hospital stay duration.
Conclusions:
- Current evidence does not support the routine use of INO for ARDS or ALI in children and adults.
- Further high-quality RCTs are recommended, stratified by etiology and incorporating other treatment modalities, to definitively assess INO's clinical relevance.

Related Concept Videos
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:19
Respiratory Assessment: Purpose and Indications
Objectives and Importance:
The primary goal of respiratory assessment is to evaluate patients at early risk of clinical deterioration. Since respiratory distress often precedes other signs of declining health, breathing patterns and sounds become a...
 01:16
Treatment for Pulmonary Arterial Hypertension: Oxygen Therapy for Respiratory Failure
Oxygen therapy is vital in increasing and maintaining blood oxygen levels in PAH patients. As a result, it aids in reducing fatigue, improving...
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:23
Acute Respiratory Failure-IV