Related Experiment Video
Updated: Aug 31, 2026


Platform for Quantitative Detection of Endometrial Immune Cells Based on Immunohistochemistry and Digital Image Analysis
Published on: October 13, 2023
Basal hormone levels in women with recurrent pregnancy loss
B Gürbüz1, S Yalti, C Fiçicioğlu
1Division of Reproductive Endocrinology and Infertility, Zeynep Kamil Women and Children Education and Research Hospital, Istanbul, Turkey. ahmetgurbuz2002@yahoo.com

Abstract:
The potential role of endocrine abnormalities during the follicular phase in women with unexplained recurrent pregnancy loss was investigated in a retrospective study. Eighty women with recurrent pregnancy loss underwent routine work-up to exclude known associations with the condition. Following investigation, 58 women failed to reveal an identifiable cause, and were therefore classified as having unexplained recurrent pregnancy loss. The control group consisted of women with known causes of abortions, such as uterine septum and parental chromosomal abnormalities. Mean age, gravidity, parity, presence of infertility, previous number of miscarriages and duration of marriage were similar in both groups. Day-3 serum levels of follicle stimulating hormone (FSH), estradiol, luteinizing hormone (LH) prolactin, total testosterone, dehydroepiandrosterone sulfate (DHEAS) and thyroid stimulating hormone (TSH) were compared in the two groups. FSH, estradiol, LH, prolactin and DHEAS concentrations were significantly higher in the unexplained recurrent pregnancy loss group than in the explained recurrent pregnancy loss group, although serum concentrations of all hormones were within the normal range (p < 0.01). TSH and total testosterone levels were similar in the two groups (p > 0.05). There were no differences in the frequency of abnormal levels of hormones between the two groups (p > 0.05). We conclude that endocrine abnormalities in the follicular phase are not associated with recurrent pregnancy loss.

Related Concept Videos
 01:27
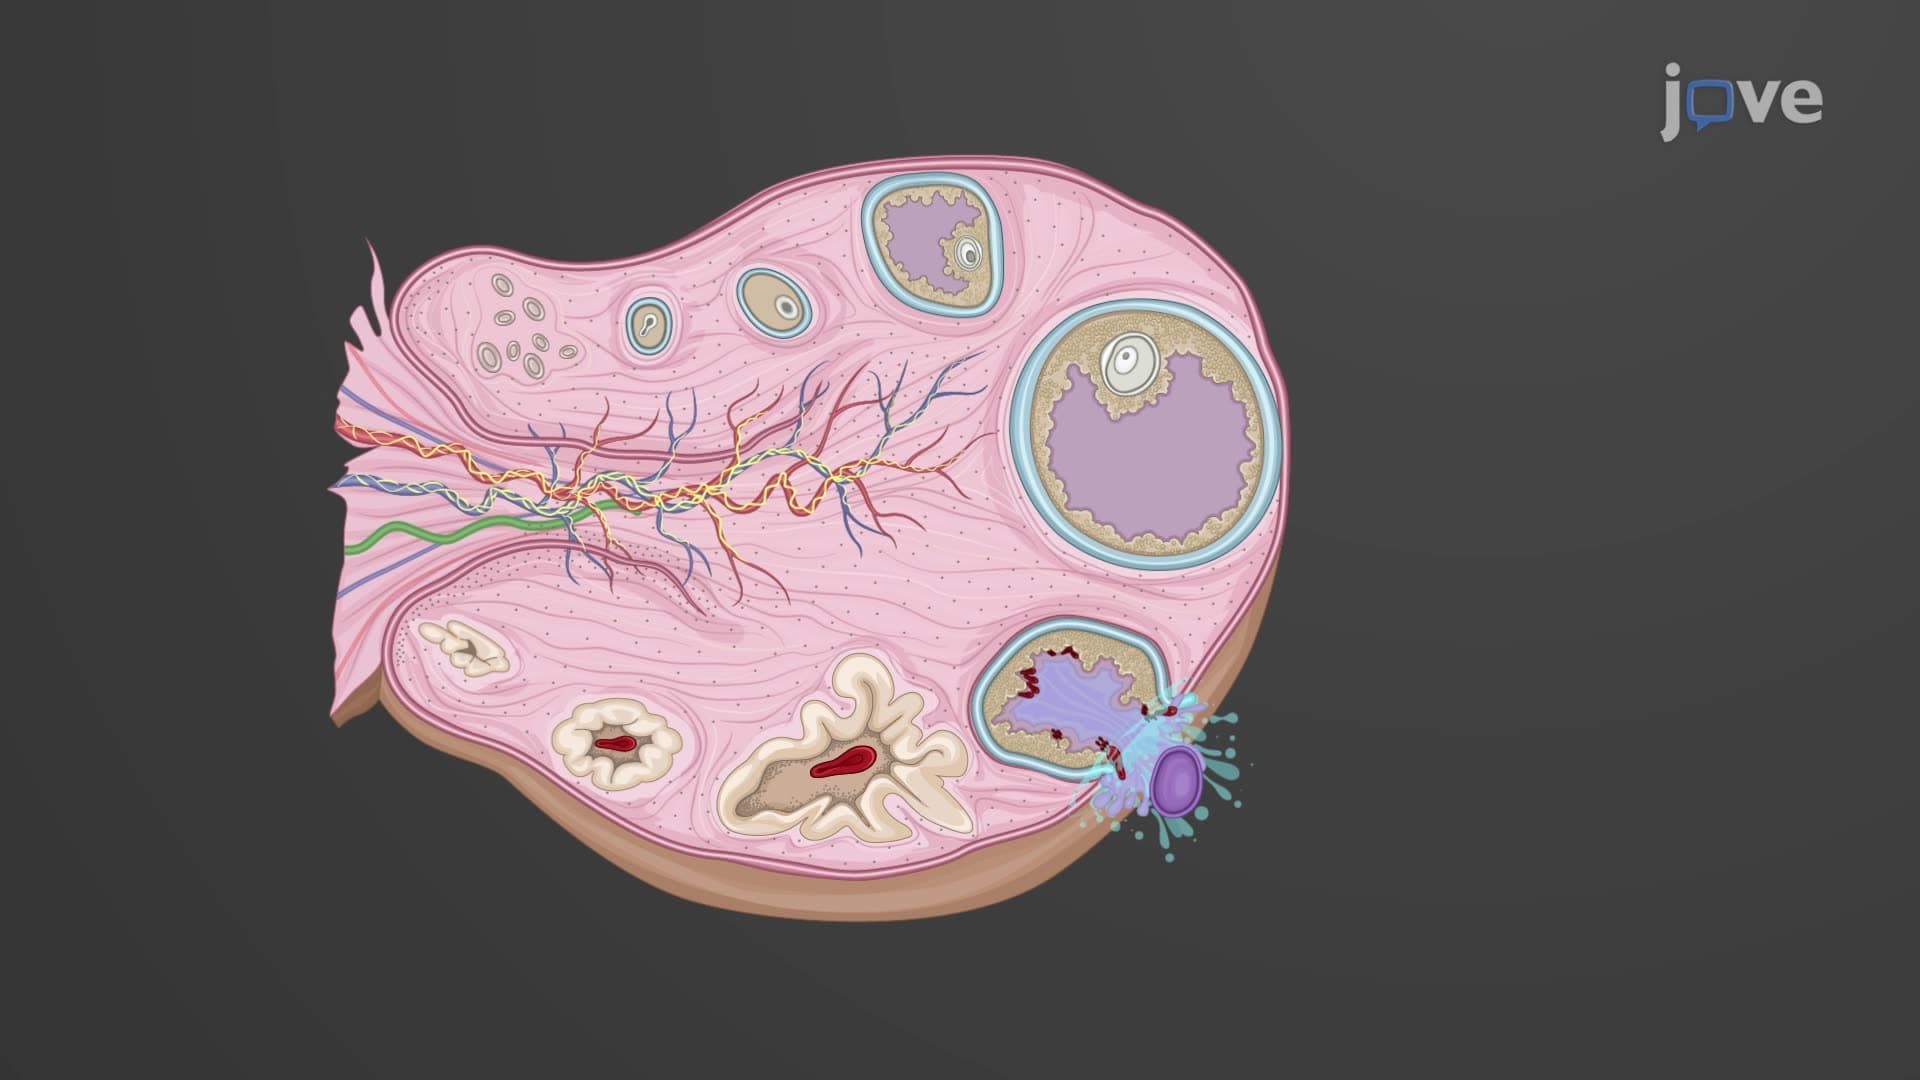
Ovarian Cycle
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:20
Proliferative Phase
Notably, the stratum basale, the basal layer of the endometrium, including the basal parts of the uterine glands, remains unaffected by menstruation. Stem cells in this layer undergo mitosis, regenerating the stratum functionalis and thickening the...
 01:24
Gonadal and Placental Hormones
In males, testosterone is the primary gonadal androgen. It plays a central role in the maturation of male reproductive organs — the penis and testes. Additionally, testosterone is instrumental in the development of secondary sexual characteristics — a deep voice as well as facial and pubic hair growth — and...
 01:28
Menopause