Related Experiment Video
Updated: Aug 31, 2026

Electrocardiogram Recordings in Anesthetized Mice using Lead II
Published on: June 20, 2020
Effect of phenylephrine provocation on dispersion of repolarization in congenital long QT syndrome
Anant Khositseth1, Jan Nemec, Joseph Hejlik
1Department of Pediatric and Adolescent Medicine/Division of Pediatric Cardiology, Mayo Clinic, Rochester, Minnesota 55905, USA.

Introduction:
Syncope and sudden death are associated with sympathetic stimulation in LQT1 while LQT2 patients are more susceptible to arrhythmias during nonexertional states. Abnormal spatial (QTd)- and transmural (TDR)-dispersion of repolarization may indicate increased arrhythmogenicity. This study compares the effect of phenylephrine on QTd and TDR in genotyped LQTS to control (C).
Methods And Results:
Seventeen LQT1, 12 LQT2, and 18 age- and sex-matched normal controls received 2 mcg/kg of phenylephrine intravenously. At baseline and peak phenylephrine effect, BP, QT, RR, Bazett's QTc, precordial QTd (QTmax-QTmin), and T-peak to T-end (Tp-e) intervals were determined blinded to the patient's clinical and genotype status. Baseline QT intervals and QTc were significantly longer in LQT1 and LQT2 compared to C. Baseline QTd and Tp-e were greater in LQT2 than either LQT1 or C: QTd=79+/-29 ms (LQT2), 53+/-26 (LQT1), and 45+/-15 (C) and Tp-e=120+/-30 ms (LQT2), 99+/-20 (LQT1), and 90+/-11 (C). Overall, phenylephrine exerted no significant effect on either QTd or Tp-e except with subgroup analysis of symptomatic LQTS where LQT1 and LQT2 patients had a divergent response with TDR.
Conclusions:
Phenylephrine-induced bradycardia decreased TDR in symptomatic LQT1 but increased TDR in symptomatic LQT2. The observed effects of phenylephrine are consistent with the protective effect of beta-blocker in LQT1 and the increased arrhythmogenicity noted during nonexertional states in LQT2.
More Related Videos
 08:28
Methods for ECG Evaluation of Indicators of Cardiac Risk, and Susceptibility to Aconitine-induced Arrhythmias in Rats Following Status Epilepticus
Published on: April 5, 2011
 09:36
Dual-Dye Optical Mapping of Hearts from RyR2R2474S Knock-In Mice of Catecholaminergic Polymorphic Ventricular Tachycardia
Published on: December 22, 2023
Related Concept Videos
 01:30
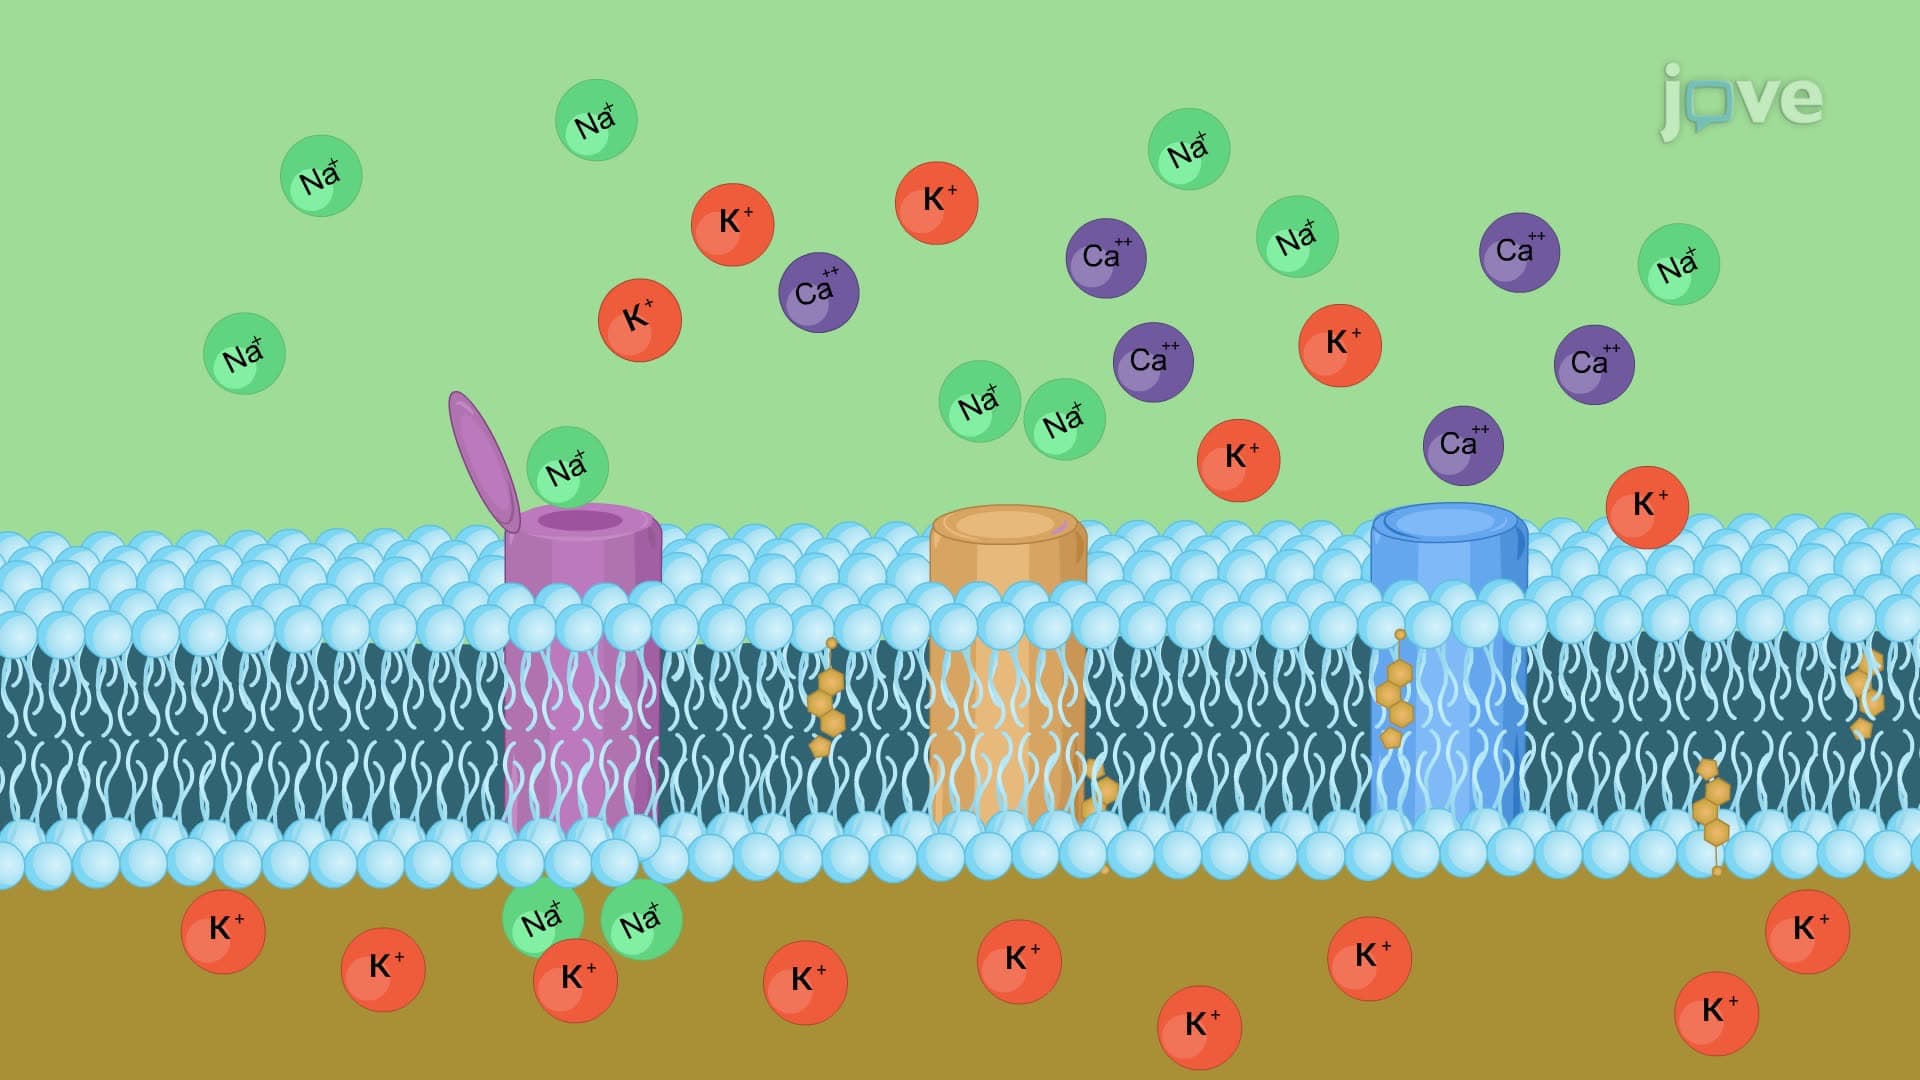
Cardiac Action Potential
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:20
Antiarrhythmic Drugs: Class IV Agents as Calcium Channel Blockers
Verapamil, a calcium channel blocker, inhibits calcium movement across myocardial cell membranes and vascular smooth muscle. This results in the dilation of coronary and...
 01:15
Pharmacodynamic Models: Linear Concentration–Effect Model
 01:22
Antiarrhythmic Drugs: Class I Agents as Sodium Channel Blockers
Class 1A Antiarrhythmic Drugs: These drugs work by moderately blocking sodium channels,...