Related Experiment Video
Updated: Aug 30, 2026


Modified Octopus Technique for Thoracoabdominal Aortic Aneurysm
Published on: August 1, 2025
Internal thoracic artery collateral to the external iliac artery in chronic aortoiliac occlusive disease
Jinna Kim1, Jong Yun Won, Sung Il Park
1Department of Diagnostic Radiology and Research Institute of Radiological Science, Yonsei University College of Medicine, Seoul, Korea. dyl@yumc.yonsei.ac.kr

Insights
In chronic aortoiliac occlusive disease, the internal thoracic artery is a key collateral pathway. This study found it consistently provided collateral perfusion in patients with severe aortoiliac obstruction.
Area of Science:
- Vascular Surgery
- Interventional Radiology
- Cardiovascular Medicine
Background:
- Chronic aortoiliac occlusive disease (CAOD) significantly impacts lower limb perfusion.
- Understanding collateral circulation is crucial for managing CAOD.
- The role of the internal thoracic artery (ITA) in CAOD collateralization requires further elucidation.
Purpose of the Study:
- To determine the incidence of ITA involvement in collateral pathways for CAOD.
- To describe the angiographic characteristics of ITA-mediated collateral flow in CAOD.
- To assess the significance of the ITA as a collateral route in severe aortoiliac disease.
Main Methods:
- Retrospective analysis of 124 patients with CAOD undergoing angiography.
- Detailed evaluation of aortograms and collateral arteriograms, including ITAs, in 15 patients with severe obstruction.
- Review of medical records to correlate findings with clinical presentation.
Main Results:
- All 15 patients with severe aortoiliac obstruction demonstrated collateral perfusion via hypertrophied ITAs.
- Rich anastomoses between superior and inferior epigastric arteries were observed, reconstituting external iliac artery flow.
- ITA collateralization was present irrespective of symptom duration, ranging from six months to twelve years.
Conclusions:
- The internal thoracic artery serves as a major parietal collateral pathway in patients with CAOD.
- ITA collaterals, alongside visceral and contralateral pathways, are vital for maintaining perfusion in severe aortoiliac disease.
- Angiographic identification of ITA collateralization is important for comprehensive assessment of CAOD.
Objective:
To evaluate the incidence and angiographic findings of the collateral pathway involving the internal thoracic artery in patients with chronic aortoiliac occlusive disease.
Materials And Methods:
Between March 2000 and Februrary 2001, 124 patients at our hospital underwent angiographic evaluation of chronic aortoiliac occlusive disease, and in 15 of these complete obstruction or severe stenosis of the aortoiliac artery was identified. The aortograms and collateral arteriograms obtained, including internal thoracic arteriograms, as well as the medical records of the patients involved, were evaluated.
Results:
In nine patients there was complete occlusion of the infrarenal aorta, or diffuse stenosis of 75% or more in the descending thoracic aorta, and in the other six, a patent aorta but complete occlusion or stenosis of 75% or more of the common iliac artery was demonstrated. Collateral perfusion via hypertrophied internal thoracic arteries and rich anastomoses between the superior and inferior epigastric arteries, reconstituting the external iliac artery, were noted in all fifteen patients, regardless of symptom duration, which ranged from six months to twelve years.
Conclusion:
In patients with chronic aortoiliac occlusive disease, the internal thoracic artery, along with visceral collaterals and those from the contralateral side, is one of the major parietal collateral pathways.

Related Concept Videos
 01:25
Abdominal Aorta
The celiac trunk, a singular artery, divides into the left gastric artery, which...
 01:20
Arteries of Lower Limbs
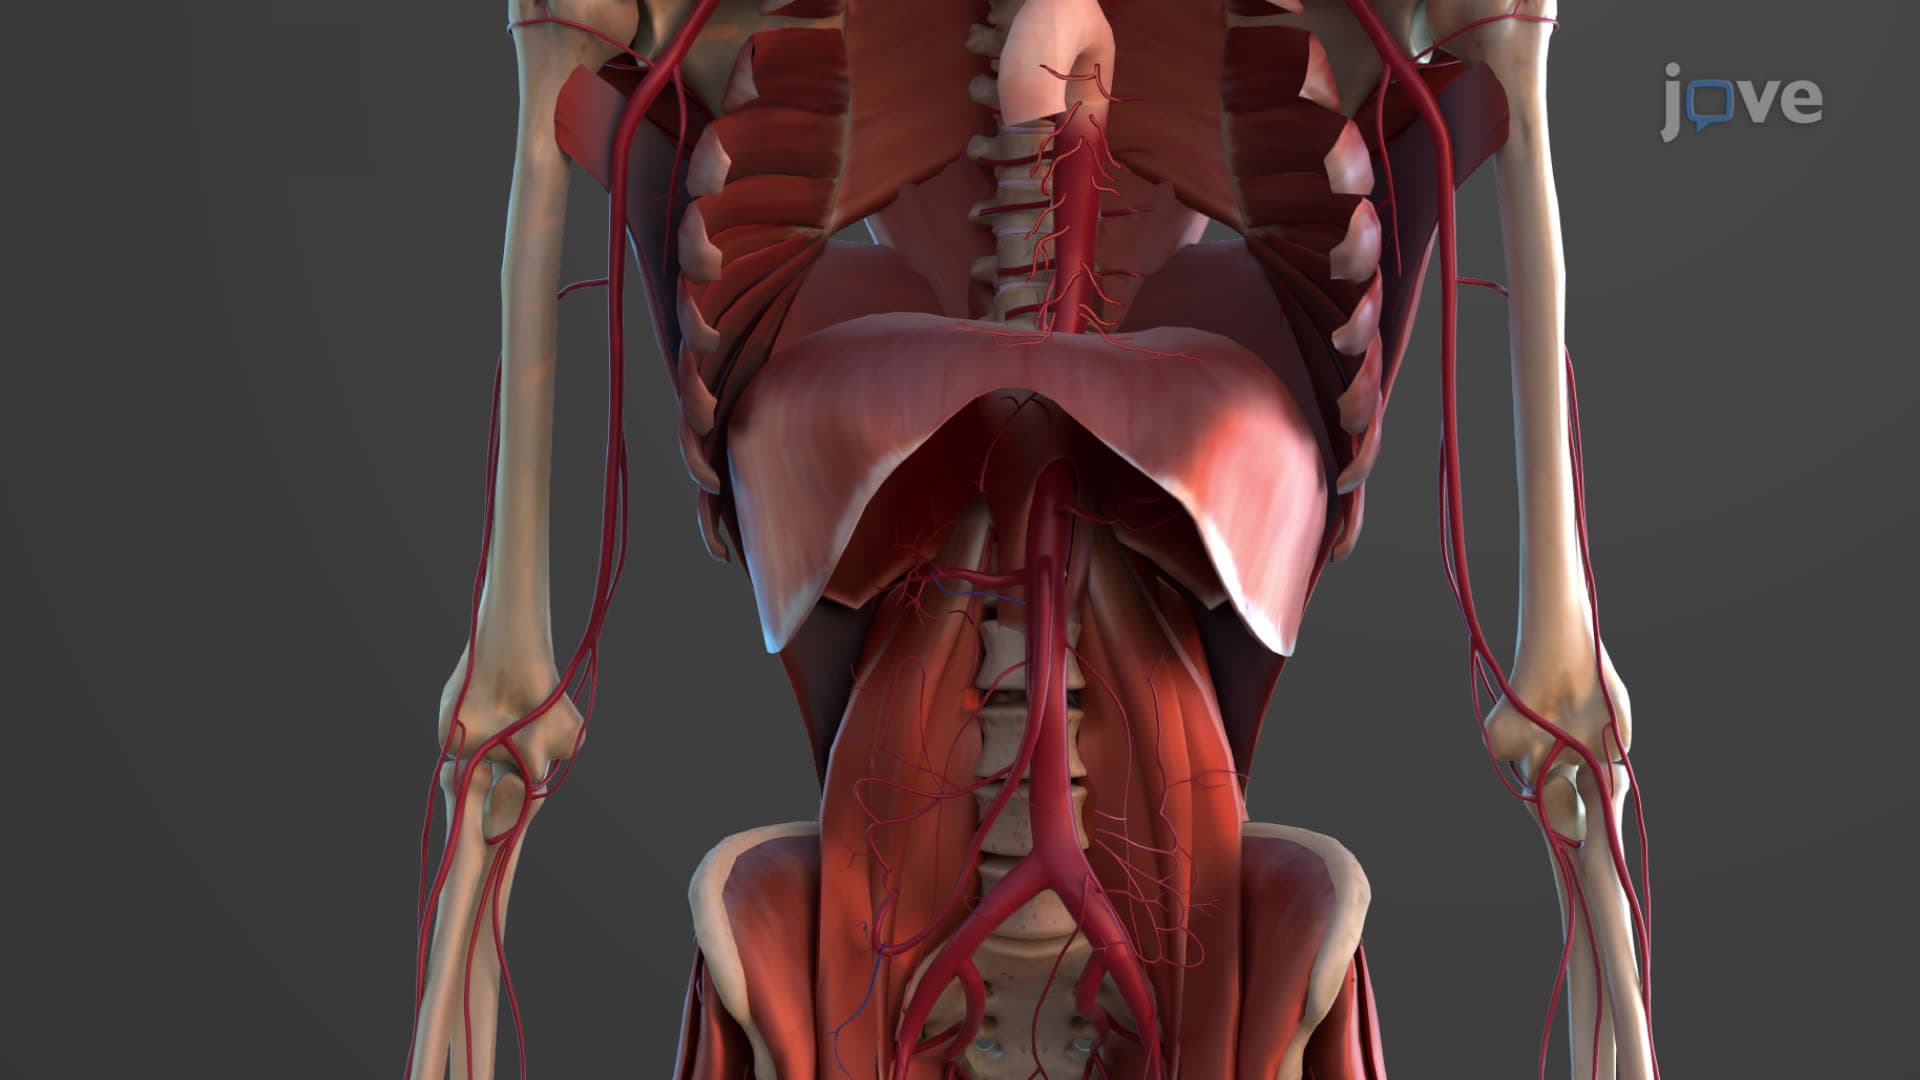 01:15
Thoracic Aorta
 01:10
The Arch of Aorta
Encircling the heart, the coronary arteries form a ring-like structure before...
 01:26
Aneurysm III: Interprofessional Care
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies