Related Experiment Video
Updated: Aug 30, 2026
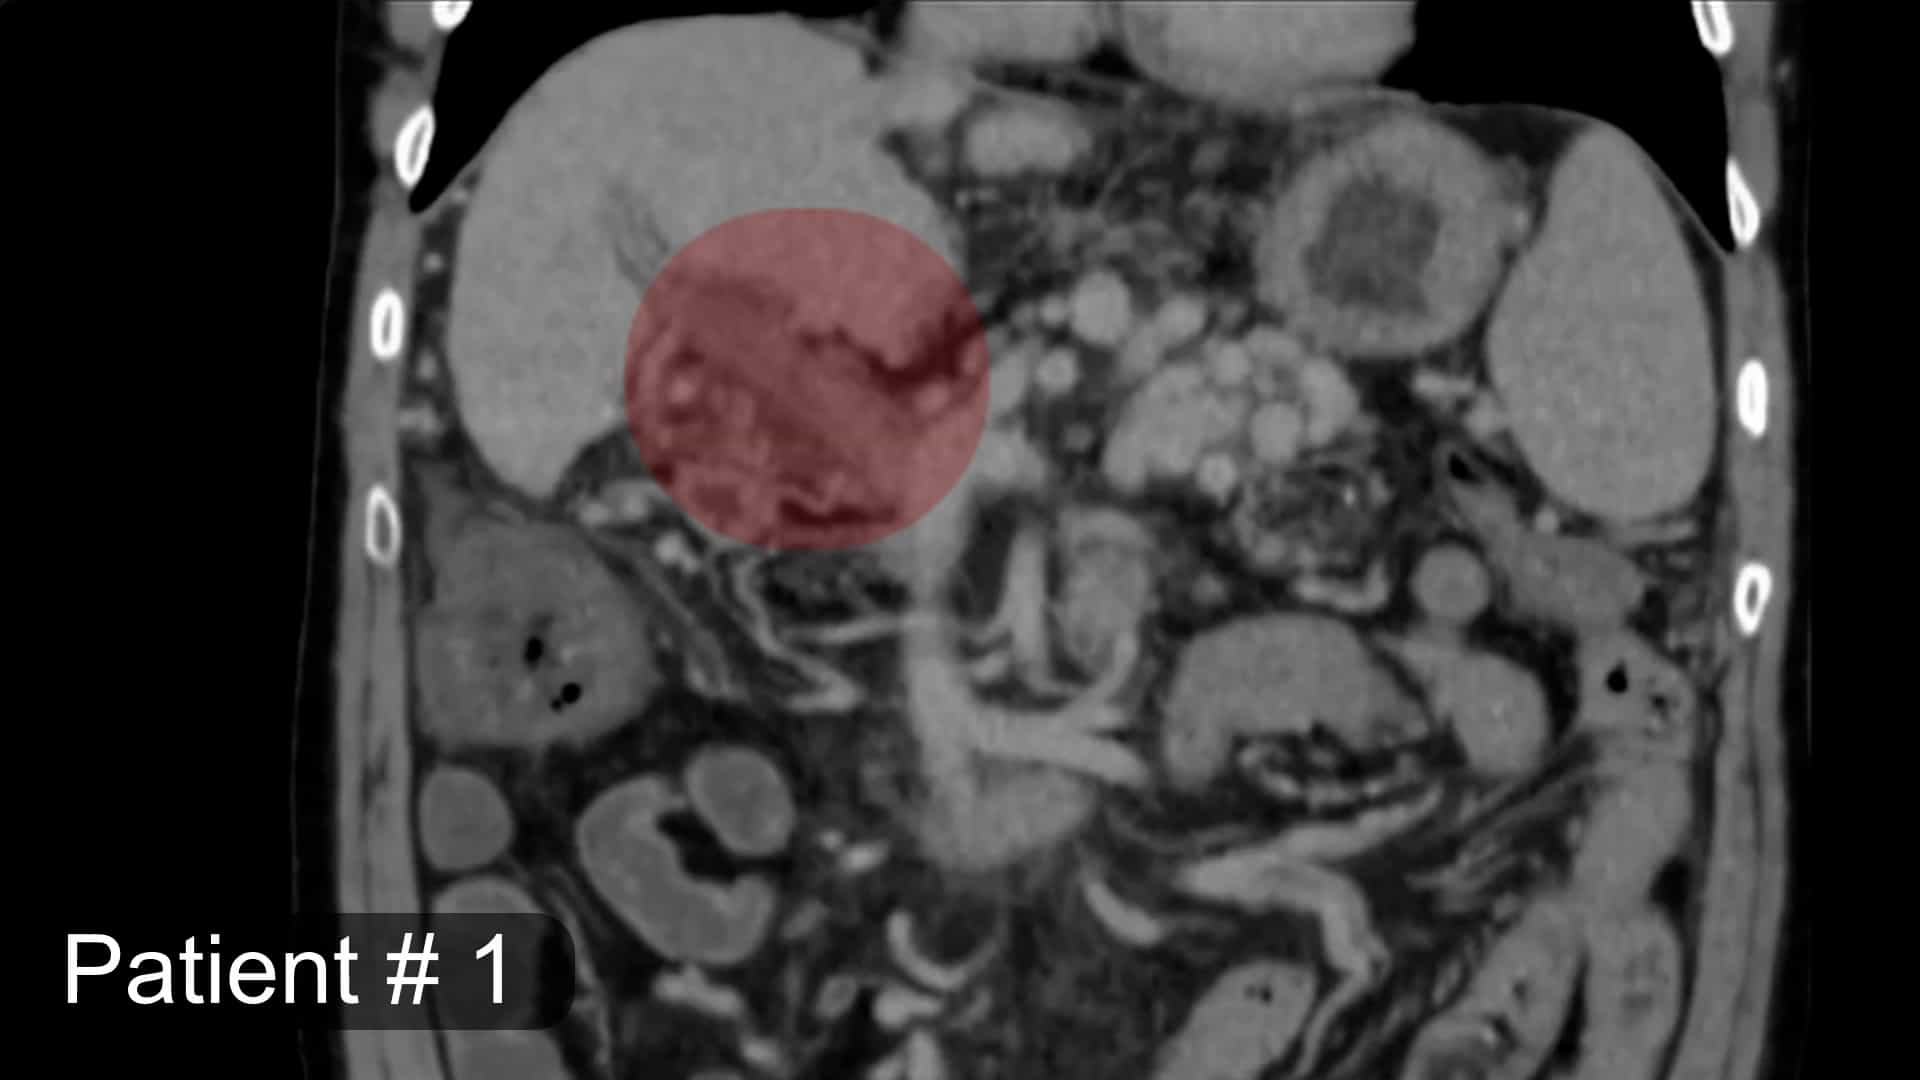
New Thrombectomy Technique for Total Portal Vein Thrombosis in Liver Transplantation
Published on: June 27, 2025
Portal vein thrombosis in cirrhotics: related with anticardiolipin antibodies?
Gürol Oksüzoglu1, Yusuf Bayraktar, Serap Arslan
1Department of Gastroenterology, Hacettepe Medical School, Ankara, Turkey. gast@bayindirtip.com.tr

Insights
Antiphospholipid antibodies, including anticardiolipin antibodies, were significantly elevated in cirrhotic patients who developed portal vein thrombosis. These findings suggest a potential role for antiphospholipid antibodies in the pathogenesis of portal vein thrombosis in cirrhosis.
Area of Science:
- Hepatology
- Immunology
- Thrombosis Research
Background:
- Cirrhosis is a significant risk factor for portal vein thrombosis (PVT).
- The role of antiphospholipid antibodies (aPL) in PVT development among cirrhotic patients remains unclear.
- This study investigates the association between specific aPL and PVT in cirrhosis.
Purpose of the Study:
- To evaluate the relationship between antiphospholipid antibodies and portal vein thrombosis in patients with cirrhosis.
- To compare aPL levels in cirrhotics with and without PVT against healthy controls.
Main Methods:
- Enrolled three groups: cirrhotics without PVT (Group I), cirrhotics with PVT (Group II), and healthy controls (Group III).
- Measured anticardiolipin IgG and IgM antibody concentrations using ELISA and lupus anticoagulant using clotting assays.
- Analyzed correlations between aPL and clinical factors in cirrhotic patients.
Main Results:
- Anticardiolipin IgG and IgM concentrations were significantly higher in cirrhotics with PVT (Group II) compared to those without PVT (Group I) and healthy controls (Group III).
- Elevated anticardiolipin IgG, IgM, or both were found in a higher percentage of patients in Group II (55.55% IgG, 72.22% IgM) versus Group I (27.27% IgG, 27.27% IgM).
- No significant correlation was found between aPL and clinical factors like prior surgery, Child groups, sex, or etiology of cirrhosis.
Conclusions:
- Anticardiolipin antibody concentrations are significantly elevated in cirrhotic patients who have developed portal vein thrombosis.
- Antiphospholipid antibodies may contribute to the development of portal vein thrombosis in the context of cirrhosis.
- Further research is warranted to elucidate the precise mechanisms linking aPL and PVT in liver disease.
Background/Aims:
To evaluate the relationship of antiphospholipid antibodies and portal vein thrombosis in cirrhotics.
Methodology:
22 cirrhotics without portal vein thrombosis (Group I), 18 with portal vein thrombosis (Group II) and 20 healthy controls (Group III) were enrolled. Anticardiolipin IgG and IgM antibody concentrations were measured by ELISA and lupus anticoagulant by clotting. Groups were compared according to sex, age, etiology of cirrhosis, prior intraabdominal surgery, Child groups, anticardiolipin IgG, IgM and lupus anticoagulant. Then for all the 40 cirrhotics (Group IV) correlation was tested between anticardiolipin IgM, IgG, lupus anticoagulant and Child groups, etiology of cirrhosis, sex and prior surgery.
Results:
In Group I, anticardiolipin IgG concentration was 15.3 (15.9) GPL)/mL and IgM was 8.6 (6.5) MPL/mL. In 6 (27.27%) anticardiolipin IgG, in 6 (27.27%) IgM and in 2 (9.09%) both were high. Lupus anticoagulant was positive in 7 (31.81%). In Group II anticardiolipin IgG concentration was 26.3 (14.7) GPL/mL and IgM was 15.1 (7.2) MPL/mL. In 10 (55.55%) anticardiolipin IgG, in 13 (72.22%) IgM and in 9 (50%) both were high. Lupus anticoagulant was positive in 5 (27.77%). In Group III lupus anticoagulant was positive in 1 (0.5%). Anticardiolipin IgG was 10.3 (5.9) GPL/mL, IgM 5 (3.6) MPL/mL anticardiolipin IgM level was high in 1 (0.5%). Group I and II were similar with respect to lupus anticoagulant, Child groups, prior intraabdominal surgery and etiology of cirrhosis. For anticardiolipin IgG and IgM there was a significant difference between Group I and II, I and III and II and III. In Group IV there was no correlation between prior abdominal surgery, Child groups, sex, etiology and anticardiolipin IgG, IgM or lupus anticoagulant.
Conclusions:
Anticardiolipin antibody concentrations were significantly higher in cirrhotics with portal vein thrombosis. Thus anticardiolipin antibodies may play a role in the development of portal vein thrombosis in cirrhosis.

Related Concept Videos
 01:22
Portal Hypertension
 01:30
Venous Thrombosis I: Introduction
 01:29
Venous Thrombosis III: Interprofessional Care
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:24
Esophageal Varices-I: Introduction
 01:24
Cirrhosis II: Pathophysiology