Related Experiment Video
Updated: Aug 30, 2026
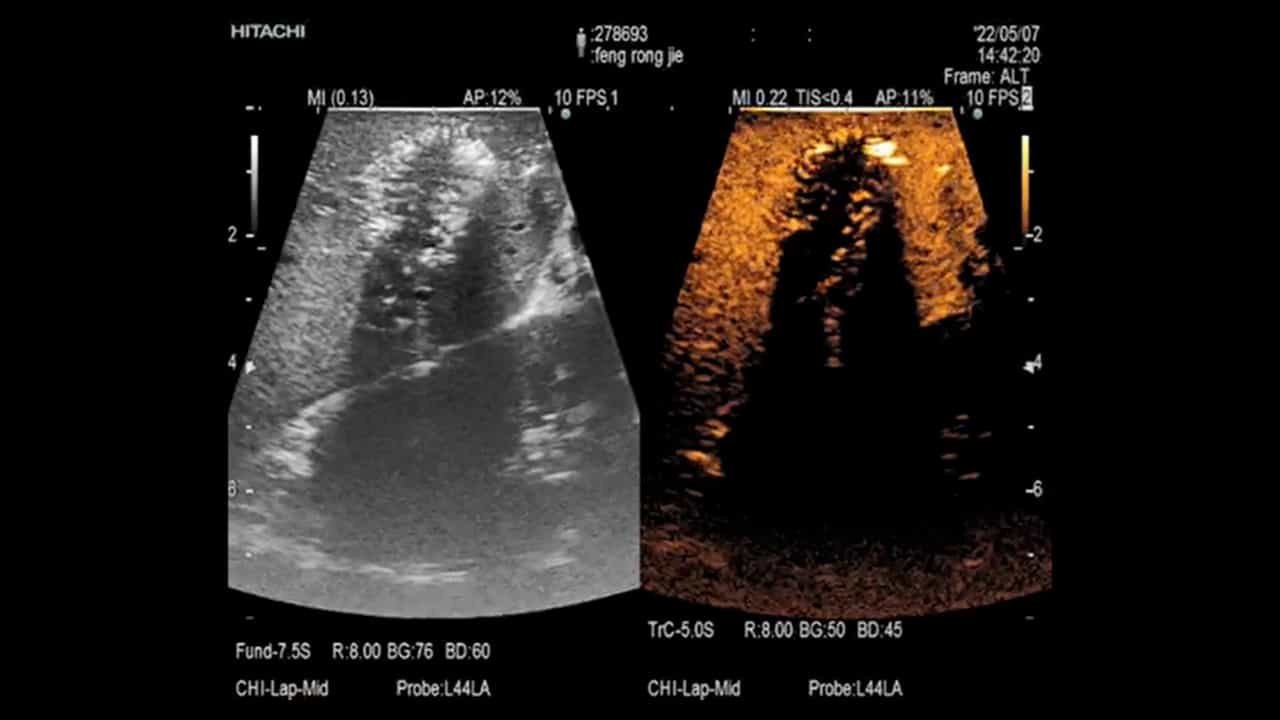
Application of Laparoscopic Hepatectomy Combined with Intraoperative Microwave Ablation in Colorectal Cancer Liver Metastasis
Published on: March 3, 2023
[Management of patients with hepatic metastases from gastric carcinoma]
Masahiro Hiratsuka1, Tokiharu Yano, Masayuki Yamamoto
1Department of Surgery, Itami Municipal Hospital, Hyogo, Japan.

Abstract:
Many studies have reported the benefit of hepatic resection for metastatic tumors from colorectal cancer. However, the significance of hepatic resection for gastric metastasis has been controversial. Peritoneal metastases were recognized in 40% of gastric cancer patients with liver metastases, and metastatic lesions in both lobes of the liver were seen in 60% of patients. Resection with curability B was performed in only 10% of the all gastric cancer patients with liver metastases. However, the overall 5-year survival rate of curability B resection was more than 30%, suggesting that it is worth while treating metastases of gastric cancer to the liver. Both synchronous and metachronous metastases are indications for hepatectomy. If there is only one liver metastasis, with no peritoneal and paraaortic lymph node metastases, curability B resection can be performed. Although there is no consensus on the method of hepatectomy, wedge resection is satisfactory. As systemic chemotherapy, S-1 + cisplatin results in a response rate of 50% in patients with metastases to the liver. As arterial infusion chemotherapy, the 5-fluorouracil-doxorubicin-mitomycin (FAM) regimen yields a response rate of more than 70% including 15% complete response rate. FAM is thus a superior regimen, but care must be taken to prevent complications resulting from intraarterial infusion of outside the vas due to deviation of the catheter.

Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...