Related Experiment Video
Updated: Aug 30, 2026
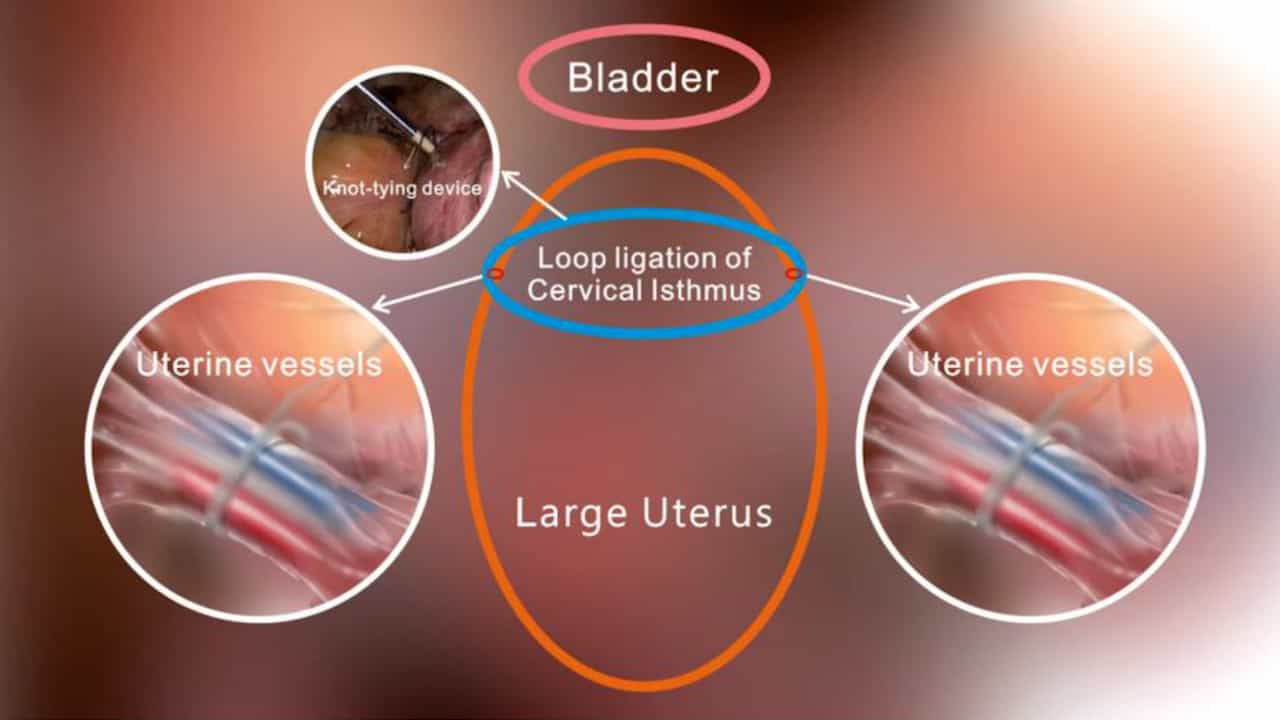

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Massive obstetric hemorrhage
1I. Department of Obstetrics and Gynecology, Semmelweis University, Budapest, Hungary.

Massive obstetric haemorrhage is a major cause of maternal death and morbidity; abruption of the placenta, placenta praevia and postpartum haemorrhage being the main causes of haemorrhages. A delay in the correction of hypovolaemia, diagnosis and treatment of defective coagulation and/or surgical control of bleeding are the avoidable factors in most maternal deaths caused by haemorrhage. The main goal is to maintain effective circulating intravascular volume by prompt and adequate replacement of blood, crystalloids or fresh-frozen plasma through more than one intravenous line (it might be necessary to pump blood under pressure) with constant monitoring of the pulse rate and the arterial blood pressure. The rapid correction of hypovolaemia with crystalloids and red cells is the first priority, followed by blood component therapy. Oxytocin and prostaglandin will correct uterine atony, and appropriate surgical intervention is required for traumatic bleeding. Ligation of the uterine arteries, ovarian arteries and hypogastric arteries will usually control uterine bleeding and arterial embolization is also effective. Hysterectomy should also be considered in severe cases. All gynecologists should be able to perform without delay the operative maneuvers which are necessary to control the bleeding, including hypogastric artery ligation, or even emergency hysterectomy. This topic may have received little attention because it is perceived as being associated with maternal morbidity rather than mortality in developed countries; it is only recently that the extent and importance of postnatal maternal morbidity has been recognized.
Massive obstetric haemorrhage is a major cause of maternal death and morbidity; abruption of the placenta, placenta praevia and postpartum haemorrhage being the main causes of haemorrhages. A delay in the correction of hypovolaemia, diagnosis and treatment of defective coagulation and/or surgical control of bleeding are the avoidable factors in most maternal deaths caused by haemorrhage. The main goal is to maintain effective circulating intravascular volume by prompt and adequate replacement of blood, crystalloids or fresh-frozen plasma through more than one intravenous line (it might be necessary to pump blood under pressure) with constant monitoring of the pulse rate and the arterial blood pressure. The rapid correction of hypovolaemia with crystalloids and red cells is the first priority, followed by blood component therapy. Oxytocin and prostaglandin will correct uterine atony, and appropriate surgical intervention is required for traumatic bleeding. Ligation of the uterine arteries, ovarian arteries and hypogastric arteries will usually control uterine bleeding and arterial embolization is also effective. Hysterectomy should also be considered in severe cases. All gynecologists should be able to perform without delay the operative maneuvers which are necessary to control the bleeding, including hypogastric artery ligation, or even emergency hysterectomy. This topic may have received little attention because it is perceived as being associated with maternal morbidity rather than mortality in developed countries; it is only recently that the extent and importance of postnatal maternal morbidity has been recognized.
Related Concept Videos
 01:07
Intestinal Obstruction II: Pathophysiology
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:17
Hemorrhagic Stroke l: Introduction
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...