Related Experiment Video
Updated: Aug 30, 2026


Cardiac Stress Test Induced by Dobutamine and Monitored by Cardiac Catheterization in Mice
Published on: February 10, 2013
Effects of intravenous dobutamine on coronary vasomotion in humans
Emanuele Barbato1, Jozef Bartunek, Eric Wyffels
1Cardiovascular Center, OLV Ziekenhuis, Aalst, Belgium.

Objectives:
We sought to investigate the vascular mechanisms of dobutamine-induced myocardial ischemia.
Background:
Dobutamine stress is often used as a surrogate for exercise. The effects of dobutamine on the epicardial arteries are incompletely understood and possibly different from those of physical exercise.
Methods:
Intravenous (IV) dobutamine (40 microg/kg per min) was administered in 19 patients with normal, 23 patients with mildly atherosclerotic, and 12 patients with stenotic coronary arteries. In another two groups of patients with stenotic arteries, IV dobutamine was preceded by 1) an intracoronary (IC) bolus of the alpha-adrenergic blocker phentolamine (12 microg/kg, n = 12); and 2) an IC infusion of the nitric oxide substrate L-arginine (150 micromol/l per min for 20 min, n = 11). Intravenous saline instead of dobutamine was infused into eight patients with normal arteries. After dobutamine (or saline), an IC bolus of isosorbide dinitrate (ISDN, 0.2 mg) was given. Coronary vasomotion was evaluated by quantitative coronary angiography on angiograms obtained after each dose of dobutamine, saline, phentolamine, L-arginine, and ISDN.
Results:
Dobutamine increased the rate-pressure product and heart rate similarly in all patients except those who received saline. Dobutamine induced vasodilation in normal (change in luminal diameter [DeltaLD] vs. baseline: 19 +/- 2%) and in mildly atherosclerotic arteries (DeltaLD: 8 +/- 2%, p < 0.05 vs. normal). In stenotic arteries, dobutamine did not induce significant vasomotion (DeltaLD: -3 +/- 3%); the latter was improved by L-arginine (DeltaLD: 10 +/- 3%, p < 0.05 vs. stenotic arteries) and fully restored by phentolamine (DeltaLD: 19 +/- 3%, p < 0.05 vs. stenotic arteries).
Conclusions:
Endothelial dysfunction and enhanced alpha-adrenergic tone contribute to the loss of dobutamine-induced vasodilation in coronary atherosclerosis. In contrast to physical exercise, dobutamine does not induce "paradoxical vasoconstriction" of atherosclerotic coronary arteries.

Related Concept Videos
 01:29
Pathophysiology of Cardiac Performance
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
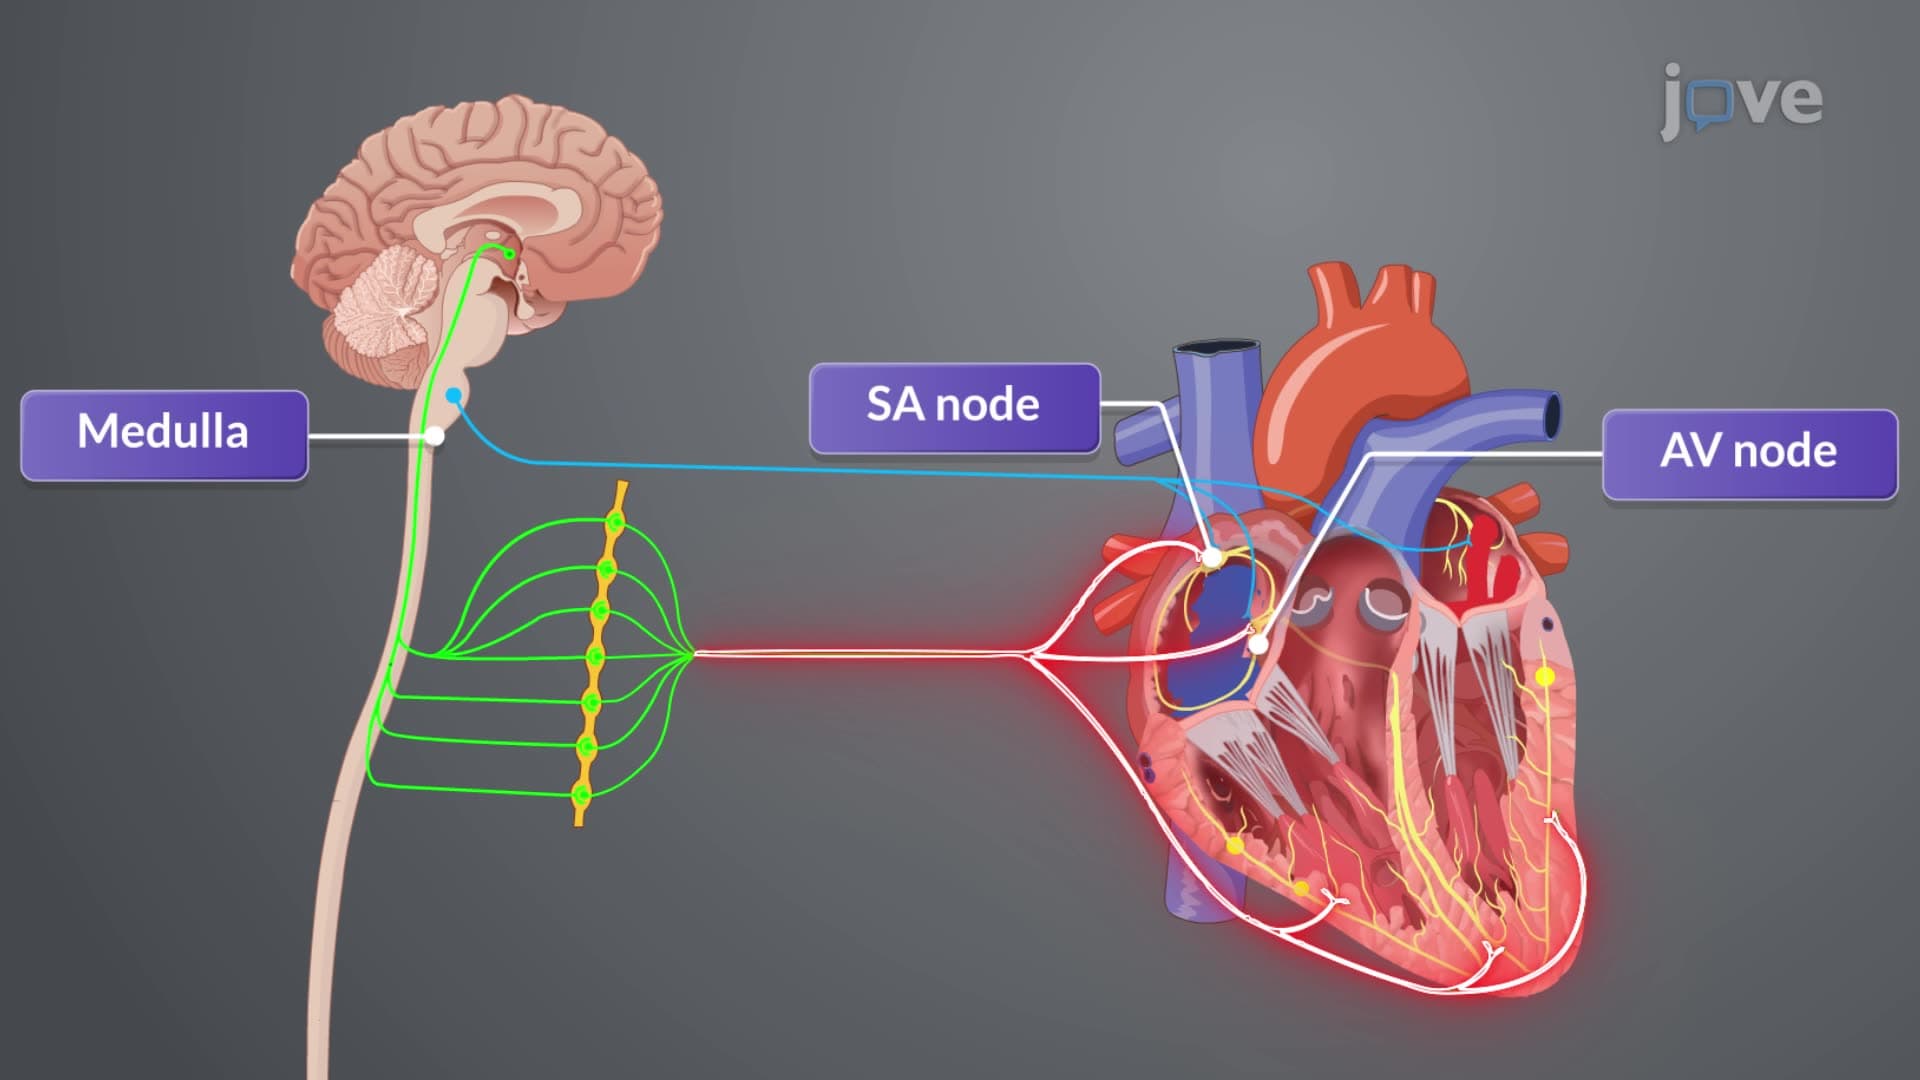
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart rate...
 01:30
Acute Coronary Syndrome III: Diagnostic Studies