Related Experiment Video
Updated: Aug 23, 2026
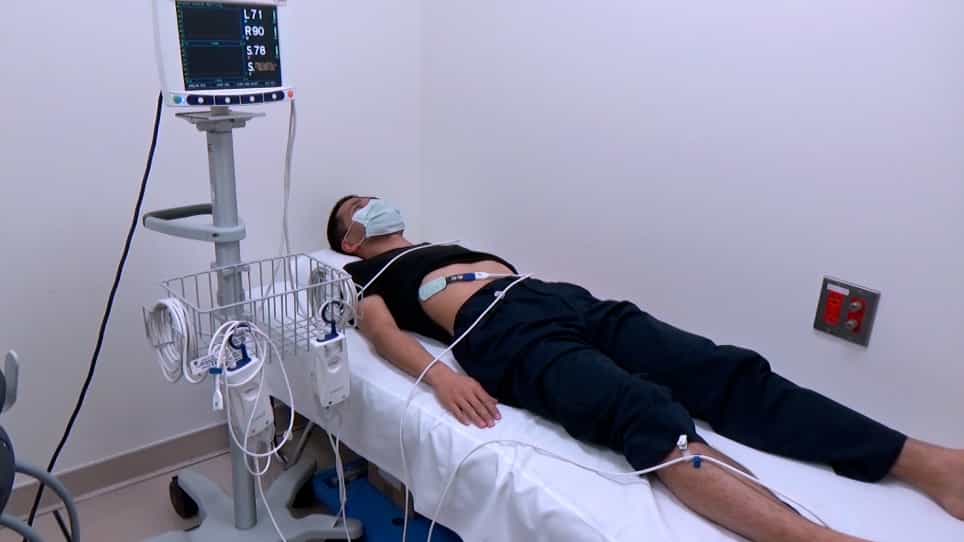

Measurement of Tissue Oxygenation Using Near-Infrared Spectroscopy in Patients Undergoing Hemodialysis
Published on: October 2, 2020
Dialysis adequacy and response to erythropoietic agents: what is the evidence base?
Francesco Locatelli1, Lucia Del Vecchio
1Department of Nephrology and Dialysis, Ospedale A. Manzoni, Lecco, Italy. nefrologia@ospedale.lecco.it

Anaemia secondary to chronic kidney disease is a complex syndrome. Adequate dialysis can contribute to its correction by removing small, and possibly middle/large molecules, that may inhibit erythropoiesis. A clear relationship between higher haemoglobin or haematocrit levels, lower recombinant human erythropoietin (epoetin) dose and increase in dialysis dose has been reported in a number of prospective and retrospective studies. This is particularly true in patients receiving inadequate dialysis. Increased attention has also been paid to the relationship between dialysis, increased inflammatory stimulus and response to erythropoietic therapy, as dialysate contamination and low-compatible treatments may increase the production of cytokines and consequently inhibit erythropoiesis. As middle-/large-molecular-weight inhibitors can only be adsorbed or removed by more permeable membranes, the biocompatibility of dialysis membranes and flux are also important factors. In highly selected, adequately dialysed patients without iron or vitamin depletion, however, the effect of these treatment modalities on anaemia appears to be smaller than expected. The role of on-line treatments is still controversial; moreover, it is still difficult to discriminate between the effects of on-line haemodiafiltration per se (use of high-flux biocompatible membranes and pyrogen-free dialysate) from that of an increased dialysis dose. Prospective, randomized, adequately sized studies on this topic are still needed. Results, albeit very preliminary, obtained with short or long nocturnal daily haemodialysis on anaemia correction are encouraging. Adequate dialysis is not only a tool for reducing morbidity and mortality of haemodialysis patients, but is also a way of optimizing responsiveness to erythropoietic therapy, allowing easier achievement of anaemia correction in a higher percentage of patients.
Anaemia secondary to chronic kidney disease is a complex syndrome. Adequate dialysis can contribute to its correction by removing small, and possibly middle/large molecules, that may inhibit erythropoiesis. A clear relationship between higher haemoglobin or haematocrit levels, lower recombinant human erythropoietin (epoetin) dose and increase in dialysis dose has been reported in a number of prospective and retrospective studies. This is particularly true in patients receiving inadequate dialysis. Increased attention has also been paid to the relationship between dialysis, increased inflammatory stimulus and response to erythropoietic therapy, as dialysate contamination and low-compatible treatments may increase the production of cytokines and consequently inhibit erythropoiesis. As middle-/large-molecular-weight inhibitors can only be adsorbed or removed by more permeable membranes, the biocompatibility of dialysis membranes and flux are also important factors. In highly selected, adequately dialysed patients without iron or vitamin depletion, however, the effect of these treatment modalities on anaemia appears to be smaller than expected. The role of on-line treatments is still controversial; moreover, it is still difficult to discriminate between the effects of on-line haemodiafiltration per se (use of high-flux biocompatible membranes and pyrogen-free dialysate) from that of an increased dialysis dose. Prospective, randomized, adequately sized studies on this topic are still needed. Results, albeit very preliminary, obtained with short or long nocturnal daily haemodialysis on anaemia correction are encouraging. Adequate dialysis is not only a tool for reducing morbidity and mortality of haemodialysis patients, but is also a way of optimizing responsiveness to erythropoietic therapy, allowing easier achievement of anaemia correction in a higher percentage of patients.


Related Concept Videos
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:25
Hemodialysis I: Introduction
 01:25
Hemodialysis III: Nursing Management
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:28
Chronic Kidney Disease III: Interprofessional Care