Related Experiment Video
Updated: Aug 30, 2026
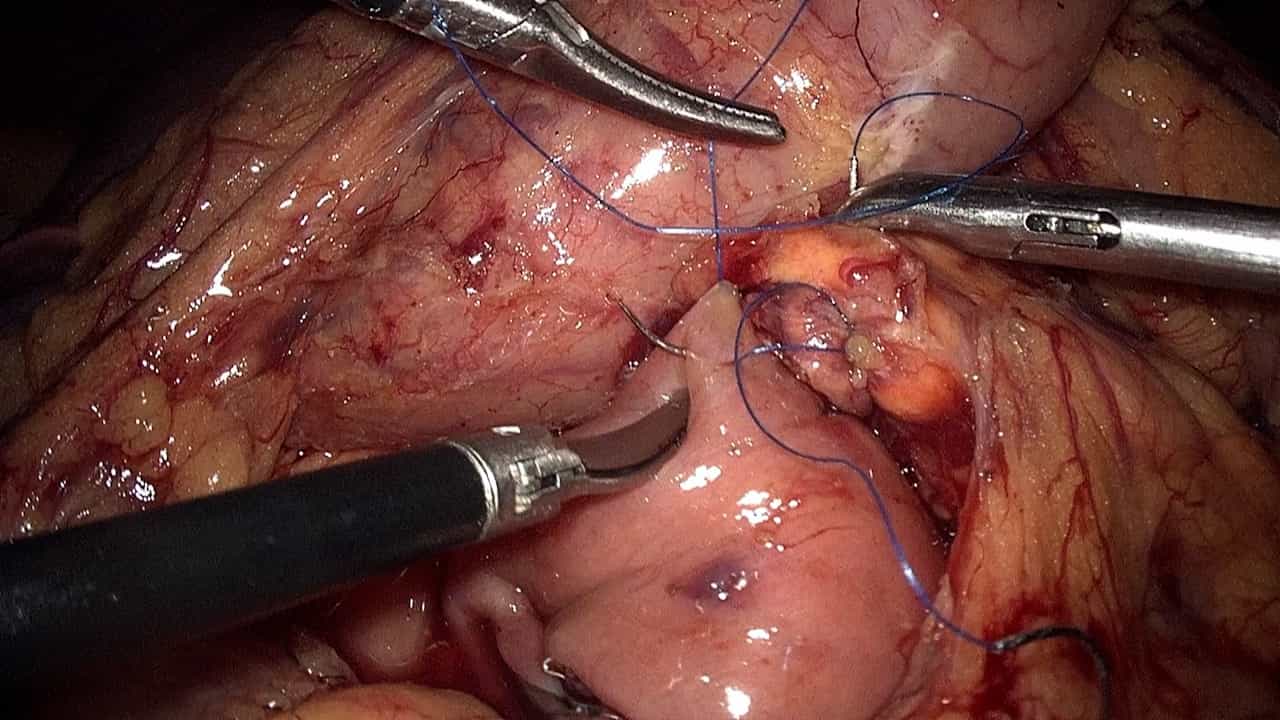

Laparoscopic Duodenum-Preserving Pancreatic Head Resection via Inferior Infracolic Approach: A Surgical Approach for Benign Lesions
Published on: February 9, 2024
[Massive hemorrhage from a pancreatic pseudocyst into the duodenum]

Insights
Bleeding from pancreatic pseudocysts due to chronic pancreatitis can be fatal. This case report details a massive bleed from the gastroduodenal artery, requiring urgent surgery and highlighting diagnostic and therapeutic challenges.
Area of Science:
- Gastroenterology
- Vascular Surgery
- Radiology
Background:
- Chronic pancreatitis frequently leads to pancreatic pseudocysts and pseudoaneurysms.
- Hemorrhage from these lesions carries a high mortality rate, especially with conservative management.
- Current diagnostics include angiography and contrast-enhanced CT, with therapy often involving percutaneous transvascular embolization (PTE) or surgery.
Observation:
- A 44-year-old patient with chronic pancreatitis presented with massive bleeding from a pancreatic pseudocyst eroding the gastroduodenal artery.
- Spontaneous pseudocyst perforation into the duodenum resulted in hemorrhagic shock, necessitating emergency surgical intervention.
- The bleeding vessel was identified via longitudinal gastroduodenotomy and pseudocyst dissection through the duodenal wall.
Findings:
- Successful identification and management of a bleeding gastroduodenal artery pseudoaneurysm within a pancreatic pseudocyst.
- Demonstration of a rare complication of chronic pancreatitis: spontaneous pseudocyst perforation causing massive gastrointestinal hemorrhage.
- Surgical approach via gastroduodenotomy allowed direct visualization and control of the bleeding source.
Implications:
- Highlights the critical need for prompt diagnosis and aggressive management of bleeding pancreatic pseudocysts.
- Underscores the limitations of conservative treatment and the potential role of surgical intervention in life-threatening hemorrhage.
- Emphasizes the importance of considering surgical options in complex cases refractory to endovascular techniques.
Abstract:
Pancreatic pseudocyst or pseudoaneurysm bleeding related to chronic pancreatitis is associated with high mortality. Diagnostics includes angiography and contrast CT; therapy is based mainly on percutaneous transvascular embolisation (PTE) and surgery. Mortality burden related to conservative approach is up to 90%. Case report describes massive pancreas pseudocyst bleeding from erosion-affected arteria gastroduodenalis in 44-years-old patient with chronic pancreatitis. Spontaneous pseudocyst perforation into the duodenum caused hemorrhagic shock with necessity of urgent surgery. Identification of bleeding vessel was enabled thanks to longitudinal gastroduodenotomy and pseudocyst dissection through duodenum wall. Article reminds some diagnostics and therapeutics issues related to chronic pancreatitis complications with bleeding as well as information published in recent literature.
Related Concept Videos
 01:21
Acute Pancreatitis II: Pathophysiology
 01:25
Acute Pancreatitis I: Introduction
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:07
Intestinal Obstruction II: Pathophysiology