Related Experiment Video
Updated: Aug 30, 2026

Investigation into Deep Breathing through Measurement of Ventilatory Parameters and Observation of Breathing Patterns
Published on: September 16, 2019
Survey of patients whose lungs could not be ventilated and whose trachea could not be intubated in university
Takumi Nagaro1, Toshihiro Yorozuya, Masao Sotani
1Department of Anesthesiology and Resuscitology, Ehime University School of Medicine, Shigenobu, Onsen-gun, Ehime 791-0295, Japan.

Purpose:
We conducted a survey to clarify the actual circumstances in which the lungs could not be ventilated and the trachea could not be intubated (CVCI).
Methods:
A questionnaire was mailed to all the university hospitals in Japan, asking about CVCI they had experienced during induction of anesthesia in 1998, and before 1997.
Results:
Answers were obtained from 60 of 83 institutes. CVCI occurred in 26 of 151 900 cases of general anesthesia (0.017%) in 1998. Eighteen cases occurred after induction of anesthesia by several induction methods. Five cases occurred after repeated attempts at tracheal intubation by laryngoscopy and fiberscopy in patients under awake or anesthetized conditions. In the remaining 3 cases, the situation of occurrence was not documented. Patients with CVCI had anatomical abnormalities around the upper airways, mostly from acquired diseases. CVCIs after induction of anesthesia were successfully treated by restoration of spontaneous respiration, blind intubation, laryngeal mask airway, and transtracheal approaches, and CVCIs after repeated attempts at intubation were treated mostly by transtracheal approaches. No serious consequences occurred in any patients in 1998. Twenty cases were reported before 1997, and 2 were specific, in which CVCI followed malplacement of a tracheal tube, and serious consequences, death and brain damage, respectively, followed. In other patients, no serious consequences occurred, although cardiac arrest occurred in 1 patient.
Conclusion:
This survey demonstrates that CVCI can occur in any situation in which the airway is not established. Furthermore, effective treatments may be different depending on the situation, and delayed recognition of tracheal tube misplacement may lead to a serious outcome.

Related Concept Videos
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like asthma or COPD,...
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...
 01:23
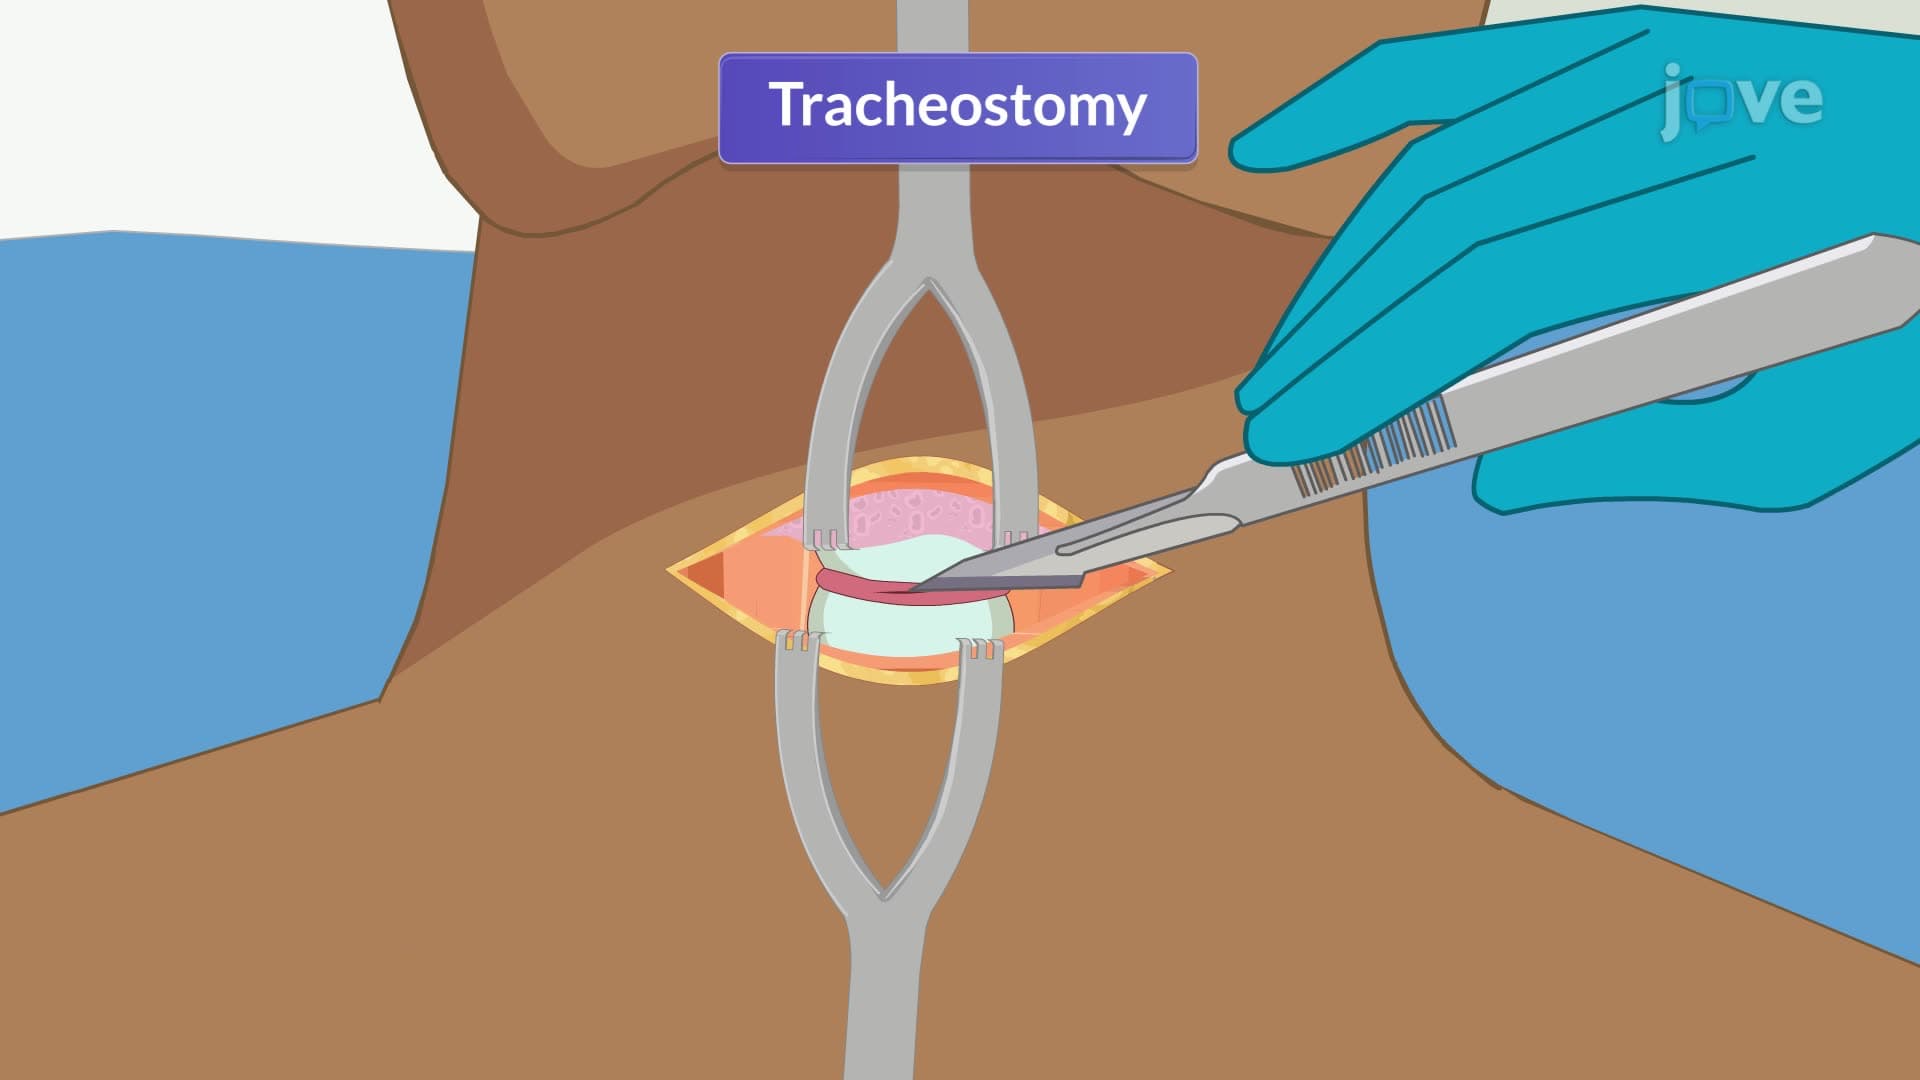
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...