Related Experiment Video
Updated: Aug 30, 2026


Modeling Ascending Vaginal Infection, Preterm Birth, and Neonatal Morbidity in Mice
Published on: October 10, 2025
Young maternal age and preterm birth
Antônio A M da Silva1, Vanda M F Simões, Marco A Barbieri
1Department of Public Health, University of Maranhão, and Department of Paediatrics, Faculty of Medicine of Ribeirão Preto, University of São Paulo, Brazil. aasilva@elo.com.br

The association between young maternal age and preterm birth (PTB) remains controversial. In some studies the association disappeared after controlling for socio-economic and reproductive factors, thus indicating that social disadvantage rather than biological factors may be the explanation. However, in other studies the association persisted after adjustment. The relation between young maternal age and PTB was studied in a city located in Brazil, an underdeveloped country, where the prevalence of teenage pregnancy was high, 29%. A systematic sampling of 2541 hospital births, stratified by hospital, was performed in São Luís, Northeast Brazil, from March 1997 to February 1998. The risks of PTB for infants born to two groups of young mothers (<18 and 18-19 years) were calculated with and without adjustment for confounding factors (family income, marital status, mode of delivery, parity, health insurance, and short maternal stature) in a logistic regression model, using mothers 25-29 years of age as the reference group. In the unadjusted analysis, the risk of PTB was higher for mothers < 18 years [odds ratio (OR) = 2.42, 95% confidence interval (CI) 1.64, 3.57]. Those aged 18 or 19 years were not at a higher risk of PTB (OR = 0.89, 95% CI 0.58, 1.38). After adjustment, the risk of PTB for mothers < 18 years was lower but remained significant after controlling for confounding (OR = 1.70, 95% CI 1.11, 2.60). After performing a stratified analysis according to parity, the risk of PTB among very young primiparae (<18 years) remained significant (OR = 1.77, 95% CI 1.02, 3.08), whereas the risk among non-primiparous adolescents was not significantly higher than the risk among mothers in the reference group. This suggests that the association between young maternal age and PTB may have a biological basis or an artifactual explanation (errors in gestational age estimation may be more common among very young mothers) or may be due to residual confounding.
The association between young maternal age and preterm birth (PTB) remains controversial. In some studies the association disappeared after controlling for socio-economic and reproductive factors, thus indicating that social disadvantage rather than biological factors may be the explanation. However, in other studies the association persisted after adjustment. The relation between young maternal age and PTB was studied in a city located in Brazil, an underdeveloped country, where the prevalence of teenage pregnancy was high, 29%. A systematic sampling of 2541 hospital births, stratified by hospital, was performed in São Luís, Northeast Brazil, from March 1997 to February 1998. The risks of PTB for infants born to two groups of young mothers (<18 and 18-19 years) were calculated with and without adjustment for confounding factors (family income, marital status, mode of delivery, parity, health insurance, and short maternal stature) in a logistic regression model, using mothers 25-29 years of age as the reference group. In the unadjusted analysis, the risk of PTB was higher for mothers < 18 years [odds ratio (OR) = 2.42, 95% confidence interval (CI) 1.64, 3.57]. Those aged 18 or 19 years were not at a higher risk of PTB (OR = 0.89, 95% CI 0.58, 1.38). After adjustment, the risk of PTB for mothers < 18 years was lower but remained significant after controlling for confounding (OR = 1.70, 95% CI 1.11, 2.60). After performing a stratified analysis according to parity, the risk of PTB among very young primiparae (<18 years) remained significant (OR = 1.77, 95% CI 1.02, 3.08), whereas the risk among non-primiparous adolescents was not significantly higher than the risk among mothers in the reference group. This suggests that the association between young maternal age and PTB may have a biological basis or an artifactual explanation (errors in gestational age estimation may be more common among very young mothers) or may be due to residual confounding.

Related Concept Videos
 02:57
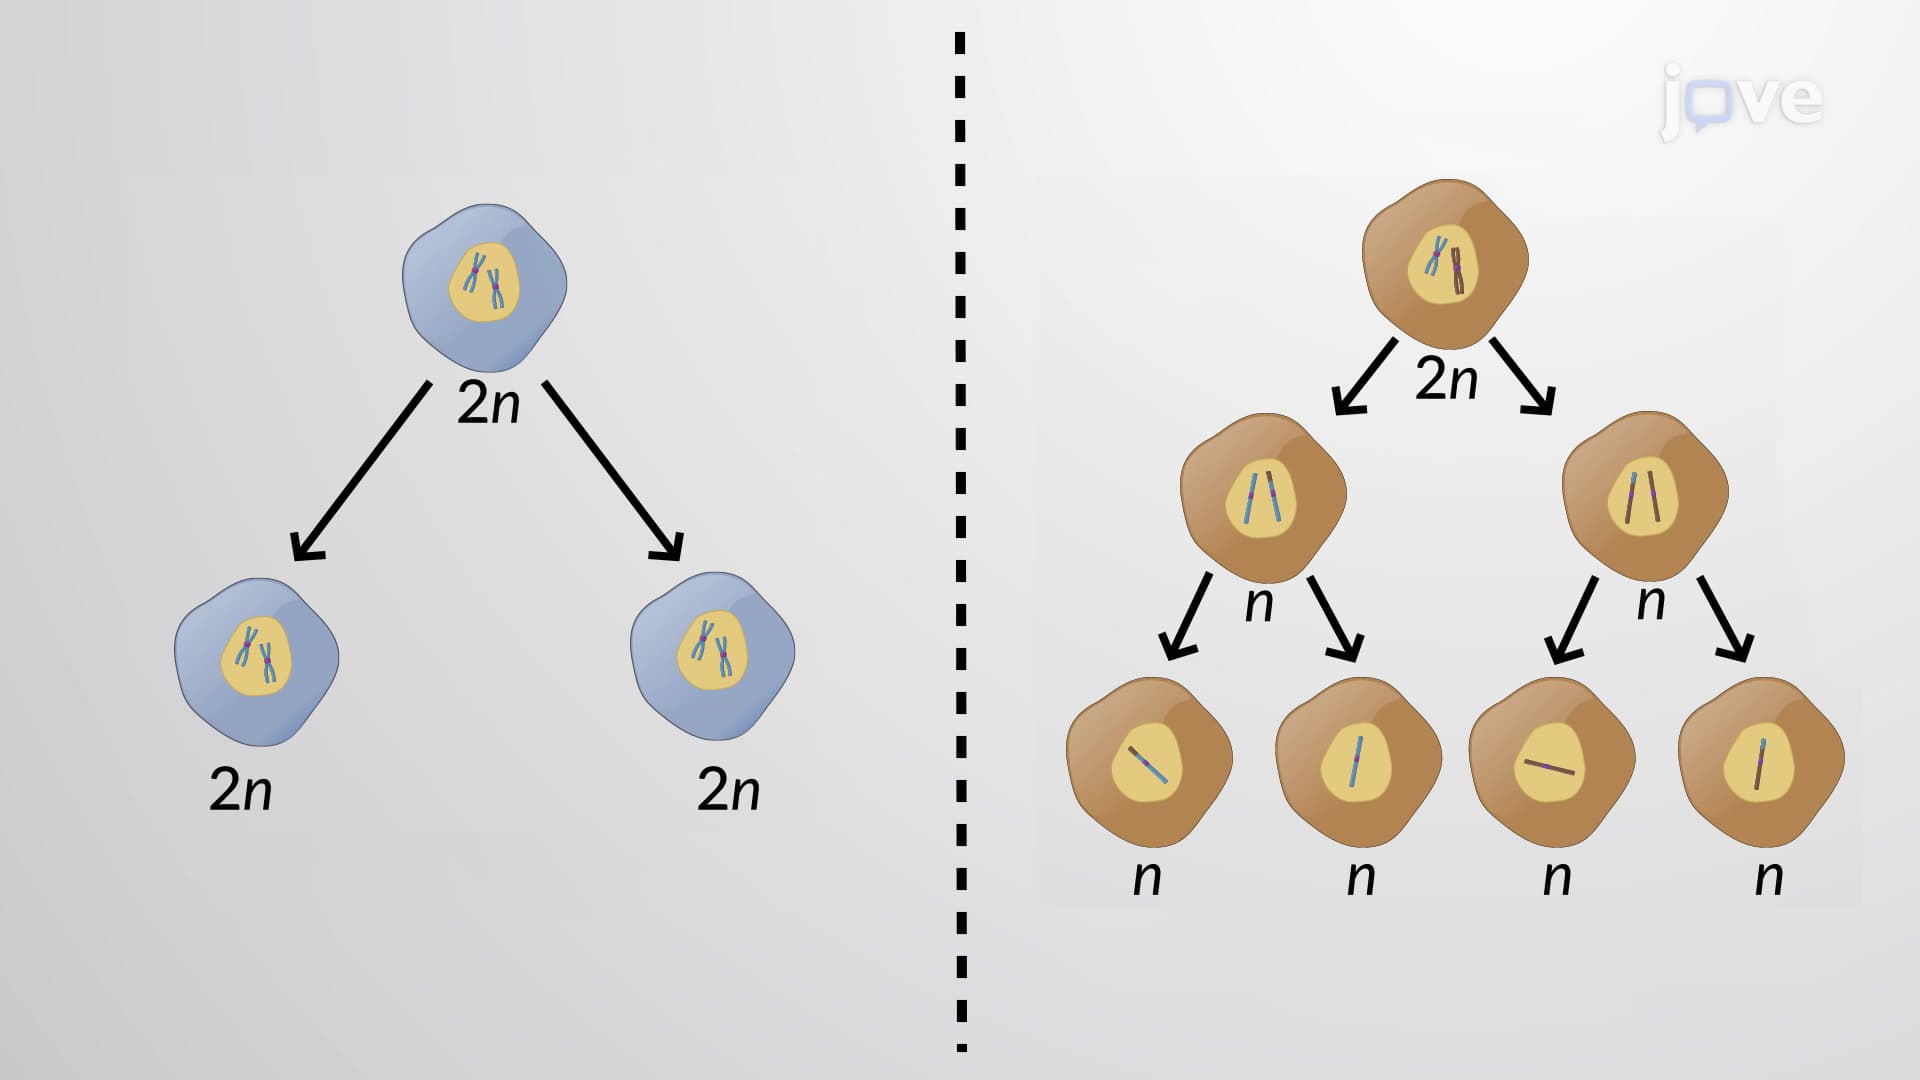
Meiosis vs. Mitosis
Before the start of mitosis and meiosis I, the cell synthesizes DNA, resulting in two homologous copies of each chromosome. DNA synthesis is...
 01:28
Development of the Oral Microbiota
 02:07
Oogenesis
 01:19
Mitral Valve Prolapse III: Nursing Management
 01:21
Nondisjunction
 01:22
Diabetes Mellitus: Type 2 and Gestational