Related Experiment Video
Updated: Aug 8, 2026

A Method for Mouse Pancreatic Islet Isolation and Intracellular cAMP Determination
Published on: June 25, 2014
Proinsulin serum concentrations in women with polycystic ovary syndrome: a marker of beta-cell dysfunction?
M Maliqueo1, I Atwater, R Lahsen
1Department of Medicine, San Juan de Dios Hospital, School of Medicine, University of Chile, Santiago, Chile.

Background:
The aim of this study was to establish the effect of polycystic ovary syndrome (PCOS) adjusted for adiposity on proinsulin concentrations.
Methods:
Ninety-one women with PCOS and 72 normal cycling (NC) women were recruited. A 2 h, 75 g oral glucose tolerance test was performed. Glucose and insulin were measured in each sample. Proinsulin and C-peptide were determined at 0 and 30 min and the fasting proinsulin/insulin ratio (PI/I) was calculated. Insulin sensitivity was estimated by insulin sensitivity index (ISI) composite, and beta-cell function was estimated by insulinogenic index.
Results:
Insulin, proinsulin and C-peptide concentrations were higher in women with PCOS than in NC women (P < 0.05). PI/I and insulinogenic index were similar in both groups. Proinsulin concentrations increased with body mass index (P < 0.05) only in women with PCOS; therefore, proinsulin concentrations were higher in obese PCOS patients compared with obese control women (P < 0.05). Moreover, a positive association between proinsulin concentrations and waist diameter adjusted for C-peptide (P < 0.05) and a negative association between proinsulin concentrations and ISI composite values were observed in PCOS patients (P < 0.05).
Conclusions:
Data suggest that in PCOS patients an elevated proinsulin concentration could reflect insulin resistance more than beta-cell dysfunction. However, the elevated concentration of proinsulin in these patients could also result from impaired beta-cell function resulting from intra-abdominal obesity independently of insulin resistance.


Related Concept Videos
 01:05
Insulin Secretory Vesicles
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
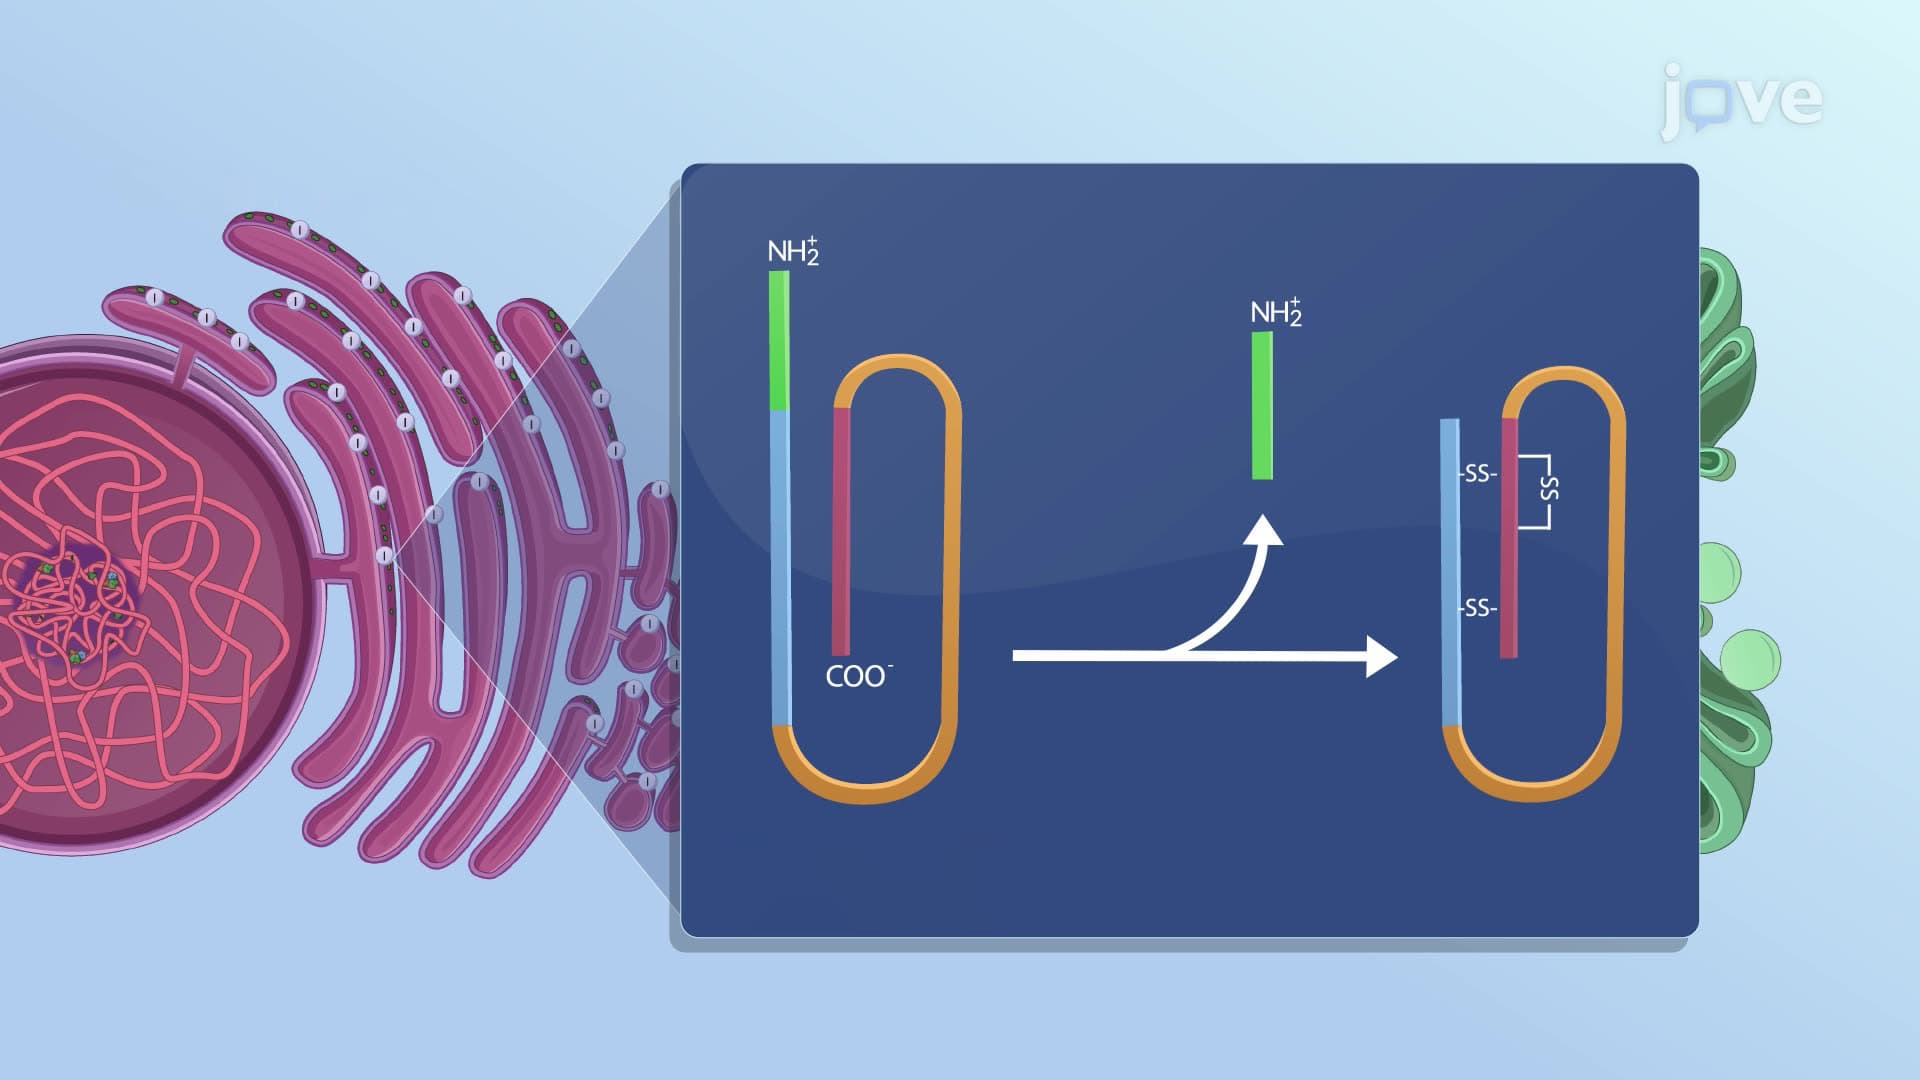
Insulin and C-peptide are co-secreted in...
 01:25
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
 01:19
Type I Diabetes III: Clinical Manifestations
 01:24
Type II Diabetes II: Pathophysiology
 01:25
Type II Diabetes Mellitus III: Clinical Manifestations and Diagnosis