Related Experiment Video
Updated: Aug 30, 2026


Rating L-DOPA-Induced Dyskinesias in the Unilaterally 6-OHDA-Lesioned Rat Model of Parkinson's Disease
Published on: October 4, 2021
Pharmacokinetics of etilevodopa compared to levodopa in patients with Parkinson's disease: an open-label, randomized,
Ruth Djaldetti1, Nir Giladi, Sharon Hassin-Baer
1Department of Neurology, Rabin Medical Center, Beilinson Campus, Petah Tiqva 49100, Israel. ruthdjal@clalit.org.il

Abstract:
"Dose failures" and "delayed on" phenomena following an intake of levodopa dose in patients with Parkinson's disease (PD) with motor fluctuations may be caused by stagnation of poorly soluble levodopa in the atonic stomach. Etilevodopa is a unique, highly soluble prodrug of levodopa. When ingested, etilevodopa is more readily dissolved in the stomach than levodopa. It passes unchanged through the stomach to the duodenum, where it is rapidly hydrolyzed by local esterases and rapidly absorbed as levodopa. To compare the pharmacokinetics of three different modes of etilevodopa/carbidopa administration with standard levodopa/carbidopa tablets in fluctuating PD patients, 29 patients with PD and response fluctuations were enrolled in an open-label, randomized, four-way crossover study of single doses of 4 treatments: swallowed etilevodopa/carbidopa tablets, etilevodopa/carbidopa tablets dissolved in water, etilevodopa oral solution with carbidopa tablets, and standard levodopa/carbidopa tablets. To measure the maximal concentration (Cmax), time to Cmax (tmax), and area under the curve (AUC) of plasma levodopa, etilevodopa, and carbidopa, blood samples were drawn before drug administration and at intervals up to 240 minutes thereafter. Plasma levodopa tmax was significantly shorter with all three modes of administration of etilevodopa (mean of about 30 minutes) than with levodopa treatment (mean of 54 minutes). During the first 45 minutes after drug ingestion, plasma levodopa AUC was significantly greater after etilevodopa administration than after levodopa administration. Levodopa AUC for 0 to 1 hour and 0 to 2 hours were also significantly greater following administration of etilevodopa/carbidopa swallowed tablets than following administration of levodopa/carbidopa tablets. Mean levodopa Cmax was in the range 2.3 to 2.7 microg/mL for all treatments. Levodopa Cmax was significantly greater following treatment with etilevodopa swallowed tablets than with levodopa tablets. Etilevodopa/carbidopa was well tolerated, with a safety profile comparable to that of levodopa/carbidopa. The shorter levodopa tmax observed with etilevodopa potentially translates to a shorter time to "on". Clinical trials with etilevodopa/carbidopa tablets should be carried out in PD patients with response fluctuations such as "delayed on" and "dose failures".

Related Concept Videos
 01:24
Parkinson's Disease: Treatment
Parkinson's Disease is primarily a result of the loss of dopaminergic neurons in the substantia nigra pars compacta. The cornerstone of its...
 01:15
Bioavailability Study Design: Healthy Subjects Versus Patients
 01:11
Bioavailability Study Design: Single Versus Multiple Dose Studies
 01:14
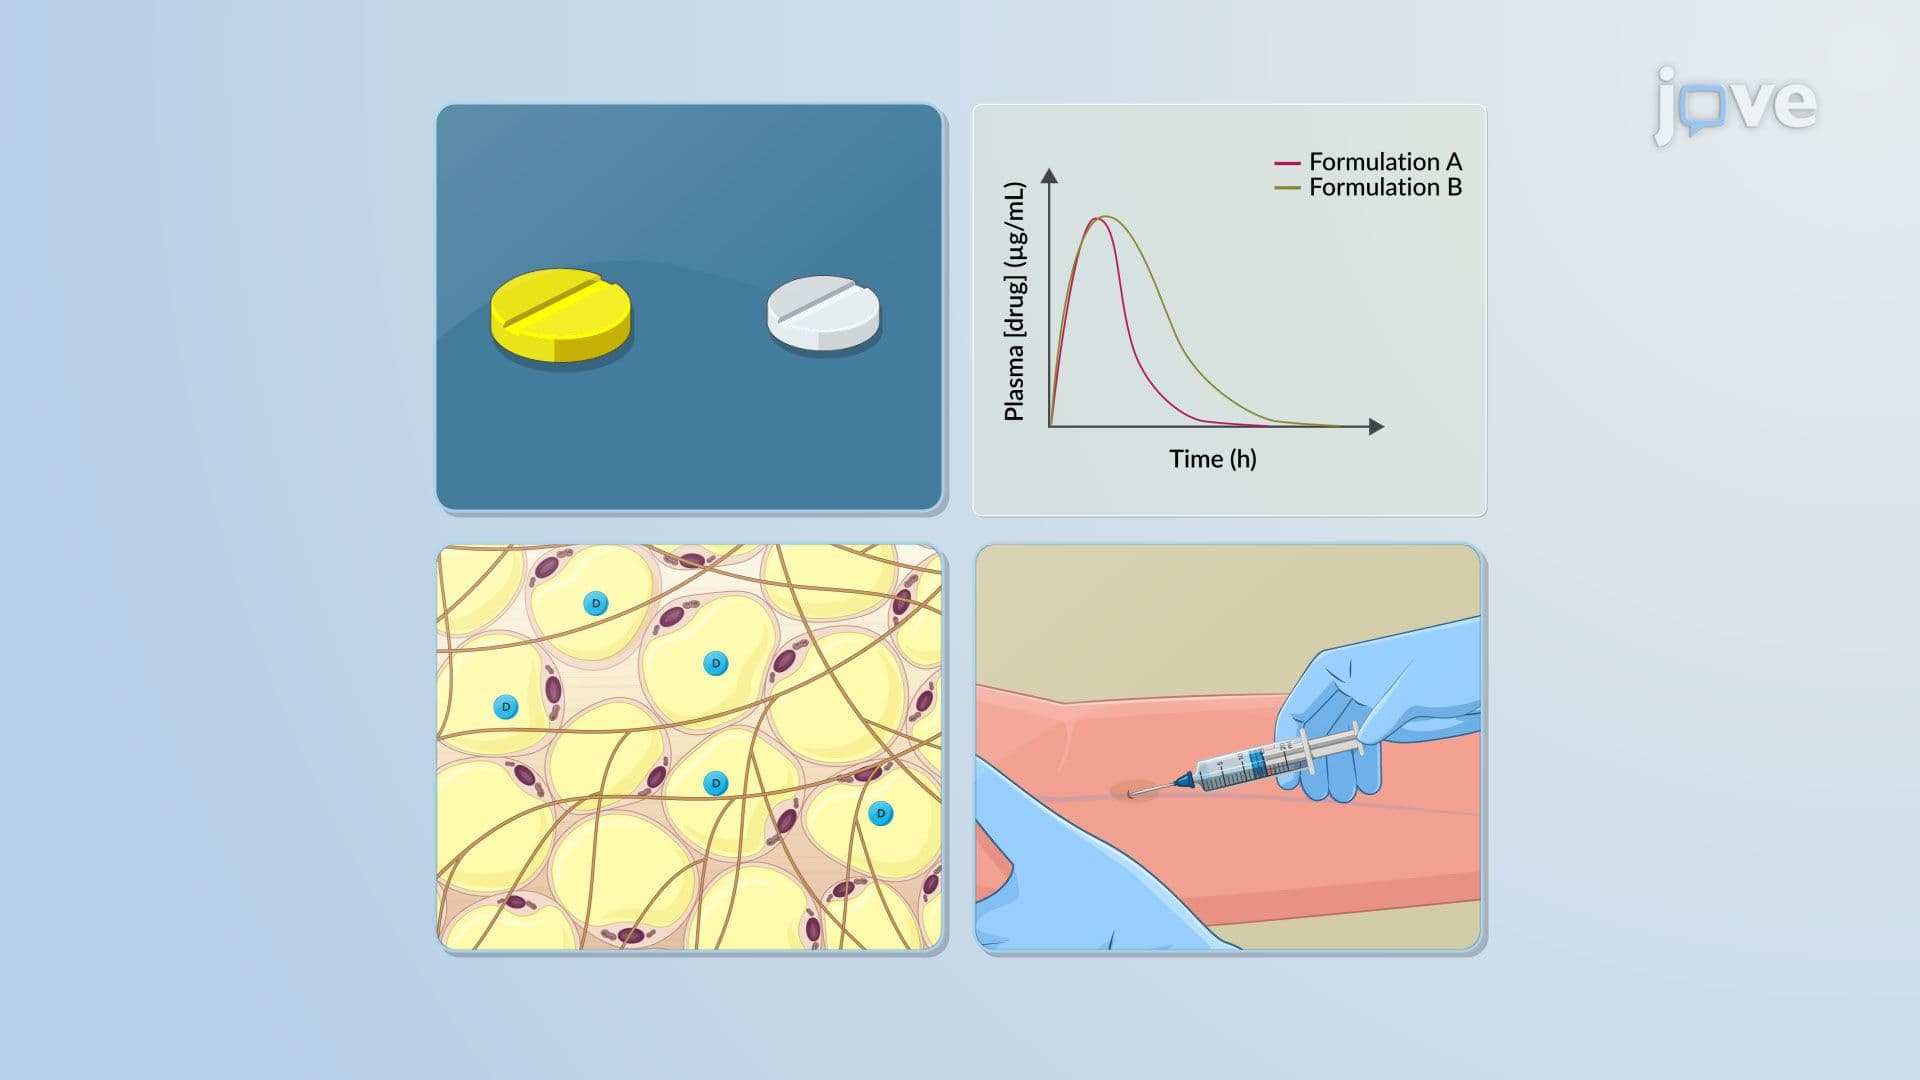
Pharmacokinetic–Pharmacodynamic Relationship: Duration of Dose-Effect Relationship
 01:20
Bioequivalence Experimental Study Designs: Completely Randomized and Randomized Block Designs
 01:31
Direct-Acting Cholinergic Agonists: Pharmacokinetics