Related Experiment Video
Updated: Aug 29, 2026
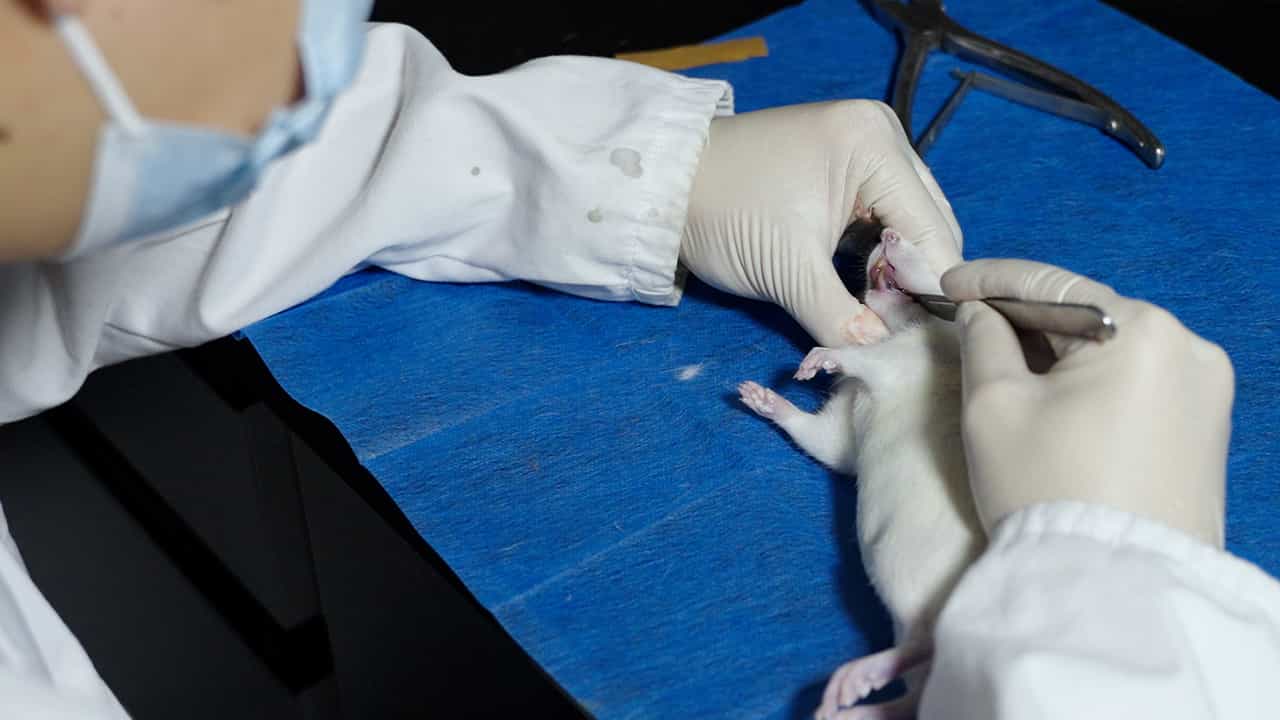

Immunofluorescent Labeling in Nasal Mucosa Tissue Sections of Allergic Rhinitis Rats via Multicolor Immunoassay
Published on: September 22, 2023
Rhinitis in pregnancy
1Clinica di Malattie Apparato Respiratorio, Servizio di Allergologia, Universita' di Torino, Azienda San Luigi, Orbassano.

Abstract:
About 30% of women suffer from nasal symptoms during pregnancy. The hormonal changes occurring during pregnancy favour per se mucosal oedema and relaxation of smooth muscles, thus contributing to nasal congestion. The most common forms of rhinitis are allergic, drug-induced, infectious and vasomotor rhinitis. In addition to the detrimental effects that rhinitis can have on quality of life, it is important to correctly treat rhinitis itself since it can influence concomitant asthma, as underlined in ARIA document. In pregnancy, the safety profile of drugs is the primary item to be considered. The American FDA pointed out that foetal damage could not be totally excluded with the majority of antirhinitis drugs. It is recommended to use "older drugs" because more data about their safety are available. Cromones are the safest drugs but, although they need multiple daily administrations. Antihistamines should be considered as second choice drugs, and their use is not recommended during the first three months of pregnancy. Topical steroids are useful in moderate-severe rhinitis, being beclometasone the most documented molecule. Topical vasoconstrictors should not be used continuously because they can induce pharmacological rhinitis. It is not recommended to start specific immunotherapy in pregnancy but it can be continued in patients who benefit from its use. Infective rhinitis should be treated with beta-lactams, cephalosporins or macrolides. Finally it is important to evaluate the cost/usefulness ratio before any drug prescription.
Related Concept Videos
 01:23
Upper Respiratory Drugs: Antitussives, Expectorants, and Mucolytics
Antitussives include codeine, dextromethorphan (Robitussin), and benzonatate (Tessalon). Codeine and dextromethorphan exert their effects centrally by suppressing the cough reflex center in the medulla. Benzonatate operates peripherally within the respiratory tract by anesthetizing...
 01:16
Drugs Used in Upper Respiratory Disorders: Overview
Antihistamines (e.g., Benadryl) block histamines from binding. Histamines are chemicals released during an allergic reaction in the body. As a...
 01:30
Epistaxis
Etiology
Possible causes of this condition include high blood pressure, trauma, low humidity, upper respiratory tract infections, allergies, foreign bodies, nasal inhalation of corticosteroids or illicit drugs, excessive use of decongestant nasal sprays, facial or nasal surgery, anatomic malformation, tumors, or systemic...
 01:29
Asthma-I: Introduction
 01:23
Chronic Pharyngitis
Etiology
It often arises from persistent viral or bacterial infections affecting sinuses and tonsils.
Additional contributing factors include inadequate dental hygiene, mouth breathing, recurring tonsillitis, allergic rhinitis, laryngopharyngeal reflux, and exposure to smoke, chemicals, and other environmental pollutants. Allergic reactions to pollen, mold, and pet dander, chronic cough, excessive voice usage,...
 01:27
Upper Respiratory Drugs: Decongestants
Most decongestants are readily available over-the-counter in various...