Related Experiment Video
Updated: Aug 29, 2026
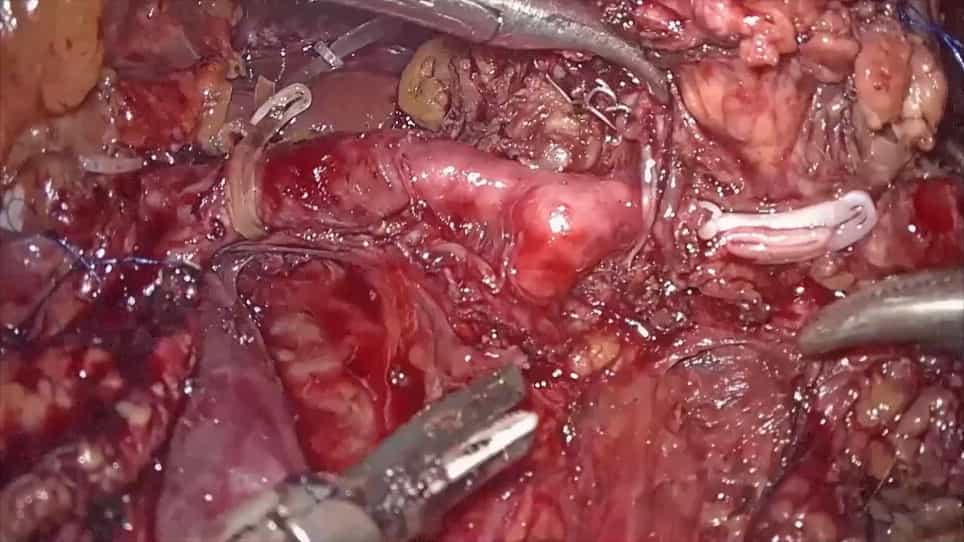
Laparoscopic Radical Antegrade Modular Pancreatosplenectomy via Dorsal-Caudal Artery Approach for Pancreatic Neck-Body Cancer
Published on: November 18, 2022
Extended lymphadenectomy and vein resection for pancreatic head cancer: outcomes and implications for therapy
Lorenzo Capussotti1, Paolo Massucco, Dario Ribero
1Unit of Surgical Oncology, Institute for Research and Cure of Cancer, Candiolo, Italy.

Hypothesis:
An aggressive strategy that includes extended lymphadenectomy and vein resection may improve the results of surgical treatment of pancreatic head cancer.
Design:
Nonrandomized control trial.
Setting:
Tertiary care referral center.
Patients:
The study included 149 consecutive patients undergoing macroscopically curative resection for periampullary adenocarcinoma from January 1, 1988, to December 31, 1998.
Interventions:
A standard resection was performed in 122 cases; an extended lymphadenectomy in 37. Twenty-four patients underwent venous resection.
Main Outcome Measures:
Data on surgical mortality, morbidity, and postoperative outcome, pathological findings, and long-term survival were analyzed.
Results:
In-hospital and 60-day operative mortality was 5.4%. Morbidity was 37.5%. Mortality, morbidity, and postoperative stay were nonsignificantly modified by extended lymphadenectomy or venous resection. Extended resection permitted the identification of a significantly higher percentage of nodal metastases beyond the peripancreatic node groups. In patients undergoing vein resection, a significantly higher rate of positive retroperitoneal margin was found. In the 100 patients with ductal adenocarcinoma, the median overall survival and the 5-year actuarial survival rate were 15 months and 8.4%, respectively. A trend toward a better survival was observed in the first 2 years after operation in the extended resection group compared with the standard resection group. Nodal status was the most powerful predictor of overall survival by multivariate analysis.
Conclusions:
Extended lymphadenectomy and vein resection did not adversely affect postoperative mortality and morbidity. Patients who required a vein resection were less likely to receive a microscopically curative pancreatectomy. Extended resection permitted better pathological staging and was associated with an early advantage in survival, but long-term survival was possible only in patients with favorable prognostic factors.