Related Experiment Video
Updated: Aug 29, 2026
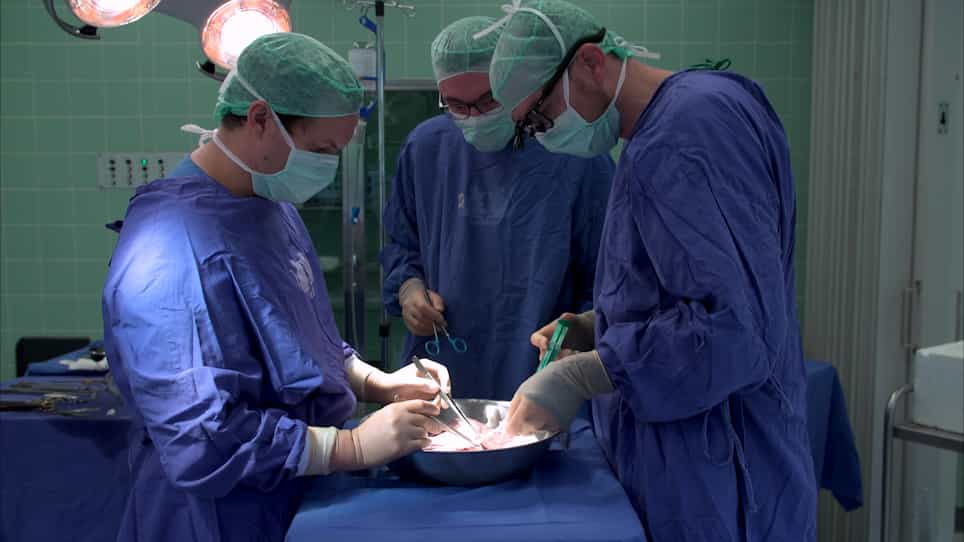

Porcine Liver Transplantation Without Veno-Venous Bypass As an Extended Criteria Donor Model
Published on: August 17, 2022
[Prognostic factors in pediatric liver transplantation. Multivariate analysis]
M López Santamaría1, M Gámez, J Murcia
1Unidad de Trasplantes Digestivos, Hospital Universitario La Paz, Paseo de la Castellana 261, 28046 Madrid.

Insights
Pediatric liver transplants (PLT) in children under three years old and those for autoimmune hepatitis present higher risks for graft loss and patient mortality. Hospital experience significantly improves outcomes in pediatric liver transplantation.
Area of Science:
- Pediatric Surgery
- Hepatology
- Transplantation Immunology
Context:
- Pediatric liver transplantation (PLT) is a complex procedure with varying outcomes.
- Understanding risk factors is crucial for improving graft and patient survival rates.
- This study analyzes a large cohort of PLT over 15 years to identify key predictors of success.
Purpose:
- To identify independent risk factors associated with graft and patient survival in pediatric liver transplants.
- To analyze the impact of pretransplant status, surgical techniques, and donor conditions on PLT outcomes.
- To determine predictors for graft loss and patient mortality in a pediatric liver transplant cohort.
Summary:
- Multivariate analysis identified UNOS 1 status, recipient age under 3 years, transplantation for autoimmune hepatitis, and transplant era as independent predictors of graft loss.
- Independent factors influencing patient survival included receiving more than one graft, recipient age under 3 years, and transplant era.
- Graft survival was influenced by 11 variables, while patient survival was impacted by recipient age, transplant for autoimmune hepatitis, and transplant era.
Impact:
- Liver transplantation in very young children (<3 years) is associated with a significantly increased risk of graft loss and mortality.
- Hospital experience and expertise in pediatric liver transplantation are critical for improving patient and graft survival, especially in high-risk populations.
- These findings can inform clinical decision-making and resource allocation to optimize outcomes for pediatric liver transplant recipients.
Aim:
To analyze independent risk factors associated with poor graft and patient survival in a series of 292 pediatric liver transplants (PLT) performed in 234 children during a 15 years period. MATERIAL AND METHODS. 1. Univariate graft and patient survival analysis in 45 variables related to pretransplant patient status, surgical technique and donor conditions. 2. Variables found with univariate analysis to be associated with outcome were entered into a stepwise backward proportional hazard model (Cox), to determine independent prediction of outcome.
Results:
11 variables influence the graft survival: recipient age, z-score recipient height, UNOS status, recipient and donor weight, transplant for immune hepatitis, platelet transfusion during the transplant, blood index > 4 during the surgery, type of arterial reconstruction, retransplantation and era of the transplant (first er: 1986-1990; 2nd. era: 1991-1995; 3rd. era: 1996-2000). Four of those variables are independent in the multivariate analysis: UNOS 1 status (Odds Ratio, OR = 2.82, 95% confidence interval = 1.36-5.85), recipient < 3 years (OR = 3.76, 95% CI = 2.13-6.63), transplants for autoimmune hepatitis and era (OR of first and second versus third era respectively 3.93 and 2.81). The independent variables influencing the patient survival were: children receiving more than one graft children less than 3 years old and transplant era.
Conclusions:
Liver transplant in small children is associated with an increased risk of graft loss and patient dead. The experience of the hospital in pediatric liver transplantation improves the results, particularly in small children.

