Chronic catheterization of the spinal subarachnoid space
Related Experiment Video
Updated: Aug 5, 2026

Pre-Chiasmatic, Single Injection of Autologous Blood to Induce Experimental Subarachnoid Hemorrhage in a Rat Model
Published on: June 18, 2021

Abstract:
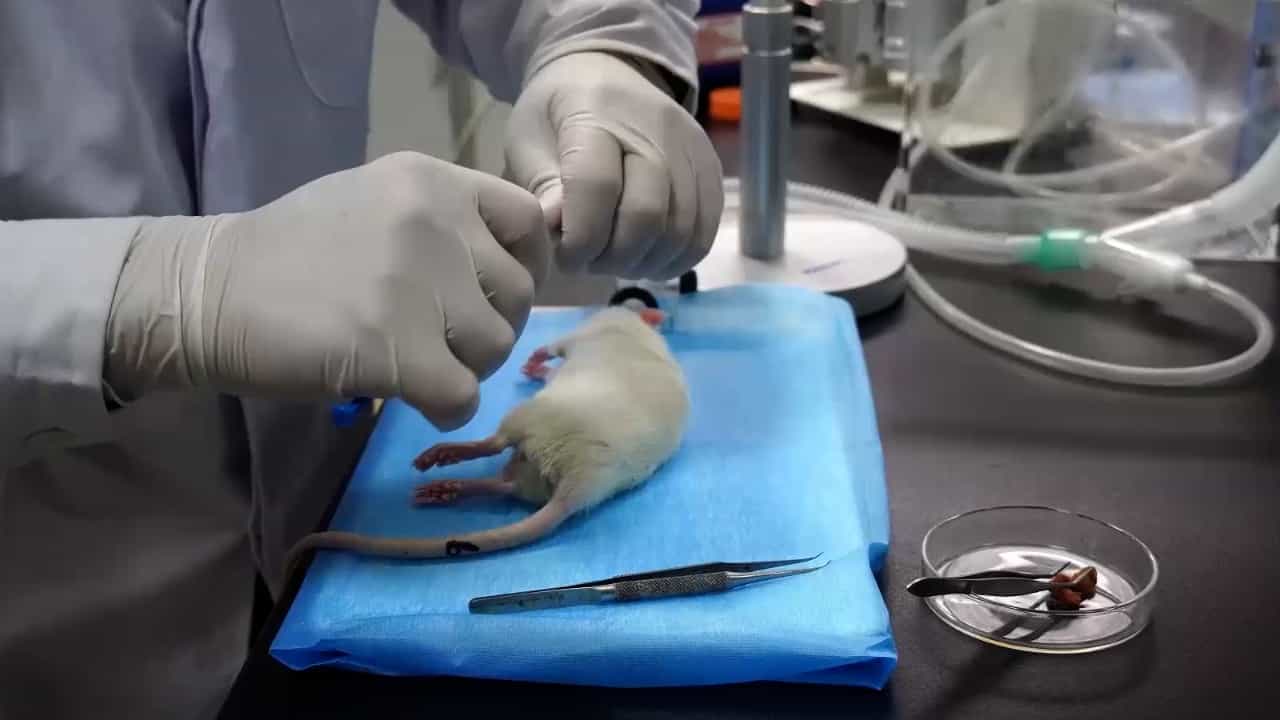
To administer drugs into the spinal subarachnoid space of unanesthetized and intact rats and rabbits, a procedure is described whereby a polyethylene catheter (PE-10) may be inserted through a puncture of the atlanto-occipital membrane and secured to the skull. Calibration experiments carried out with bromophenol blue dye, 3H-naloxone and 14C-urea revealed first, that there was little rostro-caudal diffusion of the injectate along the spinal axis and secondly, that even for compounds such as naloxone which can rapidly permeate neural tissues, the levels which do appear in the brain are small following the spinal subarachnoid administration of the drug. Control injections, administered either acutely or repeatedly over a prolonged period of time, had no detectable effect on the animal's behavior. These observations, as well as the lack of pathology in the spinal cords of rats having such catheters for periods of up to 4 months suggests that the implant is well tolerated.

Related Concept Videos
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:22
Aneurysm IV: Nursing Management
 01:14
Increased Intracranial Pressure l: Introduction