Related Experiment Video
Updated: Aug 29, 2026


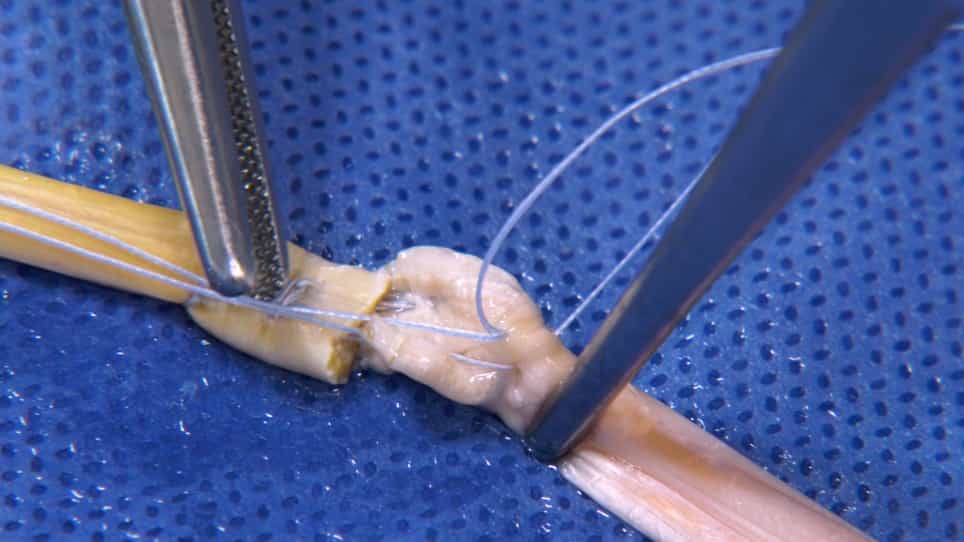
Murine Flexor Tendon Injury and Repair Surgery
Published on: September 19, 2016
[The treatment of flexor tendon injuries in children]
1Universitätsklinik für Kinderchirurgie Graz, Graz, Osterreich. heidi.friedrich@klinikum-graz.at

Insights
Immediate flexor tendon reconstruction in children, using a modified Kleinert plaster, leads to excellent functional recovery. This dynamic post-operative treatment is effective for pediatric patients, achieving full mobility within three months.
Area of Science:
- Pediatric Surgery
- Orthopedic Surgery
- Hand Surgery
Background:
- Flexor tendon reconstruction aims for full functional recovery in all patients, including infants.
- Timely intervention for severed flexor tendons in children is crucial.
- A modified Kleinert plaster offers a recommended alternative to a bandaged fist for immobilization.
Purpose of the Study:
- To evaluate a pediatric flexor tendon reconstruction protocol.
- To determine the applicability of the treatment across all pediatric age groups.
- To assess the advisability of dynamic post-operative treatment with a modified Kleinert plaster.
Main Methods:
- A retrospective study of 211 pediatric patients (9 months to 18 years) with severed flexor tendons.
- 193 lesions were treated with immediate or early reconstruction (within 48 hours).
- The Kirchmayr-Zechner suturing procedure was routinely applied.
Main Results:
- Full mobility was achieved within three months post-operatively.
- Follow-up on 173 cases showed good or excellent results in 95% according to Buck-Gramcko's criteria.
- The modified Kleinert plaster approach proved effective for pediatric patients.
Conclusions:
- The established therapeutic protocol is effective for pediatric flexor tendon reconstruction.
- Dynamic post-operative treatment with a modified Kleinert plaster is advisable for children.
- High rates of good to excellent functional recovery can be achieved in pediatric flexor tendon injuries.
Abstract:
Full functional recovery must always be the aim of flexor tendon reconstruction. This not only applies to adults, but particularly to infants. As customary, also in a child a severed flexor tendon should be attended immediately or with only a short delay. However, we definitively reject a bandaged fist of a hand and rather recommend demobilization by a modified Kleinert plaster. At the University Clinic for Paediatric Surgery in Graz over ten years ago we established a therapeutic protocol dedicated to infants, which we evaluated recently. In this study questions addressed were whether this treatment regimen is applicable for all age groups, notably whether the dynamic post operative treatment with a modified Kleinert plaster is always advisable. A total of 211 severed flexor tendons in children from nine months to 18 years (median 7 years) were treated. 193 lesions were either reconstructed immediately or within 48 hours. As a rule we apply the Kirchmayr-Zechner suturing procedure. We believe that the desired full mobility can thus be obtained within three months. In 95% of the 173 cases followed-up we achieved this goal with good or even excellent results according to Buck-Gramcko's criteria.