Related Experiment Video
Updated: Aug 25, 2026
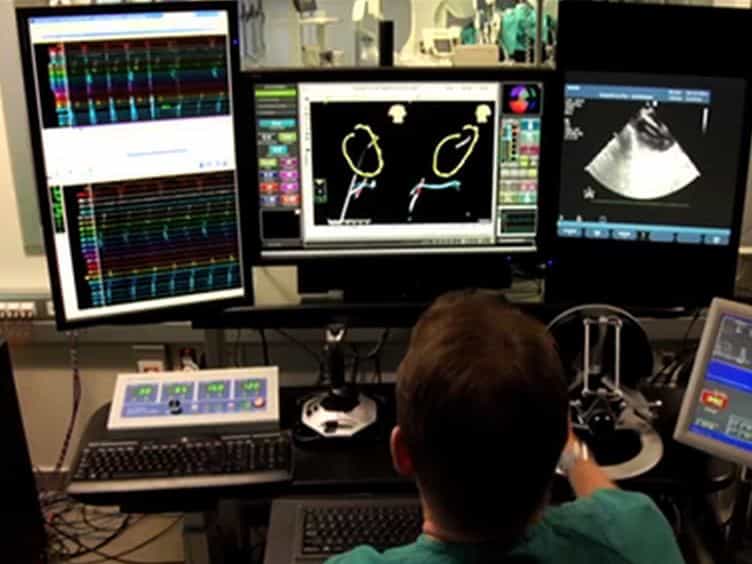

Remote Magnetic Navigation for Accurate, Real-time Catheter Positioning and Ablation in Cardiac Electrophysiology Procedures
Published on: April 21, 2013

Insights
Pediatric care for complete heart block (CHB) requires monitoring for respiratory failure and shock. Recognizing early signs of respiratory distress and compromised organ perfusion is critical for timely intervention in children.
Area of Science:
- Pediatric Cardiology
- Critical Care Medicine
- Emergency Medicine
Background:
- Complete heart block (CHB) in pediatric patients presents unique challenges due to variations in size, anatomy, and physiology.
- Cardiac arrest in children is frequently a consequence of respiratory arrest, necessitating vigilant respiratory monitoring.
Observation:
- Respiratory arrest should be anticipated in pediatric patients exhibiting decreased consciousness, poor muscle tone, increased respiratory rate or effort (e.g., nasal flaring, retractions), or cyanosis.
- Shock, defined as inadequate perfusion of vital organs, is a critical concern in CHB.
- In CHB, bradycardia (slow heart rate) can substantially reduce cardiac output, impacting organ perfusion.
Findings:
- The management of pediatric CHB hinges on recognizing signs of respiratory failure and shock.
- Continuous reassessment of vital signs, including level of consciousness, peripheral circulation, and blood pressure, is essential for managing shock in CHB.
Implications:
- Early identification of respiratory distress and shock can significantly improve outcomes for pediatric CHB patients.
- Understanding the interplay between bradycardia, cardiac output, and organ perfusion is vital for effective clinical management.
- Tailoring care to the pediatric population's specific physiological differences is paramount in managing CHB.
Abstract:
Care for the pediatric patient with CHB focuses on signs and symptoms associated with respiratory failure and shock. Differences in size among pediatric patients--and in anatomy, physiology, and possible causes--should be considered. In children, cardiac arrest is usually secondary to respiratory arrest. Respiratory arrest should be anticipated in a pediatric patient with (1) decreased level of consciousness, (2) poor muscle tone, (3) increased respiratory rate or respiratory effort (nasal flaring, intercostal, subcostal, and suprasternal retractions); or (4) cyanosis. Shock is the failure of the cardiovascular system to perfuse vital organs adequately. Organ perfusion is determined by cardiac output, which in turn results from the heart rate times stroke volume. In CHB the slowing of heart rate can significantly decrease cardiac output, so the signs and symptoms of shock--especially level of consciousness, peripheral circulation, and blood pressure--must continually be reassessed.
More Related Videos
 12:45
Benefits of Cardiac Resynchronization Therapy in an Asynchronous Heart Failure Model Induced by Left Bundle Branch Ablation and Rapid Pacing
Published on: December 11, 2017
 04:55
Pediatric Animal Model of Extracorporeal Cardiopulmonary Resuscitation After Prolonged Circulatory Arrest
Published on: May 26, 2023
Related Concept Videos
 01:19
Electrophysiology of Normal Cardiac Rhythm
 01:19
Conduction System of the Heart
The pacemaker cells are located in two primary nodes: the sinoatrial (SA) node and the atrioventricular (AV) node. The SA node pacemaker cells can autonomously depolarize, triggering an action potential that leads to the...
 01:29
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
 01:20
Conduction System of the Heart
This system relies on the unique properties of nodal and Purkinje cells:...
 01:30
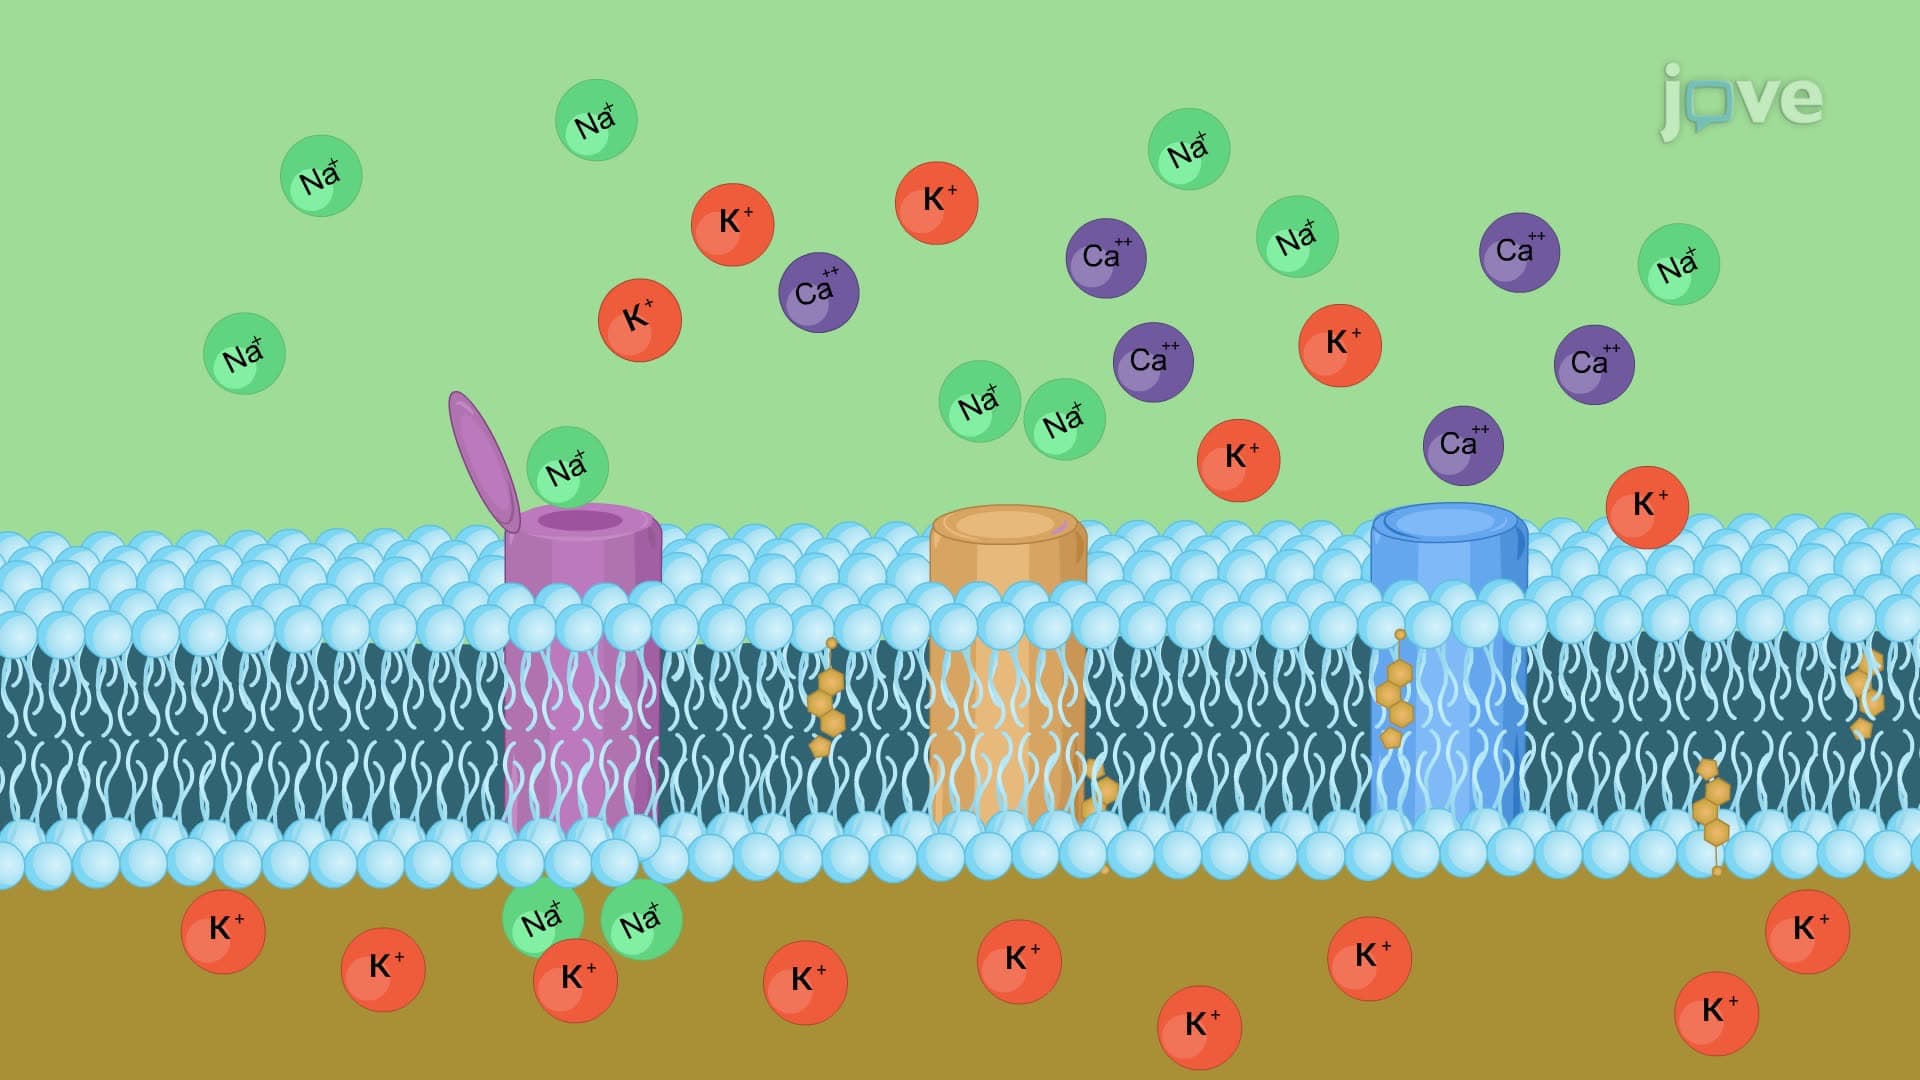
Cardiac Action Potential
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias