Related Experiment Video
Updated: Aug 20, 2026
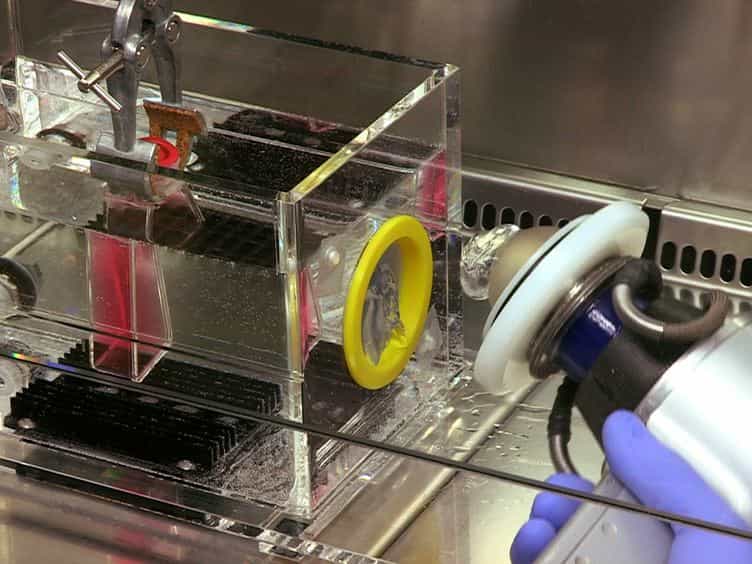

Shock Wave Application to Cell Cultures
Published on: April 8, 2014
Safety and efficacy of extracorporeal shock wave lithotripsy in infants
Gordon A McLorie1, Jeff Pugach, Dov Pode
1Division of Urology, The Hospital for Sick Children, Toronto, Ontario, Canada.

Insights
Extracorporeal shock wave lithotripsy (ESWL) is safe and effective for children under 3.5 years old, achieving an 86% success rate. Treatment parameters similar to adults can be used, and routine preoperative stenting is not recommended.
Area of Science:
- Pediatric Urology
- Nephrolithiasis Treatment
- Minimally Invasive Surgery
Background:
- Extracorporeal shock wave lithotripsy (ESWL) is established for adult kidney stones.
- Limited data exists on ESWL efficacy and safety in young children (<3.5 years).
Purpose of the Study:
- Evaluate the safety and effectiveness of ESWL in children under 3.5 years.
- Define optimal ESWL treatment parameters for this age group.
Main Methods:
- Retrospective review of 34 children (<3.5 years) undergoing ESWL across three centers.
- Analysis of patient demographics, stone characteristics, ESWL parameters, and outcomes.
- Procedures performed under general anesthesia with modified equipment for improved localization.
Main Results:
- Successful stone fragmentation (<2 mm) achieved in 86% of cases (66% single treatment, 86% multiple treatments).
- Average patient age was 23.4 months; average stone size was 13 mm.
- No major acute or long-term complications were observed.
Conclusions:
- ESWL is a safe and effective treatment for kidney stones in children under 3.5 years.
- Similar ESWL parameters to adults can be utilized, with modifications to positioning devices.
- Routine preoperative ureteral stenting is not beneficial for large stones in this population.
Purpose:
Extracorporeal shock wave lithotripsy (ESWL) in older children appears to have comparable results when compared to adults, no study has focused on its use in younger children. We reviewed our ESWL experience in children under age 3.5 years to evaluate its safety, and define optimal treatment parameters.
Methods:
We retrospectively reviewed consecutive medical and diagnostic imaging records from three ESWL centers, pertaining to 34 children under 3.5 years of age (36 renal units-RU). The children were from two distinct populations served exclusively by the three centers. We analyzed patient presentation, etiology, age, weight, stone size, preoperative interventions, energy settings, number of shock waves, number of treatments, success (stone fragments < 2 mm), and complications. We performed all forty-nine procedures under general anesthesia and modified the Dornier MFL 5000 table and the Dornier HM3 gantry to improve coupling and localizing of the calculi.
Results:
In each population, we noted similar presentations, etiologies, and treatment parameters. Patient age ranged from 6 to 40 months (mean 23.4 months). Stone size ranged from 4 mm to 22 mm diameter (average 13 mm). ESWL parameters included an average of 2210 shocks (range 900-3400) at average of 20.9 kV (range 19 kV-25 kV). Preoperative ureteral stent placement was not shown to be beneficial. Our one and multiple treatment ESWL success rates were 66% and 86%, respectively. No major acute or long-term complications occurred.
Conclusions:
We successfully performed ESWL using treatment parameters similar to adults in 86% of children under 3.5 years without major complications. Modifications of the positioning device improved coupling and localization in smaller patients. Routine preoperative ureteral stenting for large stones is not recommended.