Related Experiment Video
Updated: Aug 29, 2026
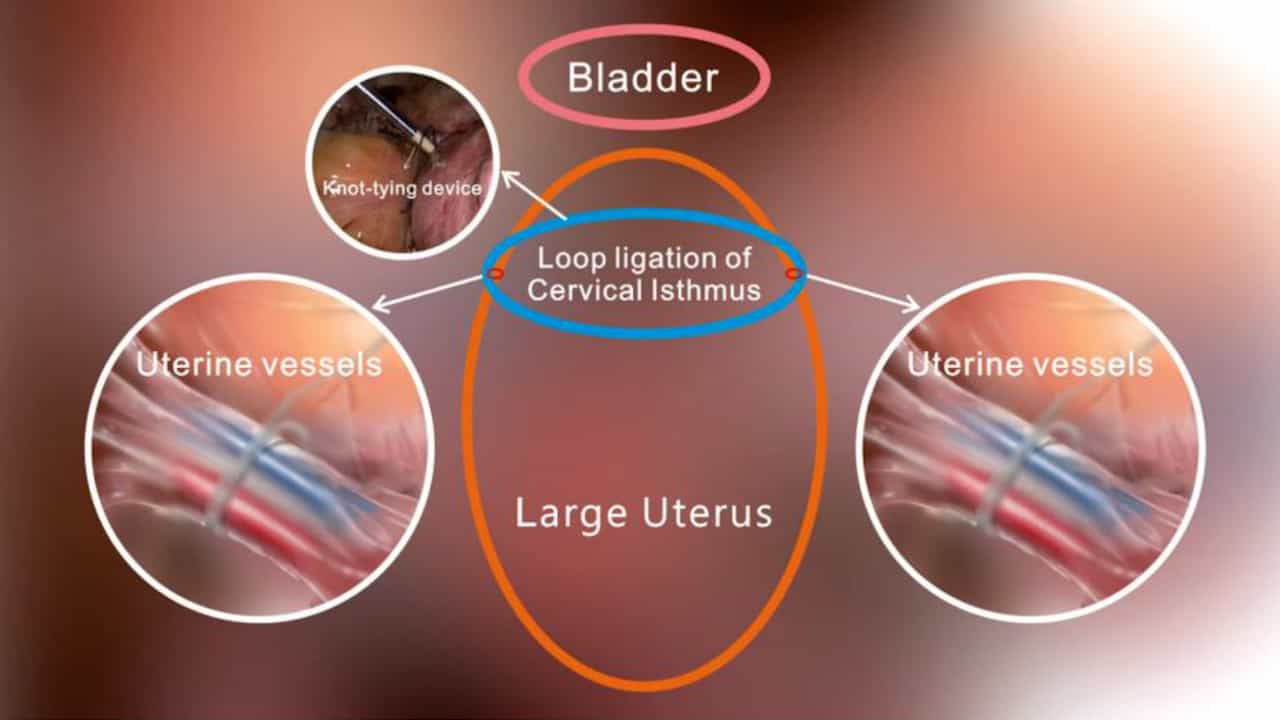

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Obstructed labour
J P Neilson1, T Lavender, S Quenby
1Department of Obstetrics & Gynaecology, University of Liverpool, Liverpool, UK. jneilson@liv.ac.uk

Obstructed labour is an important cause of maternal deaths in communities in which undernutrition in childhood is common resulting in small pelves in women, and in which there is no easy access to functioning health facilities with the capability of carrying out operative deliveries. Obstructed labour also causes significant maternal morbidity in the short term (notably infection) and long term (notably obstetric fistulas). Fetal death from asphyxia is also common. There are differences in the behaviour of the uterus during obstructed labour, depending on whether the woman has delivered previously. The pattern in primigravid women (typically diminishing contractility with risk of infection and fistula) may result from tissue acidosis, whereas in parous women, contractility may be maintained with the risk of uterine rupture. Ultimately, tackling the problem of obstructed labour will require universal adequate nutritional intake from childhood and the ability to access adequately equipped and staffed clinical facilities when problems arise in labour. These seem still rather distant aspirations. In the meantime, strategies should be implemented to encourage early recognition of prolonged labour and appropriate clinical responses. The sequelae of obstructed labour can be an enormous source of human misery and the prevention of obstetric fistulas, and skilled treatment if they do occur, are important priorities in regions where obstructed labour is still common.
Obstructed labour is an important cause of maternal deaths in communities in which undernutrition in childhood is common resulting in small pelves in women, and in which there is no easy access to functioning health facilities with the capability of carrying out operative deliveries. Obstructed labour also causes significant maternal morbidity in the short term (notably infection) and long term (notably obstetric fistulas). Fetal death from asphyxia is also common. There are differences in the behaviour of the uterus during obstructed labour, depending on whether the woman has delivered previously. The pattern in primigravid women (typically diminishing contractility with risk of infection and fistula) may result from tissue acidosis, whereas in parous women, contractility may be maintained with the risk of uterine rupture. Ultimately, tackling the problem of obstructed labour will require universal adequate nutritional intake from childhood and the ability to access adequately equipped and staffed clinical facilities when problems arise in labour. These seem still rather distant aspirations. In the meantime, strategies should be implemented to encourage early recognition of prolonged labour and appropriate clinical responses. The sequelae of obstructed labour can be an enormous source of human misery and the prevention of obstetric fistulas, and skilled treatment if they do occur, are important priorities in regions where obstructed labour is still common.
Related Concept Videos
 01:11
Pyloric Obstruction
 01:29
Intestinal Obstruction I: Introduction
 01:07
Intestinal Obstruction II: Pathophysiology
 01:29
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:22
Birth Control Methods