Related Experiment Video
Updated: Aug 29, 2026


Laparoscopic Splenectomy with Pericardial Devascularization for Hypersplenism and Esophageal Variceal Hemorrhage Due to Portal Hypertension
Published on: November 15, 2024
Portal vein thrombosis after splenectomy for gastric malignant lymphoma
Kazumasa Fujitani1, Akiko Nishiyama, Toshimasa Tsujinaka
1Department of Surgery, Osaka National Hospital, 2-1-14 Hoenzaka, Chuo-ku, 540-0006, Osaka, Japan.

Abstract:
Portal vein thrombosis (PVT) has rarely been documented in patients after splenectomy for gastric malignancy. We report a case of PVT that occurred after splenectomy as part of an en-bloc node dissection performed to treat gastric malignant lymphoma. A 38-year-old man underwent total gastrectomy and splenectomy with en-bloc D2 lymph node dissection. The spleen weighed 480 g. On postoperative day (POD) 31, the patient complained of abdominal pain in the right upper quadrant accompanied by fever. Moderate elevations of C-reactive protein (CRP), aspartate transaminase (AST), and alanine transaminase (ALT) were noted. Contrast-enhanced computed tomography (CT) and ultrasonography disclosed thrombus in the portal vein and the splenic vein. There were no abnormalities in the levels of lupus anticoagulant, protein C antigen, protein S antigen, or antithrombin III (AT III). A diagnosis of PVT was made, and prompt treatment, including intravenous heparin combined with tissue plasminogen activator (tPA) was initiated, followed by longterm warfarin. This treatment resulted in clinical improvement, but failed to achieve thrombolysis in the portal vein. At follow-up after 6 months, the patient complained of postprandial abdominal pain with persistent peripheral edema and ascites. This case indicates that splenectomy for en-bloc node dissection in gastric malignancy is a possible cause of PVT. Because both the symptoms and the laboratory data in PVT are nonspecific, a high level of clinical suspicion and a low threshold for obtaining imaging examinations are important in the early diagnosis of PVT. Surgeons should remember PVT among several other complications whenever patients treated with radical gastrectomies are symptomatic and imaging studies are considered necessary.

Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:24
Esophageal Varices-I: Introduction
 01:21
Hepatic Portal System
At its core, the hepatic portal vein is the result of a confluence of the superior and inferior mesenteric veins along with the splenic vein. Each of these veins has a unique role. The superior mesenteric vein is responsible...
 01:16
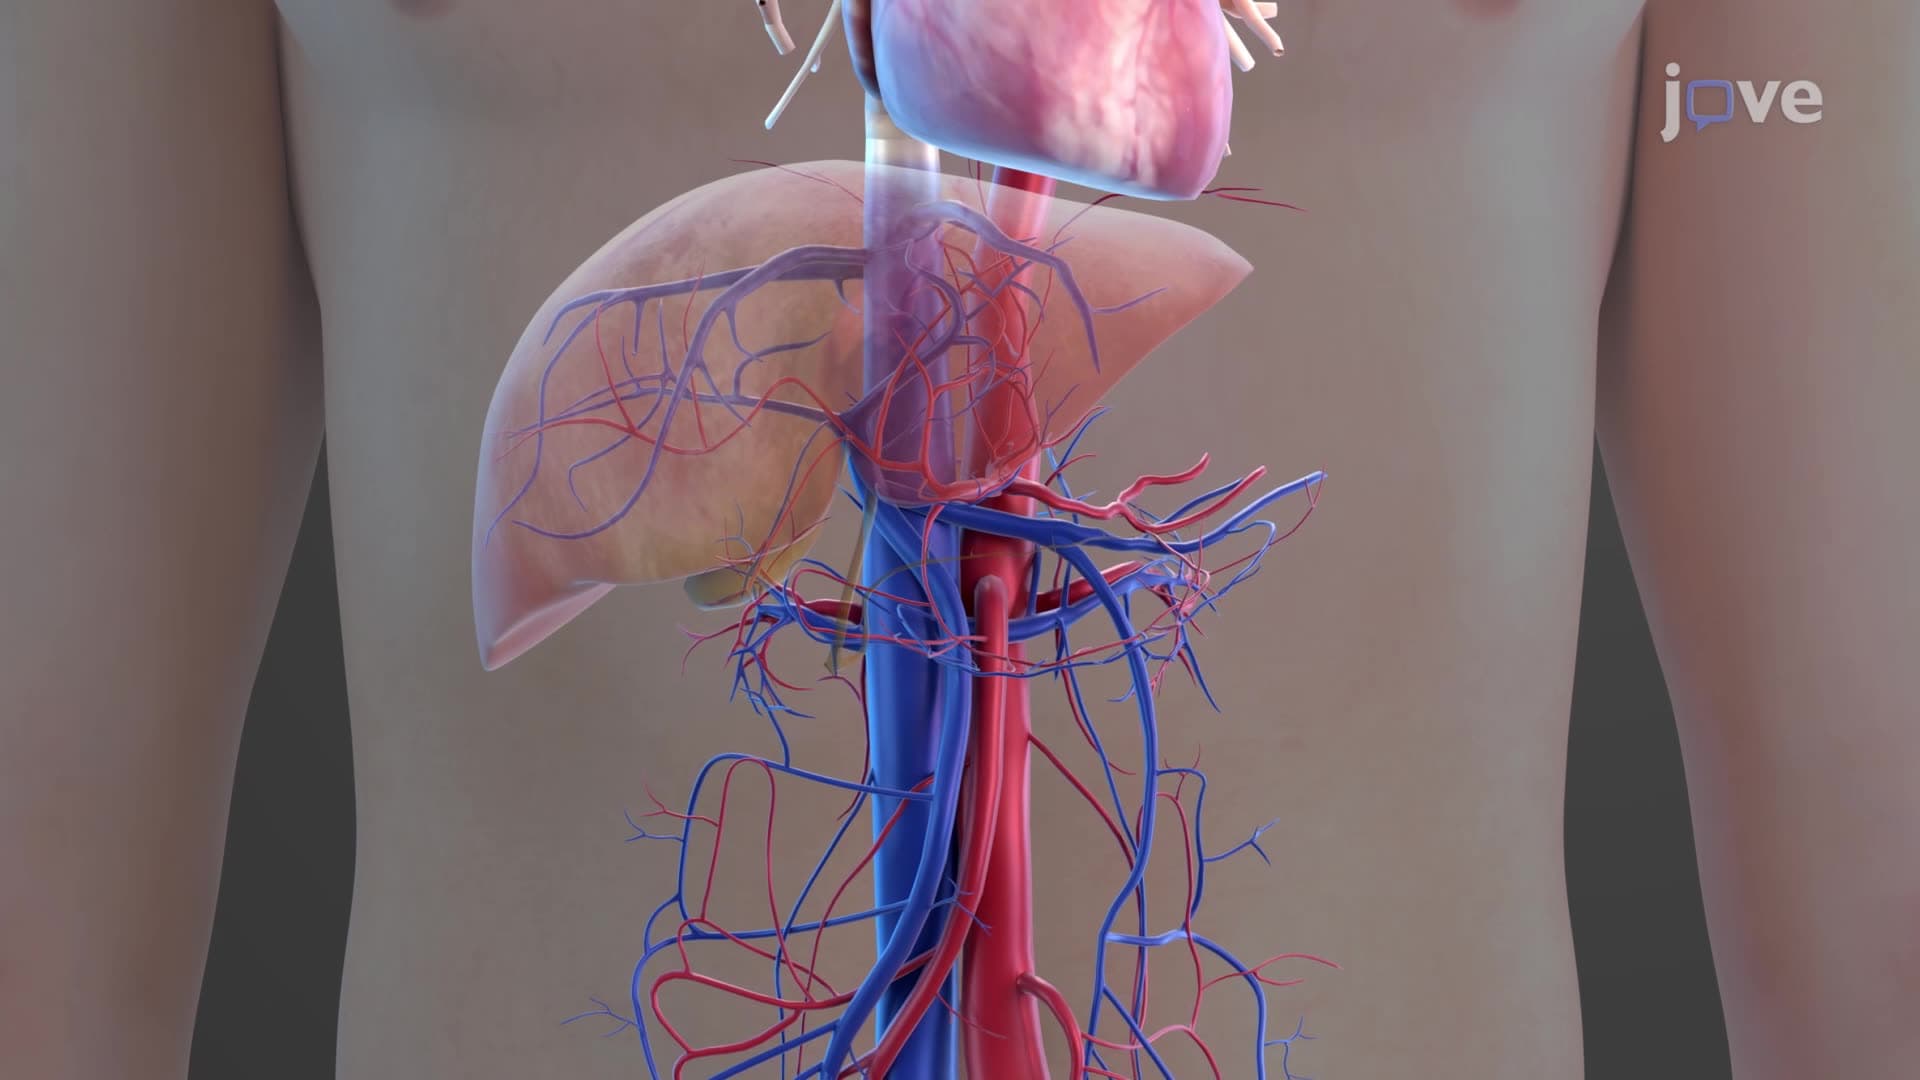
Blood Supply to the Digestive System
Blood Supply to the Digestive System: The splanchnic circulation involves three main arteries: the celiac artery (also known as the celiac trunk) and the superior and inferior mesenteric...
 01:29
Venous Thrombosis III: Interprofessional Care