Related Experiment Video
Updated: Aug 29, 2026

Assessing Insulin Clearance in Mice via In Situ Liver Perfusion
Published on: December 13, 2024
Insulin decreases hepatic acute phase protein levels in severely burned children
Xiaowu Wu1, Steven J Thomas, David N Herndon
1Shriners Hospitals for Children and Department of Surgery, the University of Texas Medical Branch, Galveston, Tex 77550, USA.

Insights
Continuous insulin treatment significantly reduces acute phase proteins in severely burned children. This suggests insulin helps regulate the body's inflammatory response to severe injury.
Area of Science:
- Biochemistry
- Endocrinology
- Pediatric Critical Care
Background:
- Severe burns trigger a hepatic acute phase response, characterized by altered protein synthesis.
- The role of insulin in modulating this response post-burn injury remains incompletely understood.
Purpose of the Study:
- To investigate the effect of continuous insulin treatment on acute phase protein levels in children with severe burns.
- To determine if insulin can downregulate the hepatic acute phase response following major trauma.
Main Methods:
- A randomized controlled trial involving 18 pediatric patients with >40% total body surface area burns.
- Patients received either continuous insulin infusion to maintain euglycemia or no treatment.
- Plasma levels of various acute phase and hepatic constitutive proteins were measured at multiple time points post-injury.
Main Results:
- Insulin treatment led to significant reductions in levels of alpha1-acid glycoprotein, C3 complement, alpha2-macroglobulin, and haptoglobin.
- These decreases were most pronounced at 21 and 28 days post-burn.
- Hepatic constitutive proteins (prealbumin, transferrin, retinol-binding protein) were also lower in the insulin group by day 21.
Conclusions:
- Continuous insulin administration effectively decreases acute phase protein levels in severely burned children.
- Insulin appears to play a role in downregulating the hepatic acute phase response to severe burn injury.
Background:
Severe burn induces the hepatic acute phase response. In this study, we wondered whether continuous insulin treatment decreases acute phase protein levels in the severely burned.
Methods:
Eighteen children aged 2 to 17 years with burns >40% of total body surface area were randomized to receive either insulin (n=9) or no treatment (n=9) within 72 hours after injury until the wounds were 95% healed. Insulin was given at a continuous rate of > or =1.5 microU/kg/min to maintain euglycemia (serum glucose 100-140 microg/dL). Plasma was examined at days 7, 14, 21, and 28 for acute phase protein levels including C-reactive protein, C3 complement, alpha1-acid glycoprotein, haptoglobin, alpha2-macroglobulin, prealbumin, transferrin, and retinol-binding protein. Statistical analysis was by ANOVA and t test.
Results:
With insulin treatment, alpha1-acid glycoprotein, C3 complement, alpha2-macroglobulin, and haptoglobin levels decreased (P<.05) after a severe burn compared with control, especially at days 21 and 28. Additionally, the hepatic constitutive proteins (prealbumin, transferrin, and retinol-binding protein) were lower in the insulin-treatment group than those of the control group at day 21 (P<.05).
Conclusions:
Continuous insulin treatment decreases acute phase protein levels after a severe burn. The results suggest insulin downregulation of the hepatic acute phase response to injury.


Related Concept Videos
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:16
Hormones Regulating Blood Glucose
In addition to accelerating glucose uptake and utilization, insulin has...
 01:15
Hypoglycemia and Glucagon
 01:25
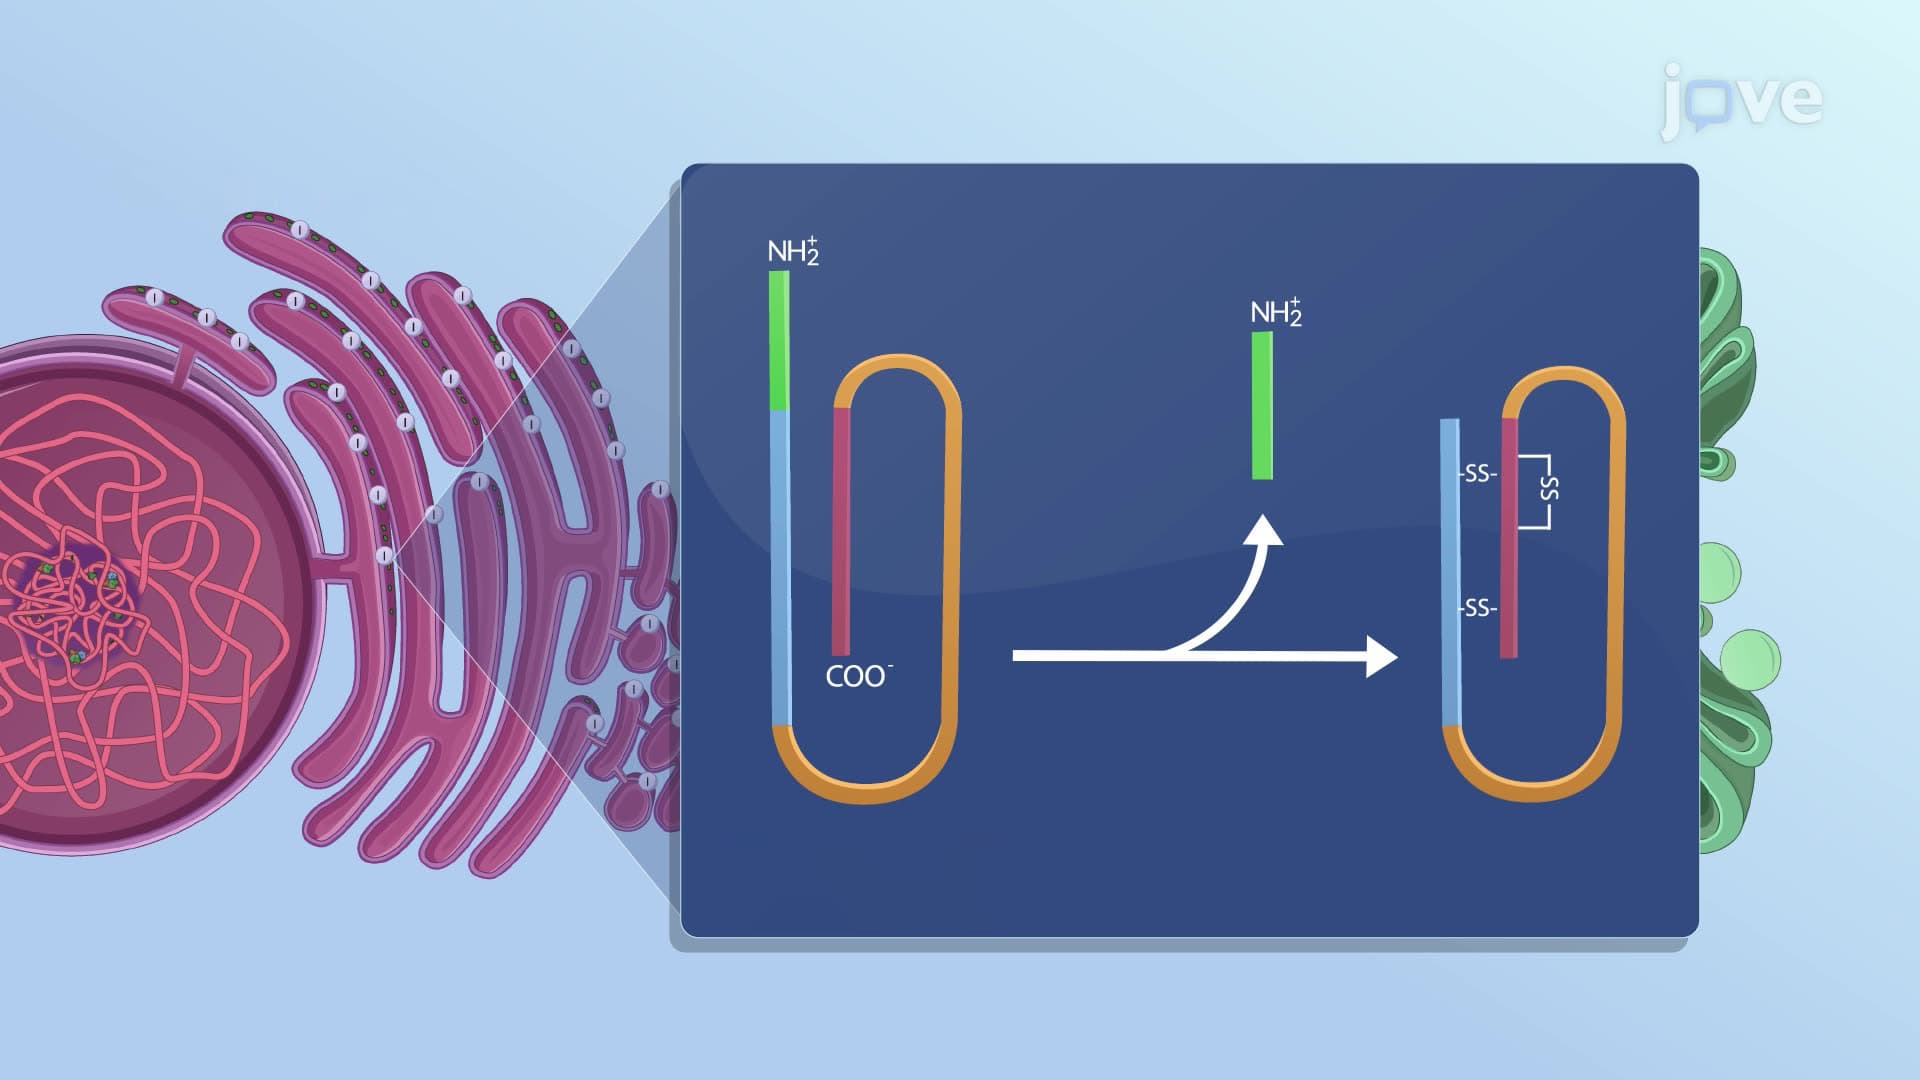
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are co-secreted in...
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management