Related Experiment Video
Updated: Aug 29, 2026
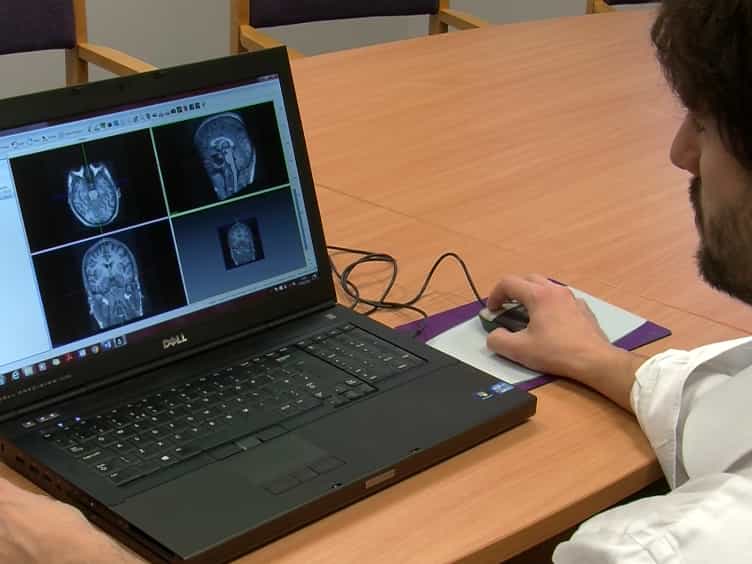

A Pipeline for 3D Multimodality Image Integration and Computer-assisted Planning in Epilepsy Surgery
Published on: May 20, 2016
Neuroimaging of the complications of epilepsy surgery
Roger E Kelley1, John DellaBadia, Alireza Minagar
1Department of Neurology, LSU Health Sciences Center, 1501 Kings Highway, Shreveport, LA 71103, USA. rkelly@lsuhsc.edu

Background And Purpose:
Stroke-like symptoms can be associated with the invasive evaluation and surgical resection of epileptic foci in patients with intractable epilepsy. Neurological deficits following surgical procedures for epilepsy are not uncommon, but most are relatively minor and transient. The authors investigated the neuroimaging patterns of cerebral tissue insults in patients suffering neurological deficits directly related to procedures performed to evaluate and treat intractable epilepsy. They attempted to discern potential secondary vascular insults from the not unexpected tissue loss that can be associated with various epilepsy procedures.
Methods:
The authors prospectively assessed 7 consecutive patients who underwent either the invasive electrocortigraphic monitoring or surgical resection of epileptic foci. All had some degree of neurological deficit postoperatively. The authors evaluated for tissue injury type with postoperative computed tomography and magnetic resonance brain imaging. They also review pertinent medical literature addressing potential complications of epilepsy surgery.
Results:
Three patients had primarily ischemic tissue injuries, 2 had tissue loss with minor bleeding, and 1 transient deficit appeared to reflect the amount of tissue removed. Another patient had choreiform movements and gait ataxia 1 week after the procedure, but no follow-up neuroimaging was available. The primary ischemic insults appeared to be related to vascular traction or compression or possibly vasospasm. The tissue loss/hemorrhagic insults were presumably related to tissue loss, with seepage of blood or bleeding from a resected cavernous hemangioma. No patients died, but 1 was left with a persistent, moderately severe neurological deficit.
Conclusions:
It is important to distinguish the not unexpected neurological deficits associated with inadvertent trauma to normal brain tissue during procedures associated with epilepsy surgery from vascular insults. Postoperative neuroimaging can be useful in this endeavor.
More Related Videos
 09:00
Investigating the Function of Deep Cortical and Subcortical Structures Using Stereotactic Electroencephalography: Lessons from the Anterior Cingulate Cortex
Published on: April 15, 2015
 09:57
Electromagnetic Source Imaging in Presurgical Evaluation of Children with Drug-Resistant Epilepsy
Published on: September 20, 2024
